[Tuberculosis in Japan at present and in near future]
Related Experiment Video
Updated: Oct 4, 2026

Analysis of 18FDG PET/CT Imaging as a Tool for Studying Mycobacterium tuberculosis Infection and Treatment in Non-human Primates
Published on: September 5, 2017
1Division of Respiratory Diseases, Tokyo National Sanatorium Hospital, Japan.

Abstract:
The high incidence of tuberculosis in the elderly people and no decrease in the incidence rate of the young people are two main features of current tuberculosis problem in Japan. To examine the near future prediction of the incidence rate and the rate of clinical breakdown by age group, the incidence rates of the newly registered tuberculosis cases of the cohorts born before 1918, in 1919-28, 1929-38, 1939-48, 1949-58 and 1959-68 were studied every ten years. The curves of incidence rate in each cohort were extrapolated to the future to obtain the incidence rates in 2008 and 2018. The numbers of predicted new cases in 2008 and 2018 were estimated to be some 31,000 and 23,000, respectively. The percentage of the cases above 60 y.o. was estimated to be 59%, 59% respectively. As the number of new cases in 1998 was 41,000, 55% of which was above 60 y.o., it will steadily decrease from now on, but the elderly people more than 60 y.o. will continue to occupy high percentage of the new cases. The incidence rate of the new cases will also decrease from 32.4 (per 100,000 populations) in 1998 to 24.5 in 2008 and 19.4 in 2018, and Japan in 2018 will still be a middle prevalence country in the world as now. The rate of clinical breakdown is obtained from dividing the incidence rate by the prevalence of tuberculosis infection. The latter is theoretically calculated from the annual risk of tuberculosis infection assuming that it doesn't depend on age. In Japan the annual risk of infection was supposed to be constant and about 4% till 1947. Since then it declined by some 10% annually till around 1977. Thereafter the annual speed of its decline was estimated to have slowed down. But we cannot know the true annual risk of tuberculosis infection, as BCG vaccination hinders the interpretation of the result of tuberculin skin testing in Japan. We postulated it declined 5% annually (Model A) or it was constant to be 0.17% since 1977 (Model B). Using these models of annual risk of tuberculosis infection, the prevalence of tuberculosis infection by age group was calculated in every calendar year. The incidence rate of each age group was assumed to be equal to that of median age in each age group. For example, the incidence rate of the cohort born in 1919-28 was assumed to be equal to that of the cohort born in 1923. In this way, the annual rates of clinical breakdown of the cohorts born in 1923, 1933, 1943, 1953, 1963 and 1973 were calculated. The rates of clinical breakdown for the cohorts born in 1923, 1933 and 1943 were similar with each other and were approximately 100 per 100,000 in both models. The rate of clinical breakdown at 25 years old for the cohort born in 1953 was 0.64 times smaller than that for the cohort born in 1943. It might due to the improvement of nutritional state and the effectiveness for adult tuberculosis of compulsory BCG vaccination which has been done after World War II in Japan. But for the cohort born after World War II, the later the cohort was born, the larger its rate of clinical breakdown was in both models. And, for example, the rate of clinical breakdown at age 25 years old for the cohort born in 1973 was 2.4 times (in Model A) or 1.7 times (in Model B) larger than that for the cohorts born in 1953. This may imply that there has been some factor(s) which facilitates tuberculous disease after tuberculous infection in young people in modern Japan. One explanation for this is the possibility that immune ability to tuberculosis might be weakened in young generations by some factor(s) such as environmental pollution.
Related Concept Videos
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:28
Pulmonary Tuberculosis V
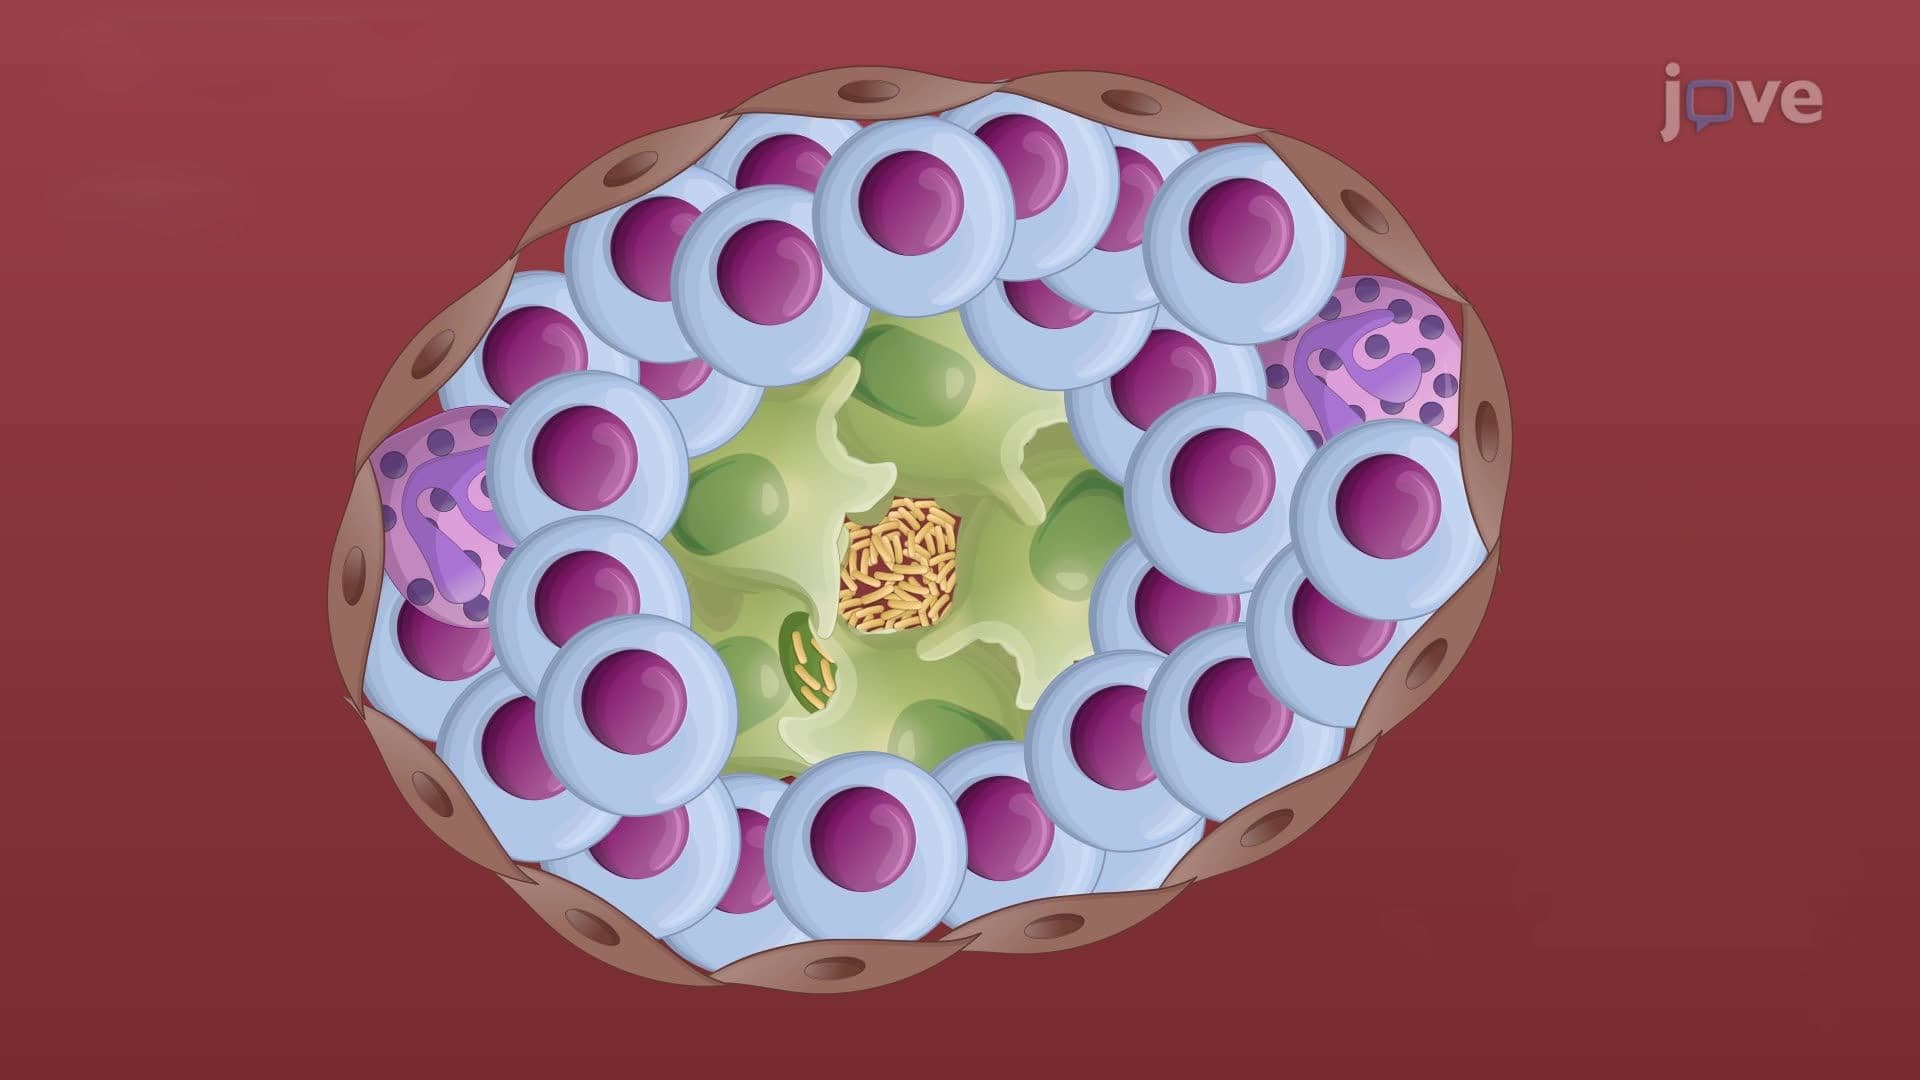
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:23
Tuberculosis
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories: