Related Experiment Video
Updated: Oct 4, 2026

Rapid Detection of Fecal Antigen of Helicobacter pylori Infection Based on Double Antibody Sandwich Detection Technology
Published on: May 23, 2025
14C urea breath test does not predict density of Helicobacter pylori in duodenal ulcer disease
D Kumar1, C S Bal, S Dattagupta
1Department of Gastroenterology, All India Institute of Medical Sciences, New Delhi, India.

Background & Objectives:
The density of Helicobacter pylori in the gastric mucosa has prognostic significance, higher densities being associated with greater chances of development of duodenal ulcer and chronic atrophic gastritis as well as poor eradication by drug therapy. The aim of this study was to assess if 14C-urea breath test counts reflect bacterial density.
Methods:
Sixty patients with endoscopically proven active duodenal ulcer and H. pylori positivity as determined by rapid urease test and gastric histology were studied. Gastric antral and corpus biopsies were graded for chronic gastritis, activity (presence of polymorphonuclear cells) and bacterial density (at surface and in pits) based on the Sydney system on a scale of four grades ranging from 0 to 3 (absent, mild, moderate and severe). 14C urea breath test was performed in all the patients.
Results:
Chronic gastritis as well as activity was more prevalent as well as severe in the antrum as compared to the corpus. H. pylori density was also significantly more in the antrum as compared to the corpus both at the surface as well as in the pits. H. pylori density correlated with the grade of chronic gastritis and activity both in the antrum and in the corpus. Urea breath test counts ranged from 331.3 cpm (counts per minute) to 8770.5 cpm and these did not correlate with histological H. pylori density at any of the sites.
Interpretation & Conclusions:
14C urea breath test does not reflect H. pylori density on histology in patients of duodenal ulcer disease.

Related Concept Videos
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:30
Serum Laboratory Studies, Stool Test, Breath Test
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 01:27
Peptic Ulcer
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:25
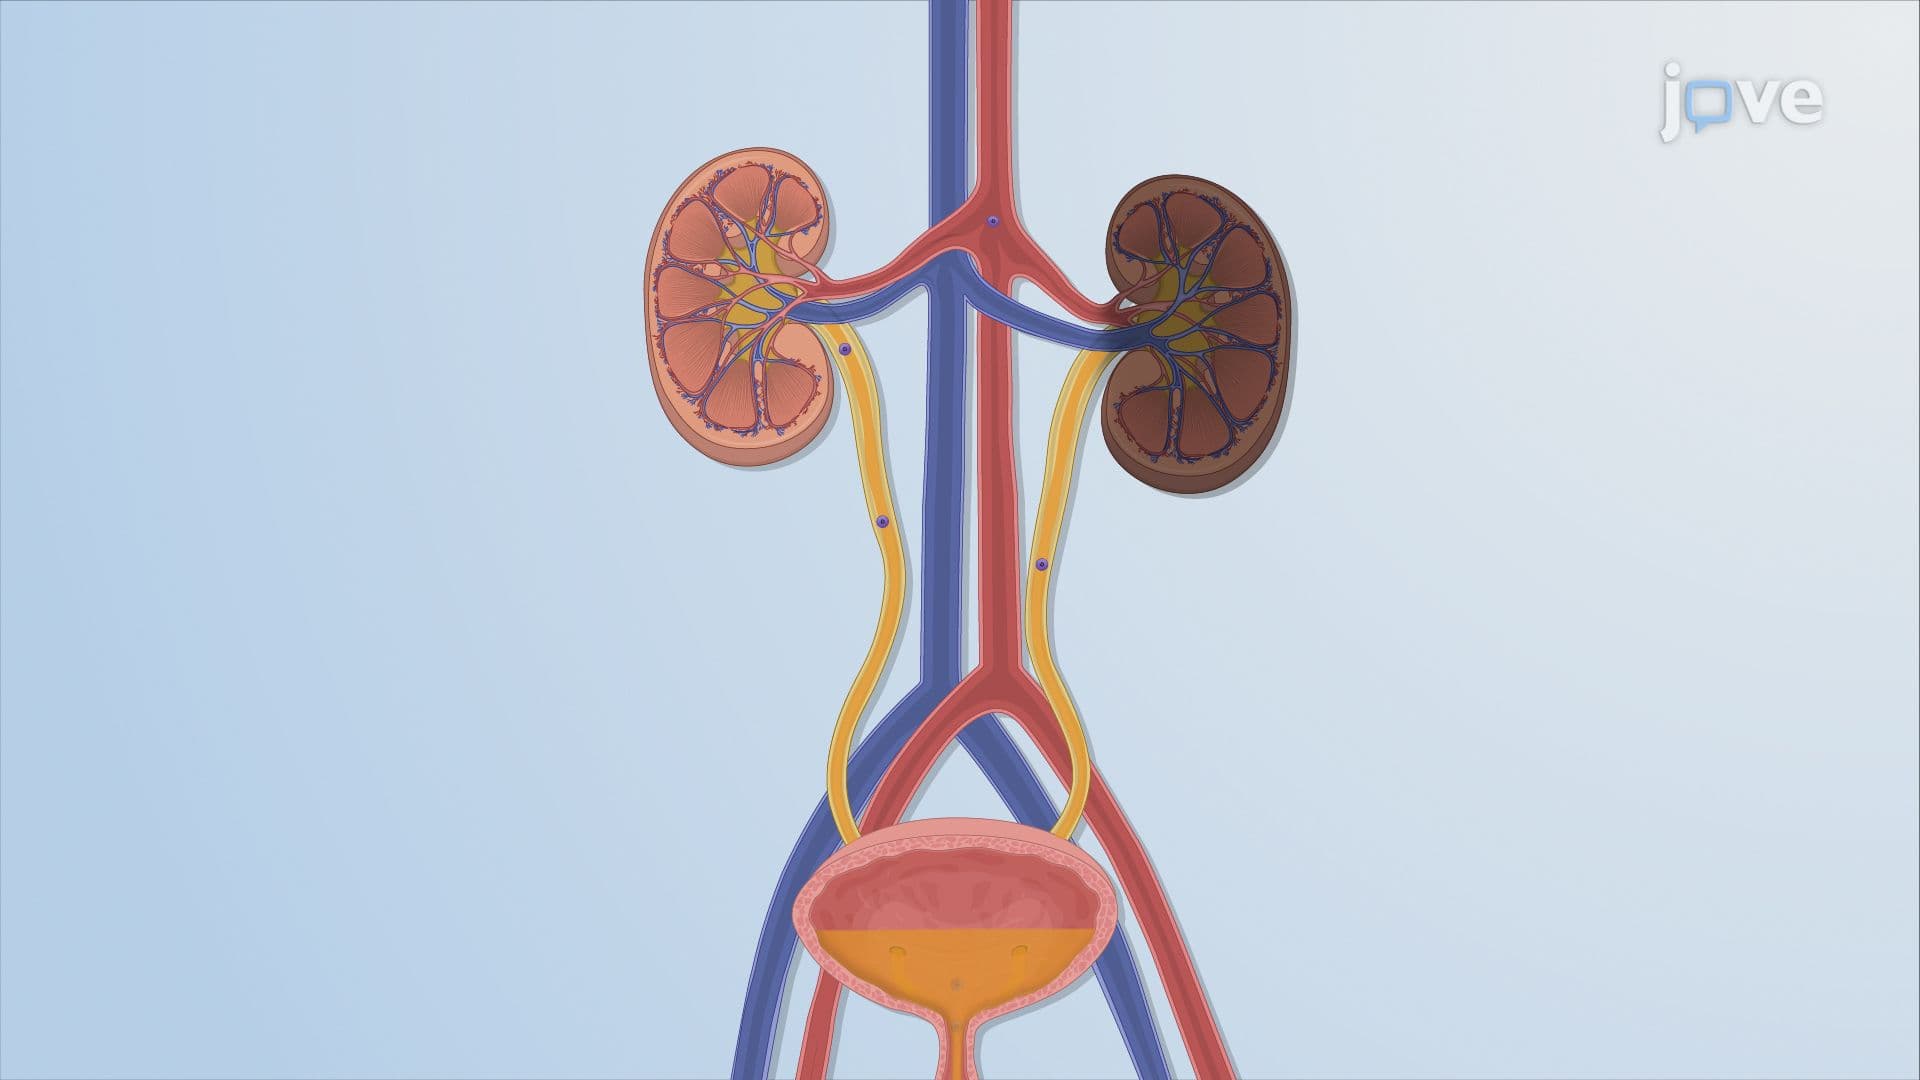
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate