Upper gastrointestinal complications: the causes, consequences, and clinical outcomes
Related Experiment Videos

Abstract:
Studies reveal that cyclooxygenase (COX-2) inhibitors seem to markedly lessen the risk of ulcers and upper gastrointestinal complications. Discussion, however, continues whether COX-2 inhibitors reduce the risk of clinical events to the same degree as nonsteroidal anti-inflammatory drugs.
Insights
Cyclooxygenase (COX-2) inhibitors significantly reduce the risk of gastrointestinal ulcers and complications. Further research is needed to confirm if they offer the same clinical event protection as traditional nonsteroidal anti-inflammatory drugs.
Area of Science:
- Gastroenterology
- Pharmacology
- Internal Medicine
Background:
- Nonsteroidal anti-inflammatory drugs (NSAIDs) are widely used for pain and inflammation.
- Traditional NSAIDs are associated with significant gastrointestinal (GI) risks, including ulcers and bleeding.
- Cyclooxygenase-2 (COX-2) selective inhibitors were developed to mitigate these GI side effects.
Purpose of the Study:
- To evaluate the effectiveness of COX-2 inhibitors in reducing the risk of ulcers and upper GI complications.
- To compare the clinical event risk reduction of COX-2 inhibitors versus traditional NSAIDs.
Main Methods:
- Review of existing studies and clinical trials.
- Analysis of patient data regarding ulcer formation and GI bleeding.
- Comparative assessment of adverse event profiles.
Main Results:
- Studies indicate that COX-2 inhibitors markedly decrease the incidence of ulcers.
- A significant reduction in upper gastrointestinal complications was observed with COX-2 inhibitor use.
- Ongoing debate exists regarding the extent of clinical event risk reduction compared to traditional NSAIDs.
Conclusions:
- COX-2 inhibitors demonstrate a clear benefit in lowering the risk of GI ulcers and related complications.
- The comparative efficacy of COX-2 inhibitors versus traditional NSAIDs in preventing major clinical events requires further investigation.
- Clinical practice guidelines may need to consider these findings for patient management.
Related Concept Videos
 01:25
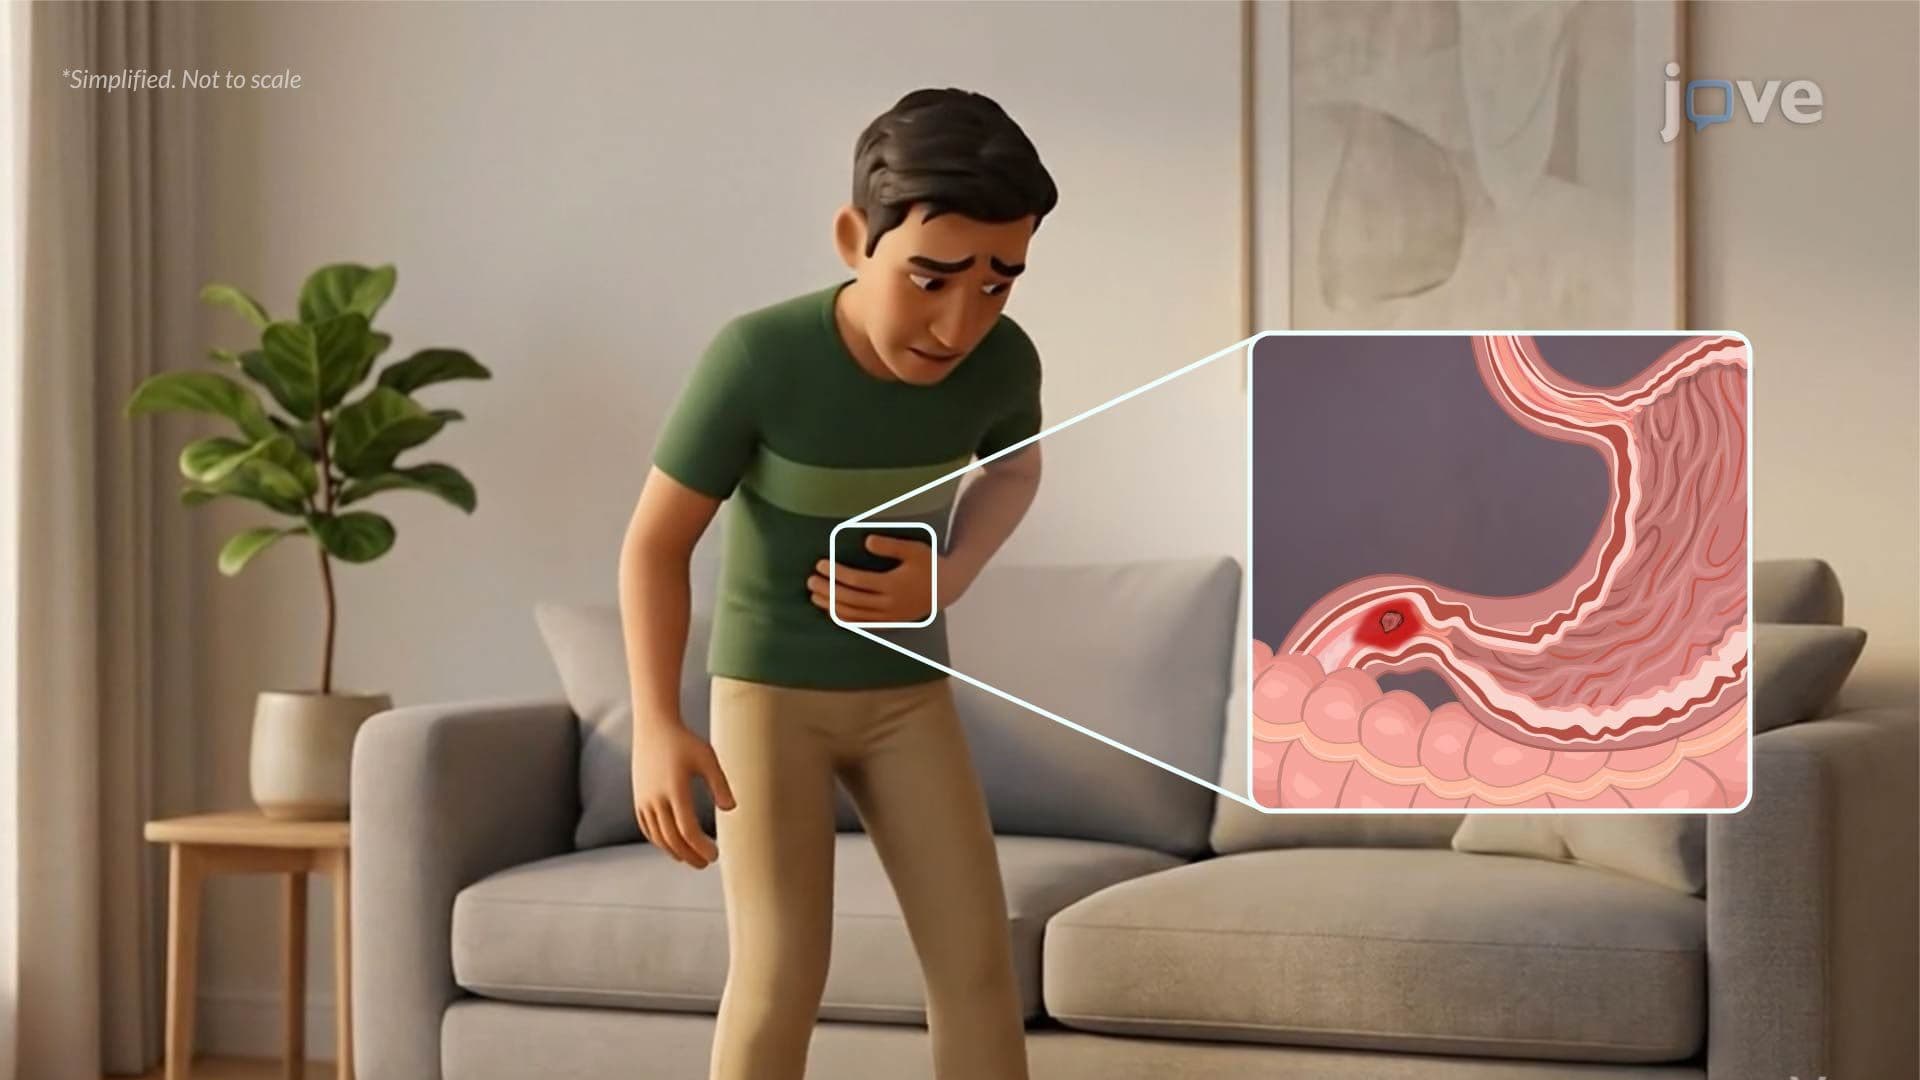
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:27
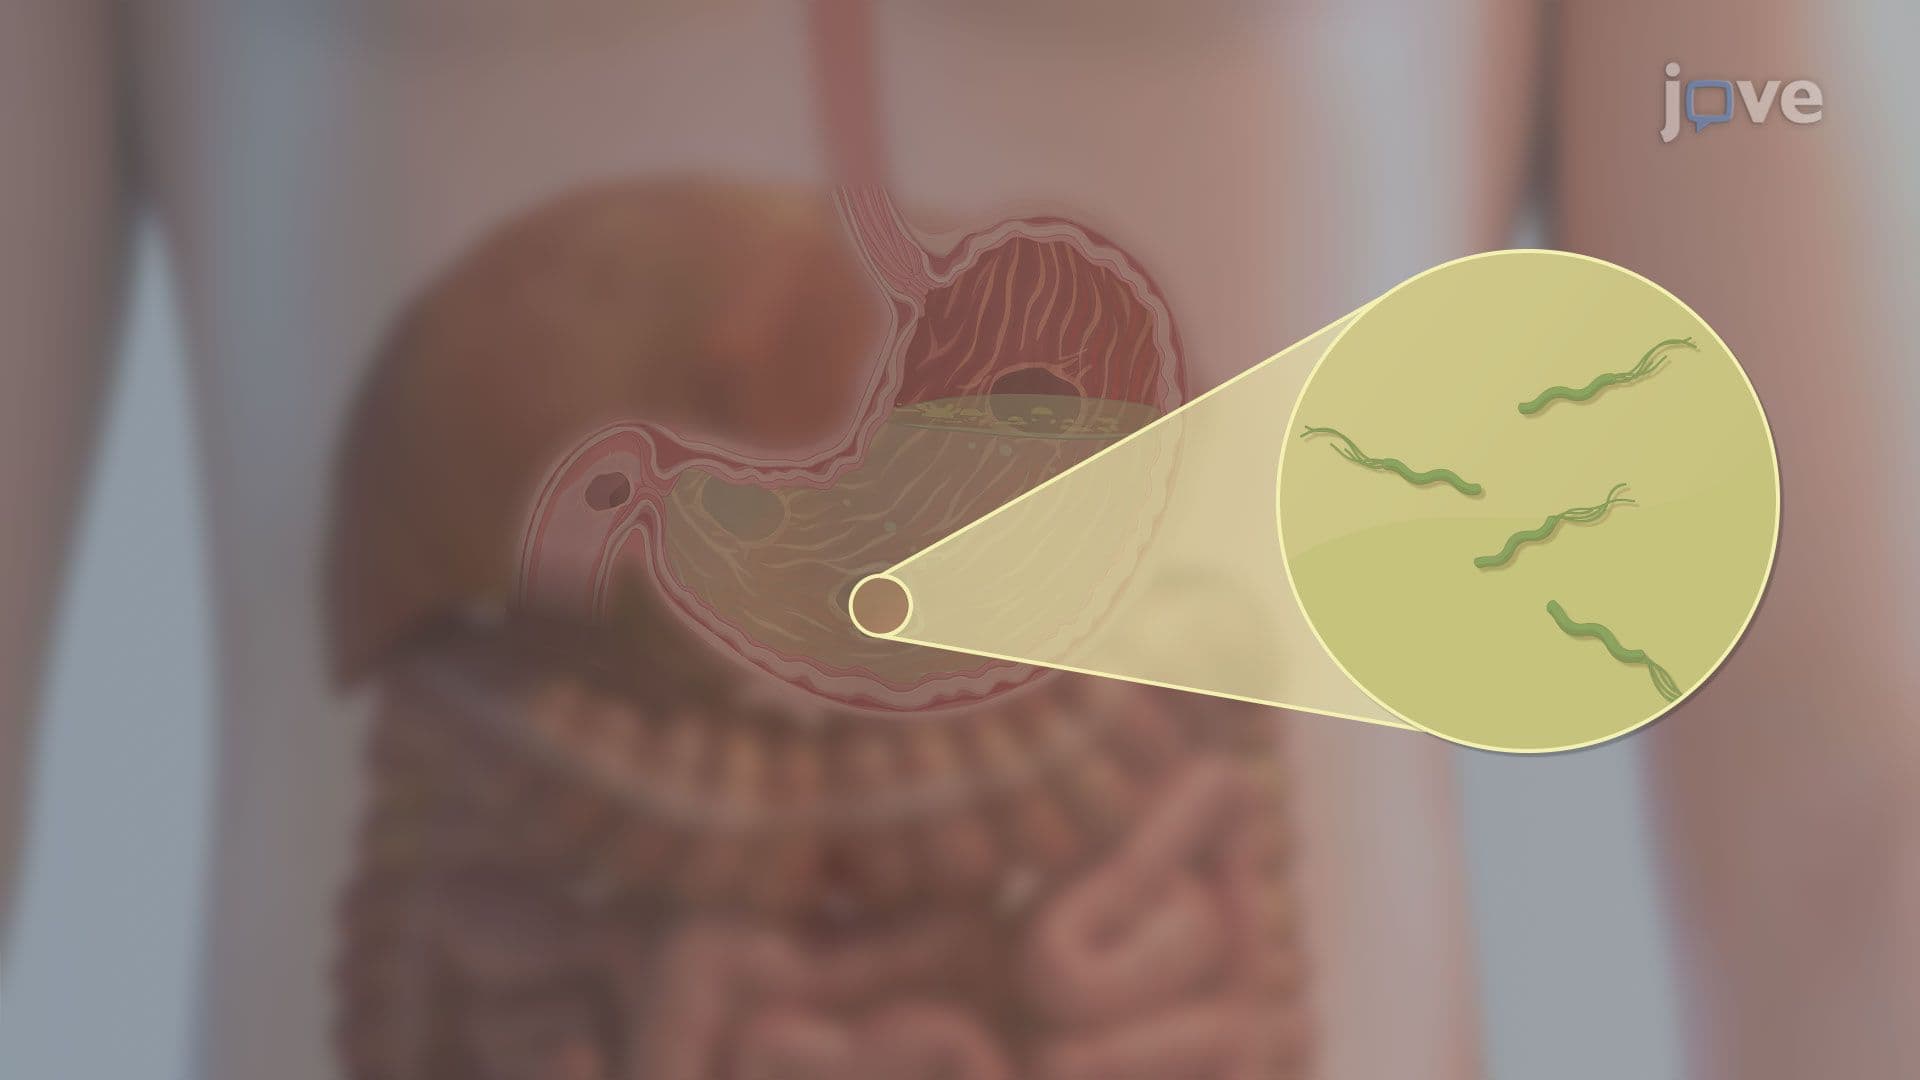
Peptic Ulcer
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:25
Gastroesophageal Reflux Disease
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease