Related Experiment Video
Updated: Oct 4, 2026
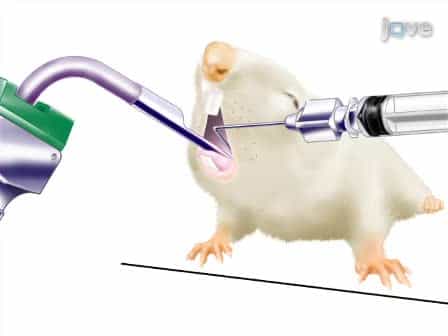
Non-surgical Intratracheal Instillation of Mice with Analysis of Lungs and Lung Draining Lymph Nodes by Flow Cytometry
Published on: May 2, 2011
Thin-section CT features of intrapulmonary lymph nodes
1Department of Radiology, Tenri Hospital, Tenri, Nara, Japan. rad053@poh.osaka-med.ac.jp

Purpose:
The objective of this study was to evaluate CT findings of pathologically proven intrapulmonary lymph nodes (IPLNs) and discuss the utility of thin-section CT and contrast-enhanced CT.
Method:
CT findings of 18 nodules in 14 patients with pathologically proven IPLNs were reviewed. CT scanning of the whole lung was performed contiguously with slice thickness of 10 mm. In addition, a helical scan with slice thickness of 2 mm was performed in nine patients, focusing on the nodule. Contrast-enhanced helical CT was performed in four patients, and the utility of thin section CT and contrast-enhanced CT was investigated.
Results:
One patient had three nodules, 2 patients had two nodules, and the remaining 11 patients had a solitary nodule. All nodules were located below the level of the carina and within 15 mm of the pleura. In one case, conventional CT revealed the nodule 20 mm away from the pleura; however, the nodule attached to the major fissure was clearly revealed on thin-section CT. The size of the nodules was < or =15 mm, and the shape was round (n = 8), oval (n = 9), or lobulated (n = 1) with sharp border. One nodule demonstrated a spiculated border due to a surrounding pulmonary fibrosis on conventional CT; however, thin-section CT showed precisely a sharp border. The lobulated shape of one case histopathologically reflected a hilus of lymph node. On contrast-enhanced helical CT, all four nodules were enhanced and the degree enhancement was 36-85 HU (median 66.6 HU).
Conclusion:
In current times, IPLNs are not uncommon lesions. We should consider IPLN in the differential diagnosis of solitary or multiple pulmonary nodules in the peripheral field and below the level of the carina. Thin-section CT showed precisely the border or relation between IPLNs and the surrounding structure. It was difficult to distinguish between IPLNs and malignant nodules from the degree of enhancement on contrast-enhanced CT. On thin-section and contrast-enhanced CT, the findings of IPLNs are not necessarily specific. Therefore, strict observation on CT is necessary; in certain cases that are increasing in size, video-assisted thoracic surgery should be considered because of their location.
Related Concept Videos
 01:23
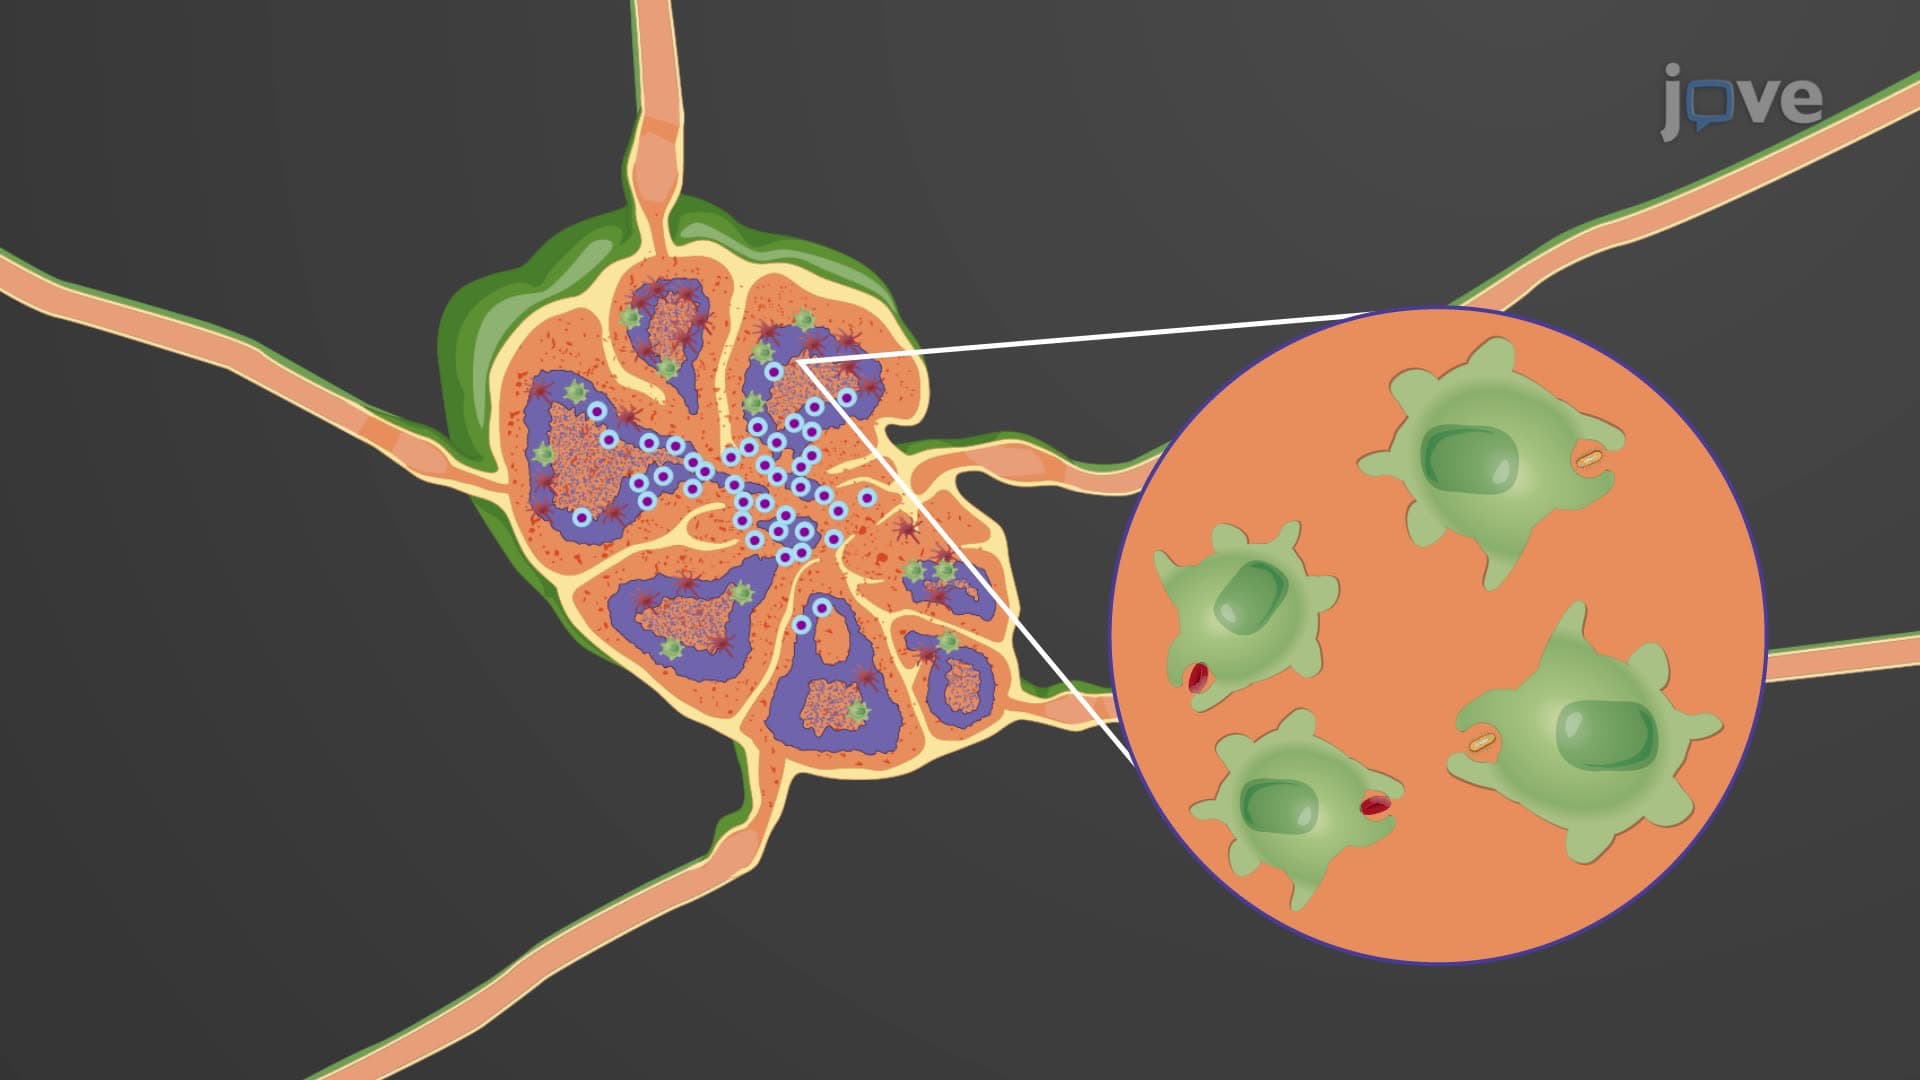
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...
 01:15
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
 01:17
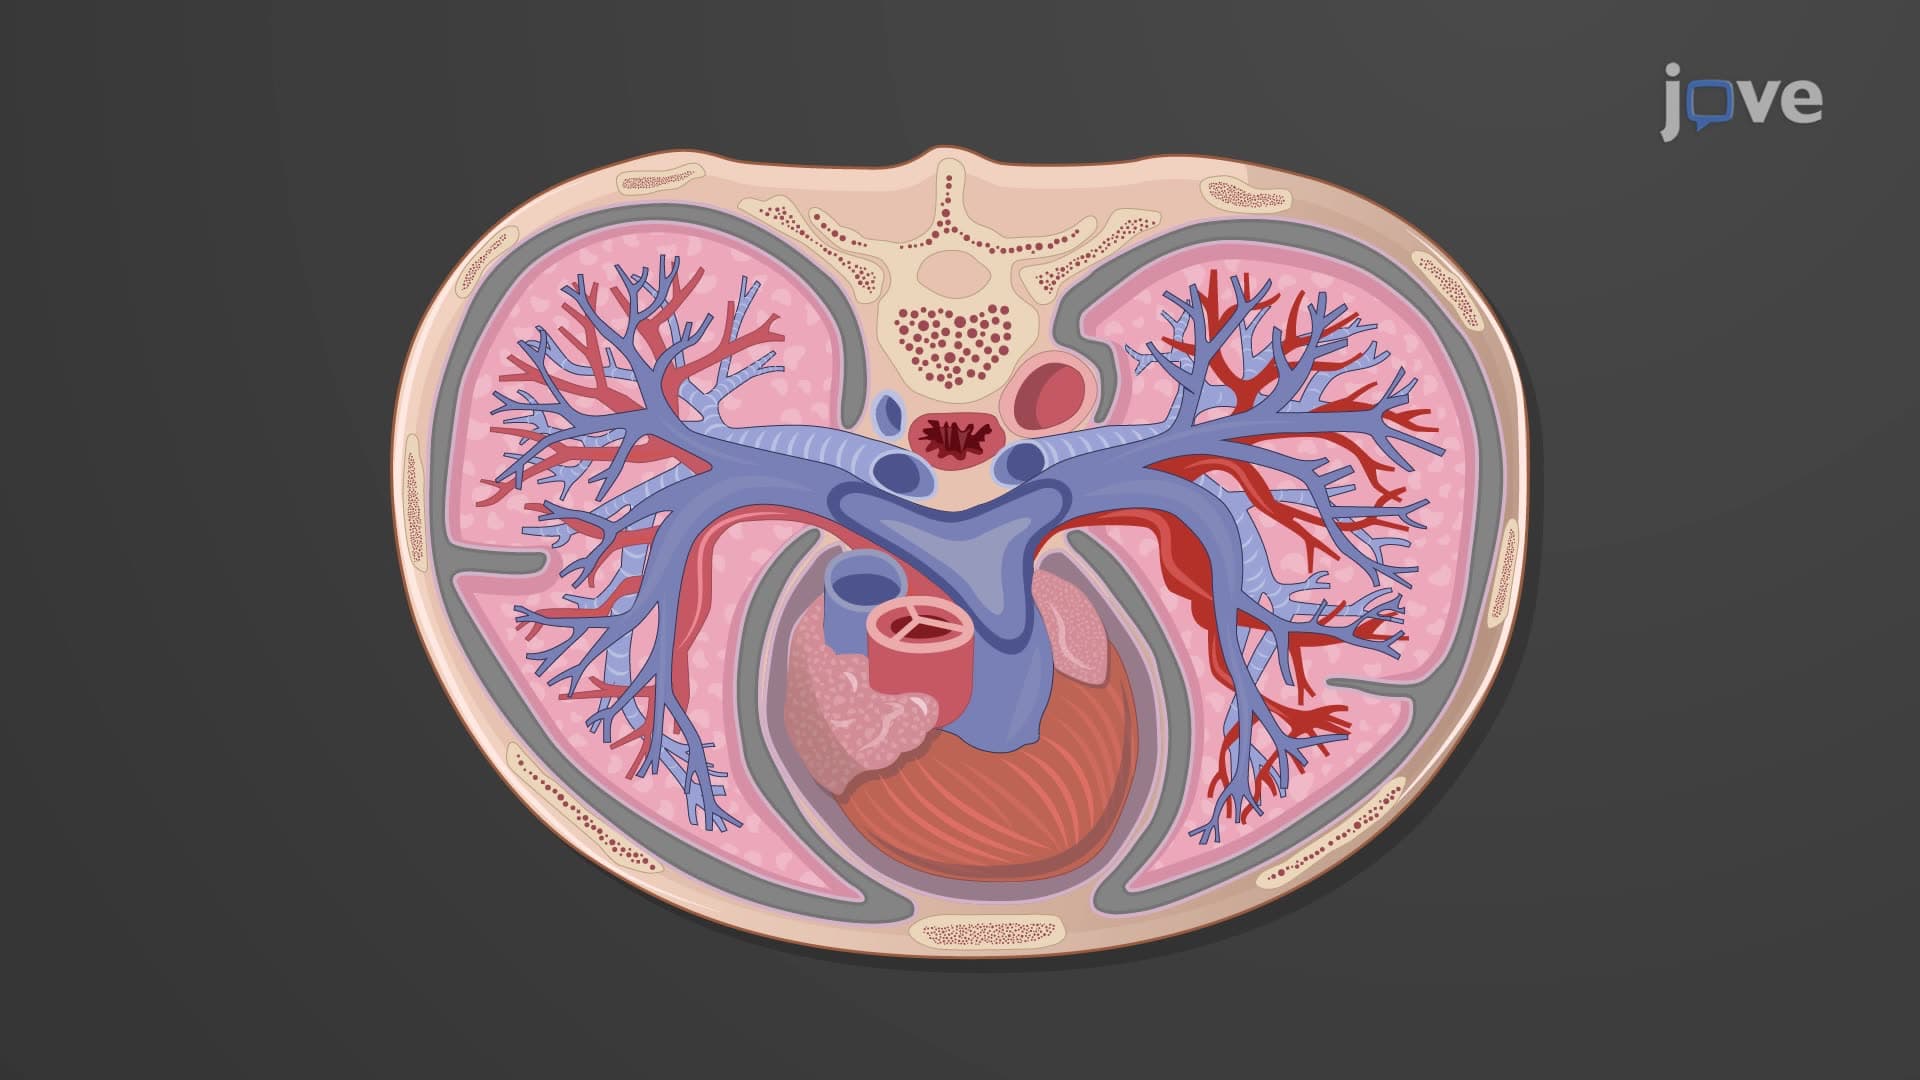
Gross Anatomy of the Lungs
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:18
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories: