Related Experiment Video
Updated: Oct 4, 2026
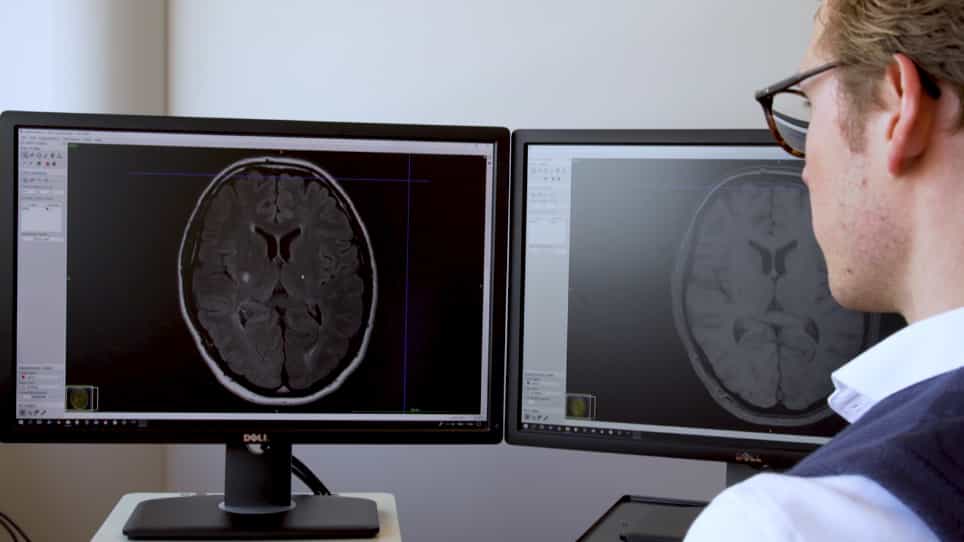
Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
Relationship between severity of MR perfusion deficit and DWI lesion evolution
V N Thijs1, A Adami, T Neumann-Haefelin
1Stanford Stroke Center, Department of Neurology and Neurological Sciences, Stanford University Medical Center, Palo Alto, CA, USA. vincent.thijs@uz.kuleuven.ac.be

Objective:
To assess whether a quantitative analysis of the severity of the early perfusion deficit on MRI in acute ischemic stroke predicts the evolution of the perfusion/diffusion mismatch and to determine thresholds of hypoperfusion that can distinguish between critical and noncritical hypoperfusion.
Methods:
Patients with acute ischemic stroke were studied in whom perfusion-weighted imaging (PWI) and diffusion-weighted imaging (DWI MRI) were performed within 7 hours of symptom onset and again after 4 to 7 days. Patients with early important decreases in points on the NIH Stroke Scale were excluded. Maps of cerebral blood flow (CBF), cerebral blood volume (CBV), and mean transit time (MTT) were created. These hemodynamic parameters were correlated with the degree of recruitment of the baseline PWI lesion by the DWI lesion.
Results:
Twelve patients had an initial PWI > DWI mismatch of >20%. A linear relationship was observed between the initial MTT and the degree of recruitment of the baseline PWI lesion by the DWI lesion at follow-up (R(2) = 0.9, p < 0.001). Higher CBV values were associated with higher degrees of recruitment (rho = 0.732, p < 0.007). The volume of MTT of >4 (R(2) = 0.86, p < 0.001) or >6 seconds (R(2) = 0.85, p < 0.001) predicted final infarct size.
Conclusion:
Among patients who have had an acute stroke with PWI > DWI, who do not have dramatic early clinical improvement, the degree of expansion of the initial DWI lesion correlates with the severity of the initial perfusion deficit as measured by the mean transit time and the cerebral blood volume.
Insights
Quantitative MRI analysis of early perfusion deficits in acute ischemic stroke predicts infarct progression. Mean transit time and cerebral blood volume thresholds help distinguish critical hypoperfusion, aiding in stroke outcome prediction.
Area of Science:
- Neurology
- Radiology
- Medical Imaging
Background:
- Acute ischemic stroke requires timely assessment of tissue viability.
- Perfusion/diffusion mismatch on MRI is crucial for guiding treatment decisions.
- Understanding the evolution of perfusion deficits is key to predicting stroke outcomes.
Purpose of the Study:
- To evaluate if early quantitative perfusion deficit severity on MRI predicts perfusion/diffusion mismatch evolution in acute ischemic stroke.
- To establish hypoperfusion thresholds for differentiating critical from non-critical states.
- To correlate perfusion parameters with final infarct size.
Main Methods:
- Retrospective analysis of acute ischemic stroke patients undergoing serial MRI (PWI and DWI).
- Exclusion of patients with rapid NIH Stroke Scale improvement.
- Creation of cerebral blood flow (CBF), cerebral blood volume (CBV), and mean transit time (MTT) maps.
- Correlation of hemodynamic parameters with PWI lesion recruitment by DWI lesion.
Main Results:
- A significant linear relationship (R(2) = 0.9) was found between initial MTT and follow-up PWI lesion recruitment by DWI.
- Higher CBV values correlated with greater lesion recruitment (rho = 0.732).
- MTT thresholds (>4 or >6 seconds) accurately predicted final infarct volume (R(2) = 0.86 and R(2) = 0.85, respectively).
Conclusions:
- In acute ischemic stroke patients with PWI > DWI mismatch and no rapid clinical improvement, initial DWI lesion expansion correlates with perfusion deficit severity.
- Mean transit time and cerebral blood volume quantify the initial perfusion deficit.
- Quantitative MRI perfusion parameters can predict infarct progression and final infarct size.