Related Experiment Video
Updated: Oct 4, 2026
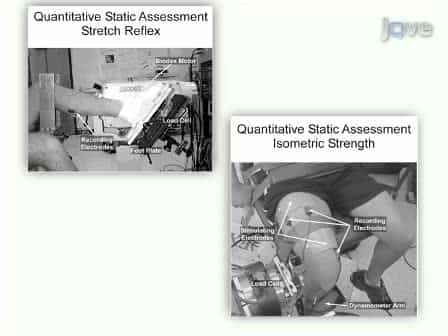

Methods to Quantify Pharmacologically Induced Alterations in Motor Function in Human Incomplete SCI
Published on: April 18, 2011
Reflexes and somatic responses as predictors of ejaculation by penile vibratory stimulation in men with spinal cord
V G Bird1, N L Brackett, C M Lynne
1Department of Urology, University of Miami School of Medicine, Miami, Florida 33101, USA.

Study Design:
Retrospective chart review.
Objective:
To identify factors in addition to level of injury (LOI) that may predict ejaculation by penile vibratory stimulation (PVS) in spinal cord injured males.
Setting:
Major urban medical school and teaching hospital.
Materials And Methods:
Presence of a bulbocavernosus response (BCR) and a hip flexor response (HR) before PVS (n=123 patients), and somatic responses during PVS (n=204 trials performed on a subset of 44 patients) were evaluated for their frequency of occurrence on trials with and without ejaculation.
Results:
Overall ejaculation success rates for cervical, T1-T6, and T7-T12 LOI were 71%, 73%, and 35%, respectively. Eighty per cent of patients who were positive for both BCR and HR ejaculated with PVS, while only 8% of patients who were negative for both BCR and HR ejaculated with PVS. For cervical injuries, BCR and HR were no more predictive of ejaculation by PVS than LOI alone. T1-T6 patients were more likely to ejaculate when at least one reflex was present. T7-T12 patients with no BCR were unlikely to ejaculate by PVS. Except for abdominal contractions, somatic responses were not present in the majority of PVS trials. When they were present, however, they occurred in a high percentage of ejaculation trials: withdrawal response (hip flexion, knee flexion and thigh adduction) (90%), piloerection (84%), extremity spasms (83%), thigh abduction (80%), and thigh adduction (72%).
Conclusion:
We recommend that patients with cervical injuries initially undergo PVS. Patients with T1-T6 LOI with at least one reflex present, and patients with T7-T12 LOI with both reflexes, or only BCR present, may undergo PVS. Certain somatic/autonomic responses, when seen, may help in deciding whether to continue with a given trial, or give a repeat trial, of PVS.
Sponsorship:
The Miami Project to Cure Paralysis and the State of Florida Specific Appropriations.
Related Concept Videos
 01:17
Male Sexual Response: Erection & Ejaculation
The blood filling the erectile tissues compresses the veins, which helps to prevent blood from leaving...
 01:22
Somatic Spinal Reflexes
One of the most well-known somatic spinal reflexes is the stretch reflex, which is activated by the sudden stretching of a muscle. This reflex involves the activation of specialized sensory receptors called muscle spindles, which are located in the muscle tissue and detect changes in the length and speed of muscle contractions. When a muscle is suddenly...
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating urine...
 01:08
Reflex Activity
A reflex exam is a diagnostic procedure performed by a healthcare professional to evaluate the functionality of a patient's...
 01:10
Spinal Cord: Information Processing
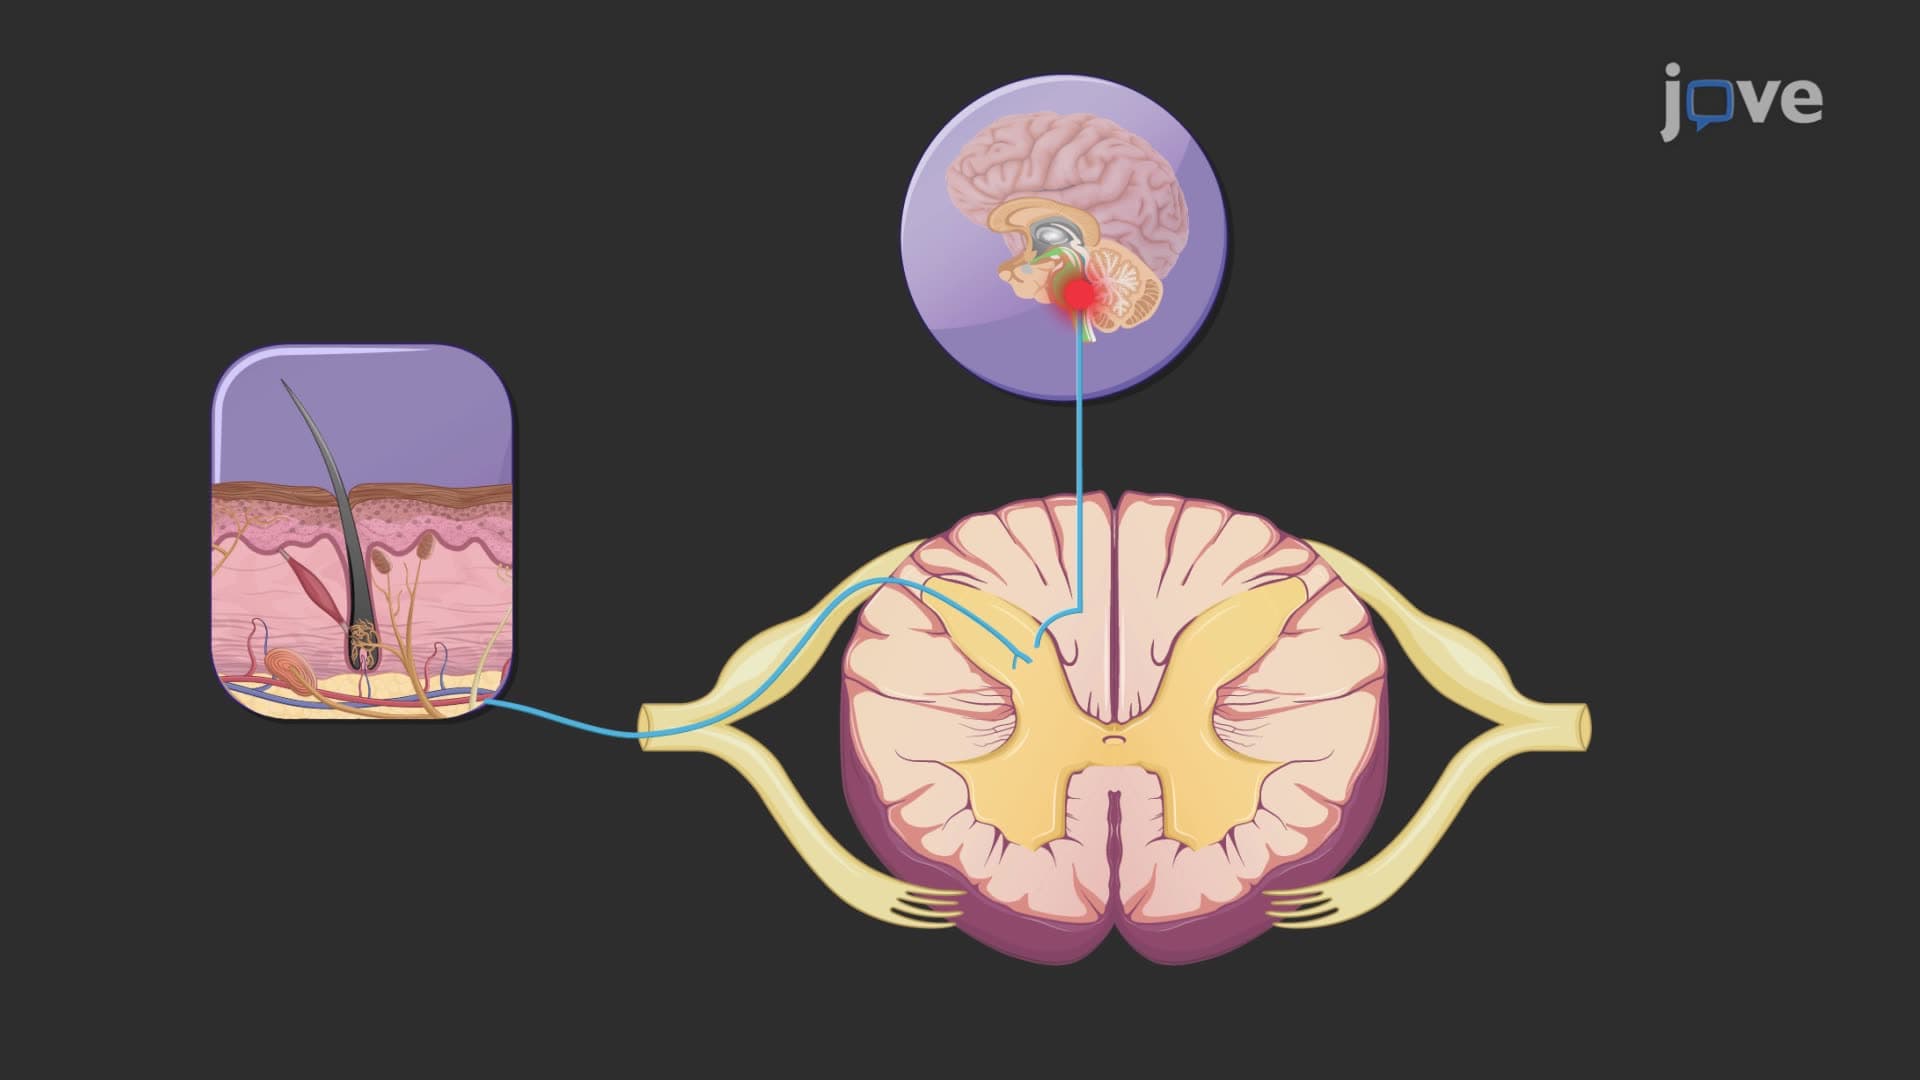
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...