Related Experiment Video
Updated: Jul 16, 2026
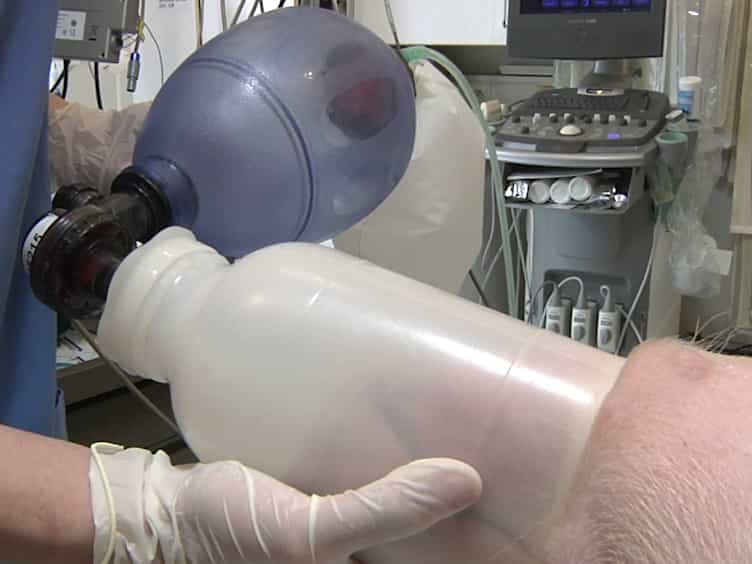

Tachycardia-Induced Cardiomyopathy As a Chronic Heart Failure Model in Swine
Published on: February 17, 2018
The muscle hypothesis: a model of chronic heart failure appropriate for osteopathic medicine
1Michigan State University College of Osteopathic Medicine, East Lansing, MI 48824-1316, USA. fjrogers@aol.com

Insights
The muscle hypothesis suggests abnormal skeletal muscles cause heart failure symptoms like breathlessness. Exercise and other therapies can improve exercise capacity and reverse muscle issues in chronic heart failure patients.
Area of Science:
- Cardiology
- Exercise Physiology
- Skeletal Muscle Biology
Background:
- Chronic heart failure (CHF) affects millions, yet a unifying hypothesis for its symptoms remains elusive.
- Conventional cardiocirculatory and neurohormonal models inadequately explain breathlessness and fatigue in CHF.
- The muscle hypothesis offers a complementary explanation, focusing on skeletal muscle dysfunction.
Purpose of the Study:
- To explore the role of skeletal muscle abnormalities in chronic heart failure.
- To evaluate the effectiveness of exercise and other interventions on CHF symptoms and skeletal muscle function.
- To propose a unifying hypothesis for CHF symptoms based on muscle dysfunction.
Main Methods:
- Review of existing literature on chronic heart failure pathophysiology and treatment.
- Analysis of the muscle hypothesis and its implications for understanding CHF symptoms.
- Comparison of exercise-based cardiac rehabilitation with pharmacological interventions.
Main Results:
- Skeletal muscle abnormalities contribute significantly to CHF symptoms, affecting at least 25% of patients.
- Exercise interventions demonstrably improve exercise capacity in CHF, surpassing effects of digitalis or ACE inhibitors.
- Exercise can reverse skeletal muscle myopathy and reduce abnormal ergoreflex activity in CHF.
Conclusions:
- The muscle hypothesis provides a valuable framework for understanding CHF symptoms beyond cardiac output limitations.
- Cardiac rehabilitation and targeted muscle training are effective strategies for managing CHF.
- Further research is warranted to explore novel interventions like osteopathic manipulative treatment for CHF.
Abstract:
Chronic heart failure is one of the most serious medical problems in the United States, affecting some 4 million persons. In spite of its common occurrence, and comprehensive literature regarding this condition, no unifying hypothesis has been accepted to explain the signs and symptoms of chronic heart failure. The cardiocirculatory and neurohormonal models place an emphasis on left ventricular ejection fraction and cardiac output and do not provide appropriate explanations for the symptoms of breathlessness and fatigue. The muscle hypothesis supplements these conventional models. It proposes that abnormal skeletal muscle in heart failure results in activation of muscle ergoreceptors, leading to an increase in ventilation and sensation of breathlessness, the perception of fatigue, and sympathetic activation. At least one fourth of patients with chronic heart failure are limited by skeletal muscle abnormalities rather than cardiac output. Cardiac rehabilitation exercise can lead to an increase in exercise capacity that is superior to that gained from digitalis or angiotensin-converting enzyme inhibitors. Exercise tends to reverse the skeletal muscle myopathy of chronic heart failure and reduces the abnormal ergoreflex. Other interventions that have been shown to have a favorable outcome include localized muscle group training, respiratory muscle training, and dietary approaches. The possibility that osteopathic manipulative treatment might be of benefit is an attractive, but untested, possibility.
More Related Videos


Related Concept Videos
 01:17
Pathophysiology of Heart Failure
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:27
Heart Failure I: Introduction
 01:29
Heart Failure II: Pathophysiology
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care