Related Experiment Video
Updated: Oct 3, 2026

Tumor Engraftment in a Xenograft Mouse Model of Human Mantle Cell Lymphoma
Published on: March 30, 2018
Blastic variant of mantle cell lymphoma: a rare but highly aggressive subtype

Abstract:
The blastic variant (BV) form of mantle cell lymphoma (MCL) is considered to be a very aggressive subtype of non-Hodgkin's lymphoma (NHL). In order to determine its clinico-biological features and response to therapy we studied 33 patients (17%) out of 187 suffering from MCL who were diagnosed with a BV of MCL. Blastic variant was diagnosed according to histopathological patterns, immunophenotyping, and bcl1 gene rearrangement and/or cyclin D1 overexpression. Three patients initially diagnosed with large cell NHL were classified as BV. Patients received front-line therapy including CHOP-like regimen or CVP (n = 29), or chlorambucil (n = 4) and CHOP or ESAP as second-line therapy. High-dose intensification with stem cell transplantation (SCT) was performed in 11 cases (autoSCT, n = 8; alloSCT, n = 3). All but two patients were in complete remission (CR) at the time of transplant (CR1, n = 5; CR2, n = 4). Clinical and biological characteristics did not differ from those of the common form of MCL. The median age was 62 years (29-80), with a sex ratio (M/F) of 2.6:1. Of the 33 patients, 66% had extranodal site involvement, 85% had an Ann Arbor stage IV, and 82% had peripheral lymphadenopathy. Circulating lymphomatous cells were seen in 48% of cases. Twelve patients (36%) entered a CR1 with a median duration of 11 months. Fifteen patients (46%) failed to respond and rapidly died of progressive disease. Second-line therapy led to a 26% (6/23) CR2 rate. Nine patients relapsed after high-dose therapy. Twenty-two of the 33 patients (66%) died of refractory or progressive disease. Median overall survival (OS) time was 14.5 months for the 33 BV patients as compared to 53 months for the 154 patients with a common form of MCL, P <0.0001. In the univariate analysis, OS was influenced by age, extranodal site involvement, circulating lymphomatous cells, and international prognosis index (IPI). In the multivariate analysis, only IPI affected OS: patients with IPI > or =2 had 8 months median OS as compared to 36 months median OS for patients with IPI <2, P = 0.003. Blastic variant is one of the worst forms of NHL. An improved recognition of BV of MCL is required, particularly in high-grade CD5+ NHL using immunophenotyping and bcl1 molecular study. Standard therapy using anthracycline or even high-dose intensification produce poor results and an alternative treatment should be proposed to such patients.

Related Concept Videos
 01:27
Disorders of Leukocytes
Leukopenia may result from bone marrow disorders, autoimmune diseases, and infectious diseases. For example, conditions such as multiple myeloma and aplastic anemia can impair the bone marrow's ability to produce adequate leukocytes. Similarly, autoimmune diseases like lupus and viral infections such as HIV can prompt the immune system...
 01:24
B Cell Activation and Differentiation
When naive B cells encounter a specific antigen that can bind to the B cell receptor (BCR) on their surface, they undergo sensitization to respond to the antigen's presence. Sensitization begins with...
 01:23
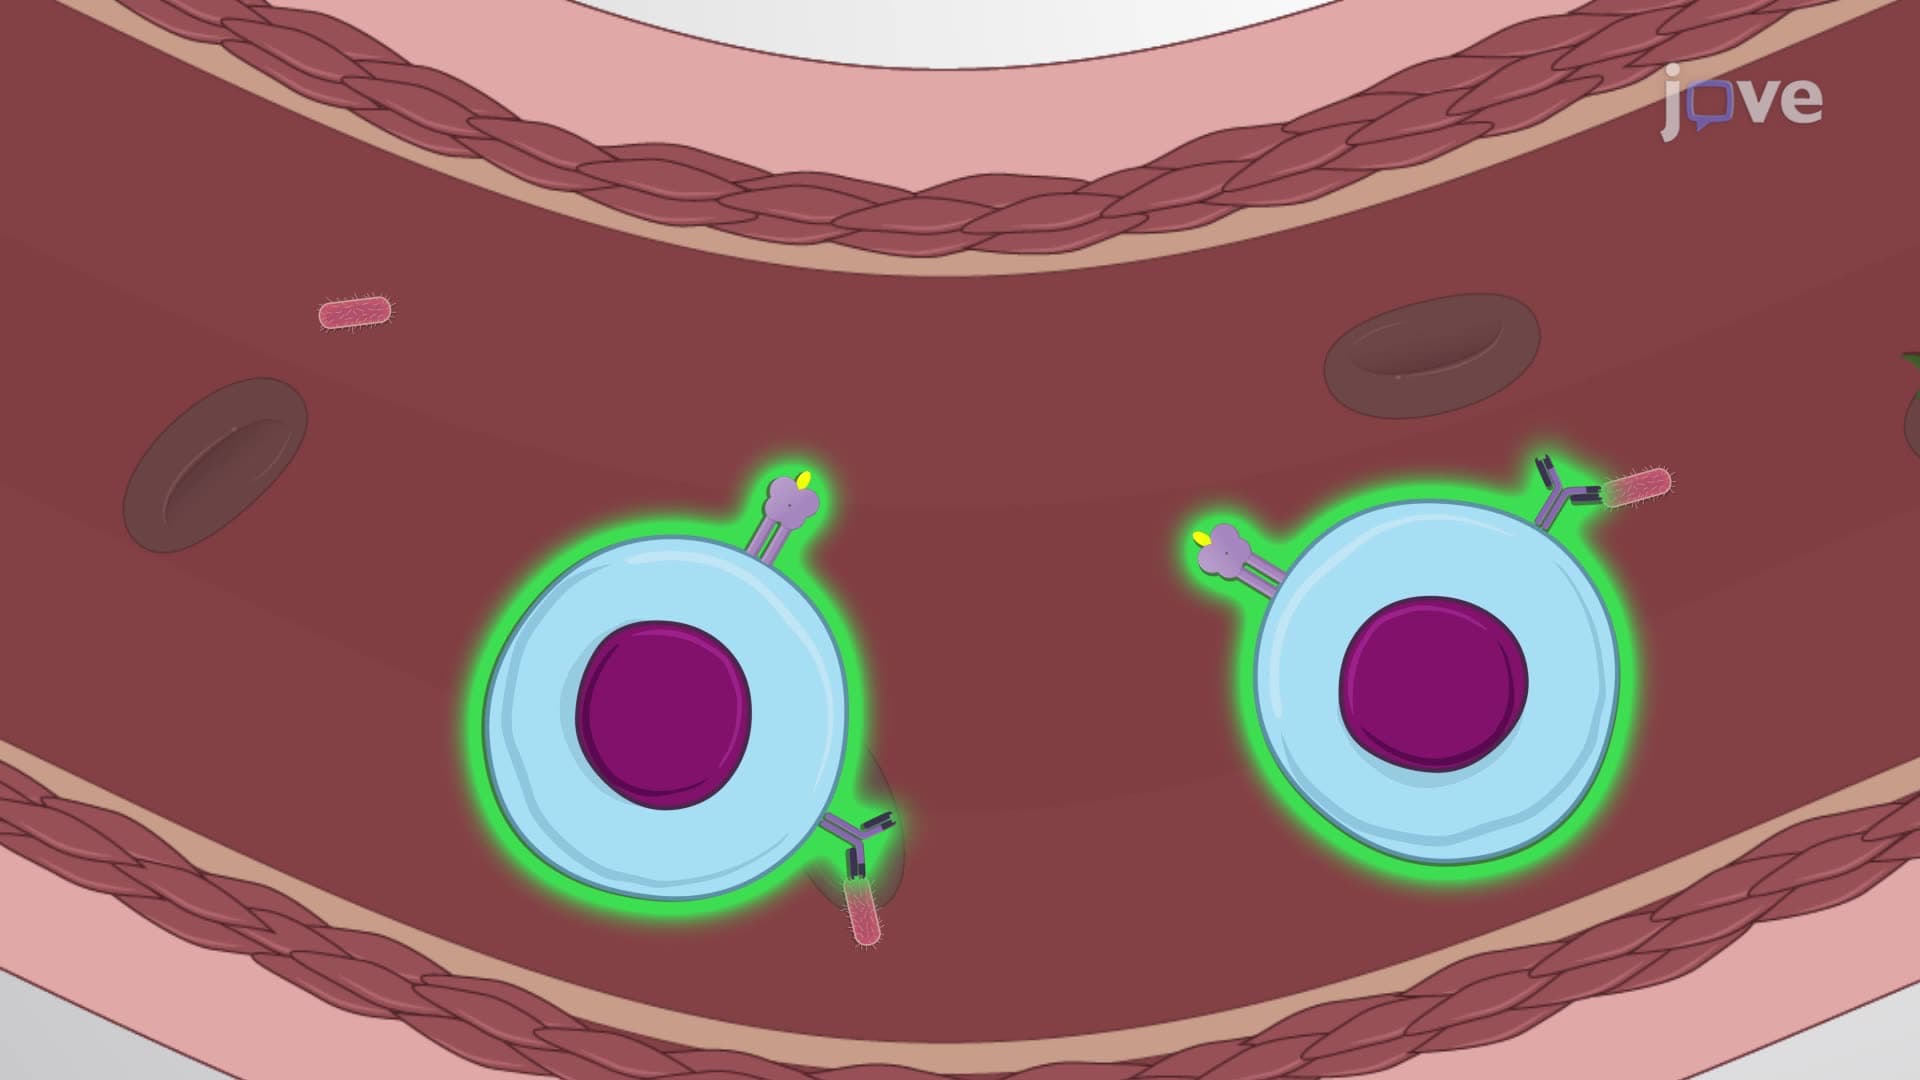
Cells of the Adaptive Immune Response
 01:15
Differentiation of Common Myeloid Progenitor Cells
 02:30
Metastasis
Epithelial-to-Mesenchymal Transition
The epithelial-to-mesenchymal transition or EMT is a developmental process commonly observed in wound healing, embryogenesis, and cancer metastasis. EMT is induced by transforming growth factor-beta (TGF-β) or receptor tyrosine kinase (RTK) ligands, which further...