Azoles for allergic bronchopulmonary aspergillosis associated with asthma
Related Experiment Video
Updated: Oct 3, 2026
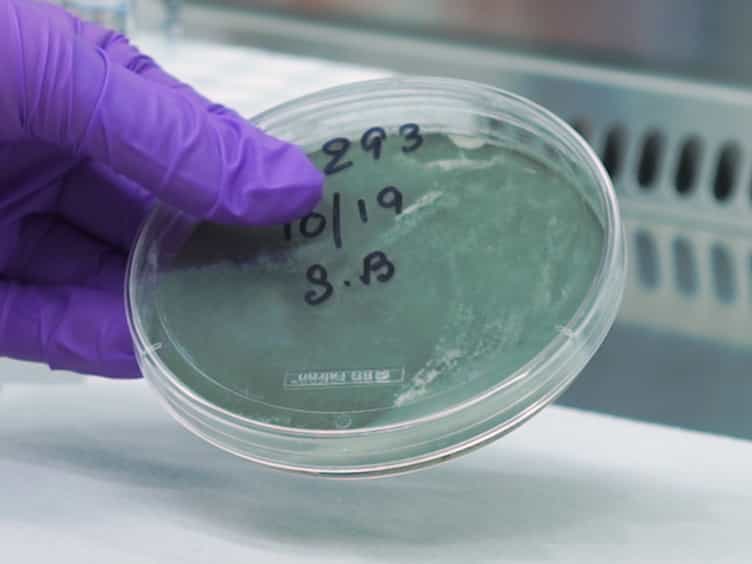
Histological Quantification to Determine Lung Fungal Burden in Experimental Aspergillosis
Published on: March 9, 2018
P Wark1, A W Wilson, P G Gibson
1Department of Respiratory Medicine, John Hunter Hospital, Locked Bag No 1, Hunter Region Mail Centre, NSW, Australia, 2310. pwark@mail.newcastle.edu.au

Background:
Allergic Broncho-pulmonary Aspergillosis is hypersensitivity to the fungus Aspergillus fumigatus that complicates patients with asthma and cystic fibrosis. The mainstay of treatment for ABPA remains oral corticosteroids, though this does not completely prevent exacerbations and may not prevent the decline in lung function.
Objectives:
The purpose of this review was to determine the efficacy of azoles in the treatment of Allergic Broncho-pulmonary Aspergillosis.
Search Strategy:
The Cochrane Airways Group Asthma register was searched using the terms: (allergic bronchopulmonary aspergillosis OR aspergillosis OR allergic pulmonary aspergillosis OR allergic fungal and disease OR allergic mycotic and disease) AND (azole OR triazole OR itraconazole OR ketoconazole).
Selection Criteria:
All controlled trials that assessed the effect of azole antifungal agents compared to placebo or other standard therapy for ABPA were reviewed. Patients with cystic fibrosis were not included.
Data Collection And Analysis:
All identified trials were independently reviewed by both reviewers & all data collected. Trial quality was scored by the Cochrane assessment of allocation concealment & the Jadad scale of methodological quality.
Main Results:
Twelve trials were identified, but only three were prospective, randomised and controlled. One demonstrated a reduction in immunological markers of disease activity and symptom scores using ketoconazole 400 mg daily for 12 month. There was no significant improvement in lung function. The other two examined the use of itraconazole for 16 weeks. In one there was a reduction in sputum eosinophils by 35% compared to 19% with placebo (p<0.01). In the same trial, the number of exacerbations requiring oral corticosteroids was 0.4 per patient with itraconazole compared with 1.3 per patient with placebo (p<0.03). Meta analysis of data from both trials showed that itraconazole treated patients were more likely to have decline in serum IgE over 25% or more (Odds Ratio 3.3; 95% confidence intervals 1.3, 8.2).
Reviewer'S Conclusions:
Itraconazole modifies the immunologic activation associated with ABPA and improves clinical outcome in ABPA at least over the period of 16 weeks.

Related Concept Videos
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms:
 01:25
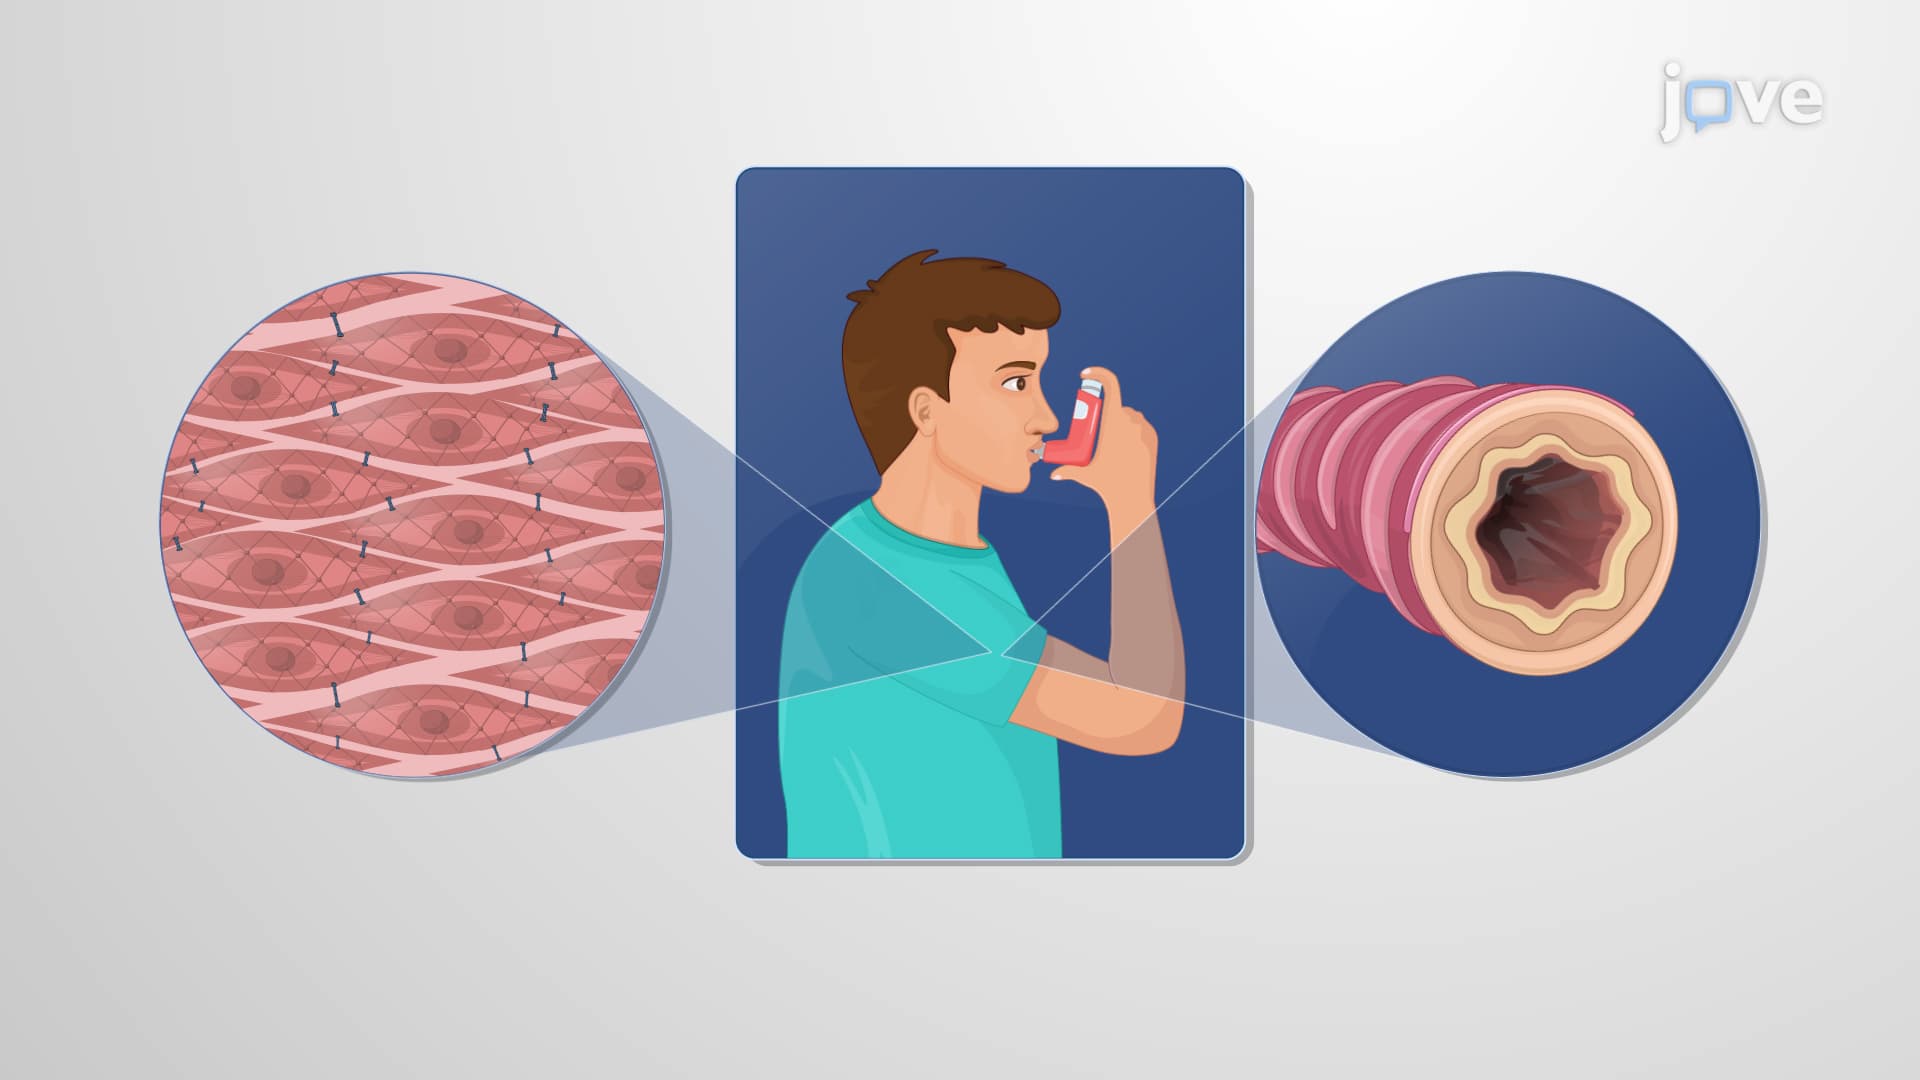
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:20
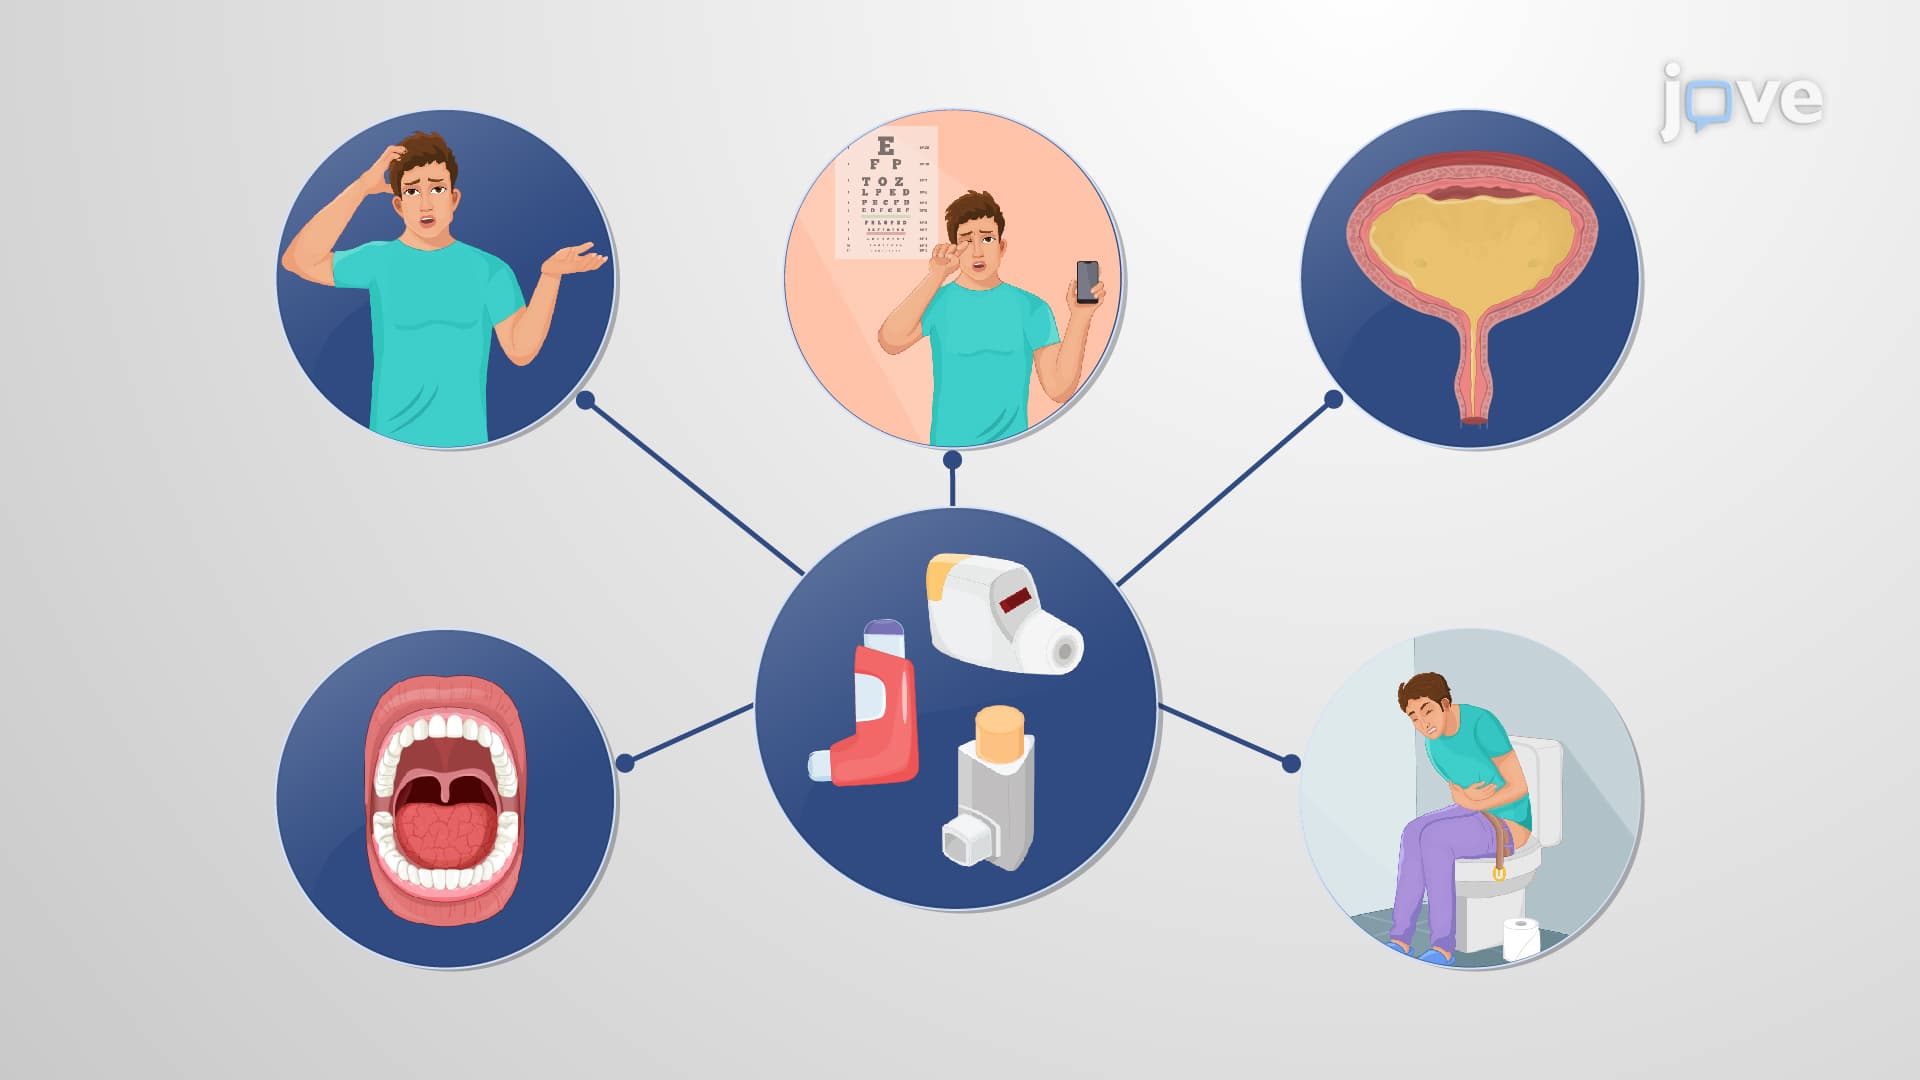
Antiasthma Drugs: Muscarinic Receptor Antagonists
Antimuscarinic agents compete with ACh for the same binding site on the muscarinic receptors. By binding to these receptors, they inhibit the downstream effects of ACh and block the parasympathetic...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.