Platelet glycoprotein IIb/IIIa blockers for percutaneous coronary revascularization, and unstable angina and non-ST-segment elevation myocardial infarction
Related Experiment Video
Updated: Aug 15, 2026
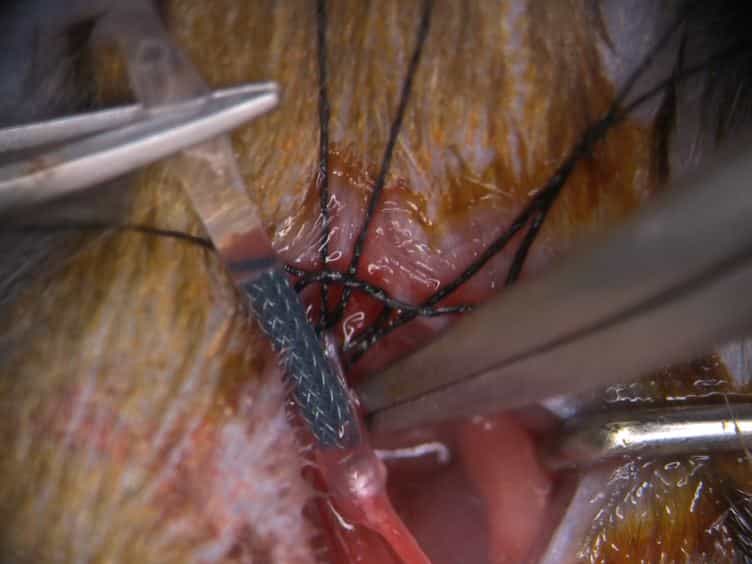
A Murine Model of Stent Implantation in the Carotid Artery for the Study of Restenosis
Published on: May 14, 2013
1Institute de Malaties Cardiovasculars, University of Barcelona, Hospital Clinic, Villarroel, 170, Barcelona, Spain, E-08036. xbosch@medicina.ub.es

Insights
Glycoprotein IIb/IIIa blockers significantly reduce mortality and myocardial infarction risk in percutaneous coronary revascularisation patients. However, these agents do not decrease mortality in unstable angina/non-ST-segment elevation myocardial infarction patients, despite a slight reduction in death or MI risk.
Area of Science:
- Cardiology
- Pharmacology
- Clinical Trials
Background:
- High risk of thrombosis during percutaneous coronary revascularisation (PTCR) and in unstable angina/non-ST-segment elevation myocardial infarction (UA/NSTEMI) despite aspirin and heparin.
- Glycoprotein (GP) IIb/IIIa antagonists inhibit platelet aggregation, potentially preventing mortality and myocardial infarction.
Purpose of the Study:
- To evaluate the efficacy and safety of GP IIb/IIIa blockers in patients undergoing PTCR.
- To assess the effectiveness and safety of GP IIb/IIIa blockers in patients with UA/NSTEMI.
Main Methods:
- Systematic review and meta-analysis of randomized controlled trials.
- Searched Cochrane Library, MEDLINE, EMBASE, and congress abstracts.
- Included trials comparing intravenous GP IIb/IIIa blockers with standard medical treatment.
Main Results:
- For PTCR: Reduced 30-day mortality (OR 0.71) and mortality/infarction at 30 days and 6 months (OR 0.62, 0.65), with increased severe bleeding (OR 1.38).
- For UA/NSTEMI: No reduction in 30-day or 6-month mortality, but decreased mortality/infarction at 30 days and 6 months (OR 0.91, 0.88), with increased severe bleeding (OR 1.27).
Conclusions:
- Intravenous GP IIb/IIIa blockers decrease 30-day mortality and significantly reduce death or MI risk in PTCR patients, at the cost of increased severe bleeding.
- In UA/NSTEMI patients, GP IIb/IIIa blockers do not reduce mortality but offer a slight decrease in death or MI risk, with a small increase in severe bleeding.
Background:
During percutaneous coronary revascularisation (i.e. coronary angioplasty (PTCA) with or without stent implantation), and in unstable angina/non-ST-segment elevation myocardial infarction, the risk of acute vessel occlusion by thrombosis is high in spite of treatment with aspirin and heparin. GP IIb/IIIa antagonists inhibit platelet aggregation and may prevent mortality and myocardial infarction.
Objectives:
To assess the efficacy and safety of GP IIb/IIIa blockers during percutaneous coronary revascularisation, and in patients with unstable angina/non-ST-segment elevation myocardial infarction.
Search Strategy:
We searched the Cochrane Library (issue 1, 2000), MEDLINE (1966 to June 2001), EMBASE (1980 to Nov 1999), reference list of articles, medical websites and handsearch among abstracts from cardiology congresses.
Selection Criteria:
Randomized controlled trials comparing intravenous GP IIb/IIIa blockers with standard medical treatment during percutaneous coronary revascularisation, and in patients with unstable angina/non-ST-segment elevation myocardial infarction.
Data Collection And Analysis:
A list of titles and abstracts was screened separately by two reviewers who assessed trial quality and extracted data.
Main Results:
Percutaneous coronary revascularisation: Fourteen trials involving 17,788 patients were included. GP IIb/IIIa blockers were associated with decreased mortality at 30 days (OR 0.71 (95% CI 0.52, 0.97)) but not at 6 months (OR 0.85 (0.66, 1.11)). Mortality or infarction was decreased both at 30 days (OR 0.62 (0.55, 0.70); ARR: 31 per 1,000), and at 6 months (OR 0.65 (0.58, 0.73); ARR: 38 per 1,000)), but severe bleeding was increased (10 per 1,000; OR 1.38 (1.04, 1.85)). Unstable angina/non-ST-segment elevation myocardial infarction: Eight trials involving 30,006 patients were included. GP IIb/IIIa blockers were not associated with decreased mortality at 30 days (OR 0.90 (0.80, 1.02)) or at 6 months (OR: 1.01 (0.88, 1.16)). Mortality or infarction was decreased at 30 days (OR 0.91 (0.85, 0.98); ARR: 13 per 1,000)) and at 6 months (OR 0,88 (0.81, 0.95); ARR: 13 per 1,000)), although severe bleeding was increased (1 per 1,000; OR 1.27 (1.12, 1.44)).
Reviewer'S Conclusions:
Intravenous GP IIb/IIIa blockers reduce the risk of death at 30 days and markedly that of death or MI at 30 days and 6 months in patients submitted to percutaneous coronary revascularisation at a price of a moderate increased risk of severe bleeding. In contrast, in patients with unstable angina/non-ST-segment elevation myocardial infarction, these agents do not reduce mortality, only slightly reduce the risk of death or MI, and slightly increase the risk for severe bleeding.
Related Concept Videos
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:30
Acute Coronary Syndrome I: Introduction
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care