Related Experiment Video
Updated: Oct 3, 2026


Repeated Transcranial Magnetic Stimulation Combined with Action Observation Training in Children with Spastic Cerebral Palsy
Published on: August 9, 2024
Use of rapacuronium in a child with spinal muscular atrophy
1Anesthesia Research Service 151, VA Medical Center, Milwaukee, WI, USA. astucke@mcw.edu

Insights
This case study details the first use of a neuromuscular blocking agent in a child with spinal muscular atrophy (SMA). Rapacuronium administration showed partial recovery, highlighting challenges in monitoring SMA patients during anesthesia.
Area of Science:
- Anesthesiology
- Neurology
- Pediatrics
Background:
- Spinal muscular atrophy (SMA) is a genetic neuromuscular disorder affecting motor neurons, leading to progressive muscle weakness.
- Anesthesia management in pediatric SMA patients presents unique challenges due to potential respiratory and bulbar muscle involvement.
- Nondepolarizing neuromuscular blocking agents (NDNMBA) are used in anesthesia, but their effects in SMA patients require careful consideration.
Observation:
- An 18-month-old girl with SMA experienced laryngospasm during anesthesia induction and received rapacuronium.
- Post-administration, diaphragmatic function showed recovery within 15 minutes, and adequate respiratory efforts were observed upon emergence.
- Diminished upper extremity muscle strength persisted, necessitating continued intubation until strength returned to baseline.
Findings:
- Train of four (TOF) monitoring during recovery was equivocal, indicating potential limitations in assessing neuromuscular blockade in SMA.
- Differential muscle group involvement in SMA can render standard TOF monitoring unreliable for predicting upper airway muscle function.
- This is the first reported instance of using an NDNMBA in a pediatric patient with SMA.
Implications:
- Careful clinical assessment and prolonged monitoring may be necessary for SMA patients recovering from anesthesia.
- Standard neuromuscular monitoring techniques might be insufficient in SMA, necessitating alternative assessment strategies.
- Further research is warranted to establish optimal anesthetic and monitoring protocols for pediatric SMA patients receiving neuromuscular blocking agents.
Abstract:
We report the case of an 18-month-old girl with spinal muscular atrophy (SMA) that received 1 mg x kg(-1) rapacuronium for laryngospasm during induction of anaesthesia. Within 15 min, we observed some diaphragmatic recovery and, after emergence from anaesthesia, the child demonstrated adequate respiratory efforts. However, the child showed diminished strength of the upper extremity muscles. Since the preoperative workup had revealed bulbar symptoms and laryngeal function could not be easily assessed, the patient was kept intubated until upper extremity strength had returned to preoperative levels. Small doses of midazolam had been given to reduce the patient's anxiety but the patient was extubated within 5 h without any complications. Train of four (TOF) monitoring of the right adductor pollicis muscle, performed during anaesthetic recovery, was equivocal. In SMA, muscle groups are differentially affected so that TOF responses may be inconclusive and not reflect the state of the upper airway muscles. To our knowledge, this is the first report of use of a nondepolarizing neuromuscular blocking agent in a child with SMA.

Related Concept Videos
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:17
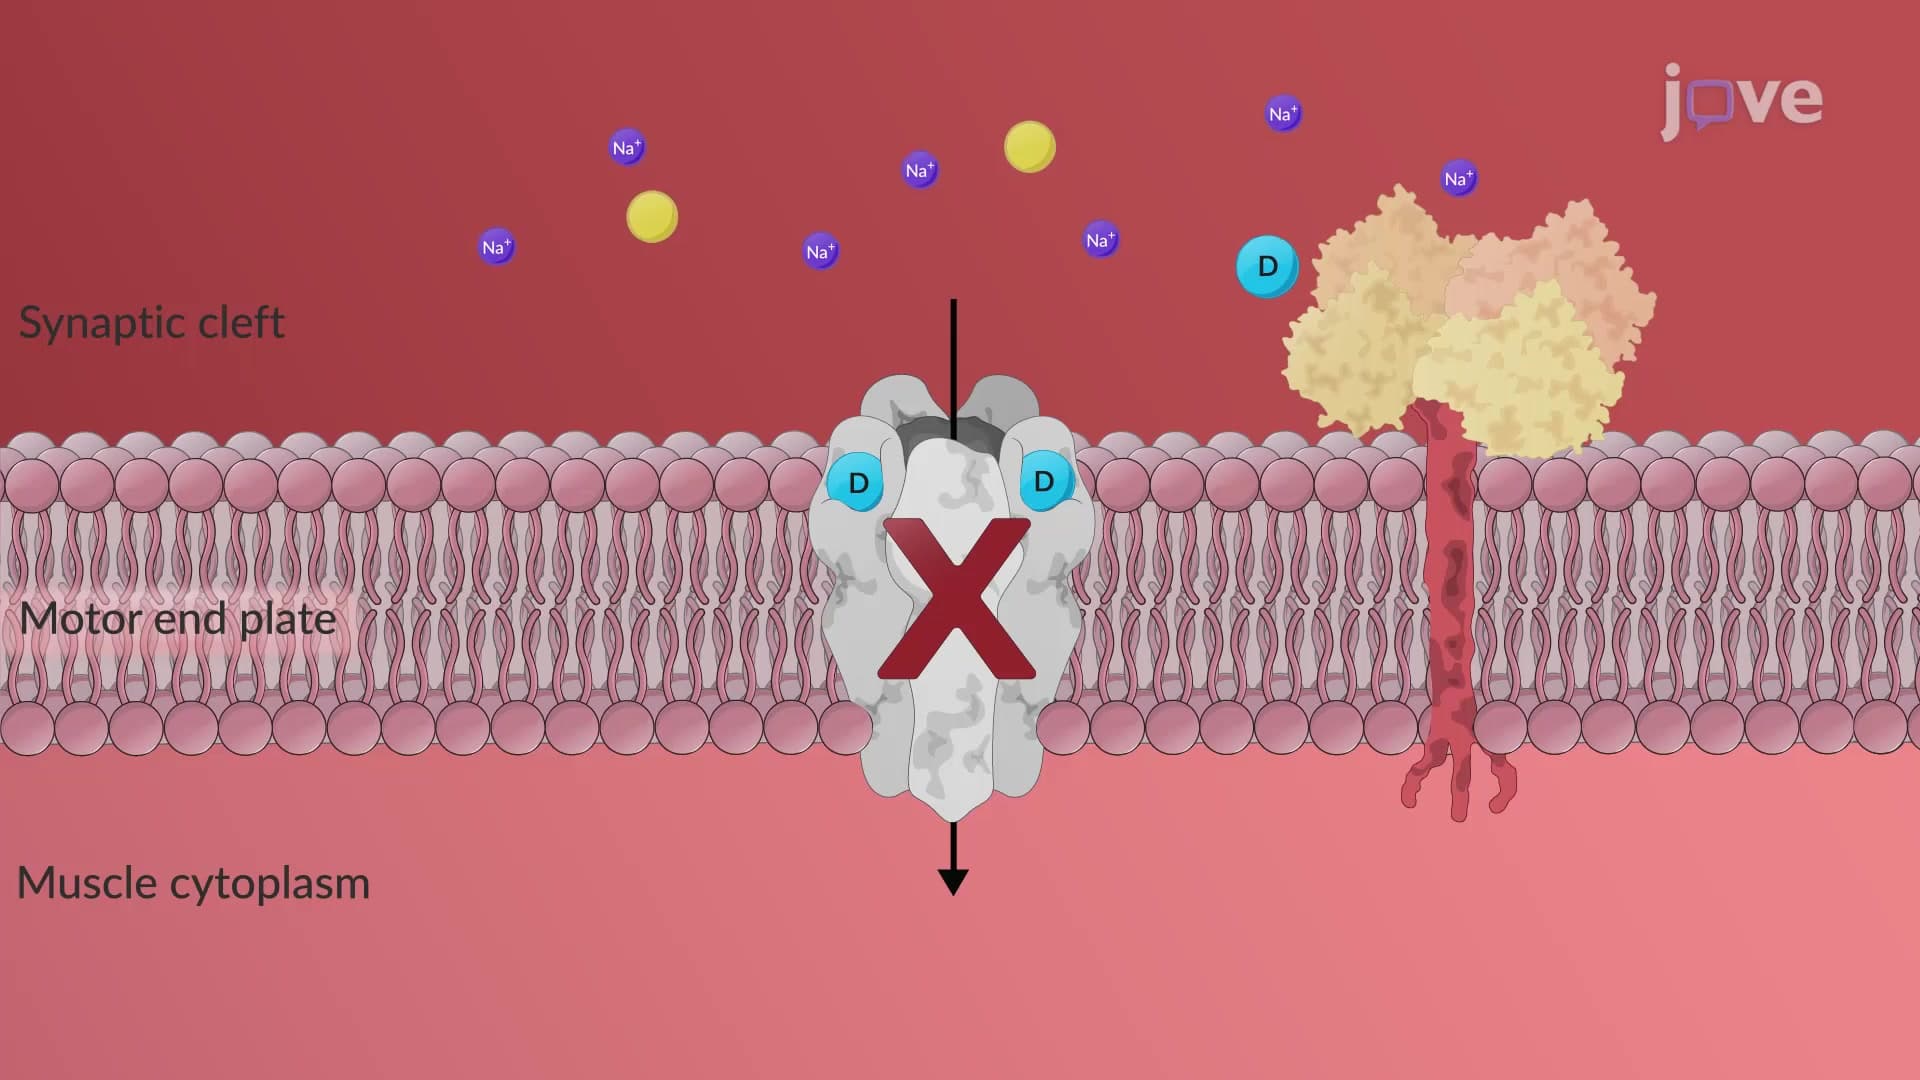
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:19
Depolarizing Blockers: Pharmocokinetics