The dynamics of gastritis
Related Experiment Video
Updated: Aug 19, 2026

The Dyspepsia Educational Tool As a Novel Aid in Dyspepsia Management
Published on: June 29, 2019
1Department of Gastroenterology and Hepatology, Academic Hospital Rotterdam, PO Box 2040, 3000 CA Rotterdam, The Netherlands. kuipers@mdl.azr.nl

Abstract:
The dynamics of gastritis remain a topic of intense investigation. The results of these investigations have increased our knowledge concerning the development of preneoplastic lesions and cancer of the stomach and given us insight with regard to the interactions among bacterial colonization, chronic inflammation, and carcinogenesis in other organs. The past year has presented us with further data showing that the progression of chronic gastritis to gland loss and gastric cancer is related to the severity of inflammation, which is influenced by the characteristics of the bacterial strain, host genetics, and hypochlorhydria. In contrast, Helicobacter pylori eradication leads to a rapid disappearance of neutrophils in the gastric mucosa. Chronic inflammation with mononuclear cells also improves upon eradication, but at a much slower rate, usually not leading to normalization within the first year after therapy. Whether H. pylori eradication can thus prevent new development of atrophy and metaplasia as well, or lead to regression of pre-existing lesions, has been the topic of many studies by now. Unfortunately, most of these studies have suffered from their case design, limited sample size, and short follow-up. Therefore, the conflict in outcome of these case studies comes as no surprise. The few prospective, randomized, controlled studies, however, strongly confirm that H. pylori eradication leads to healing of gastritis, which can at least halt further development of atrophy and metaplasia. Whether these lesions can truly regress remains to be proven.


Related Concept Videos
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
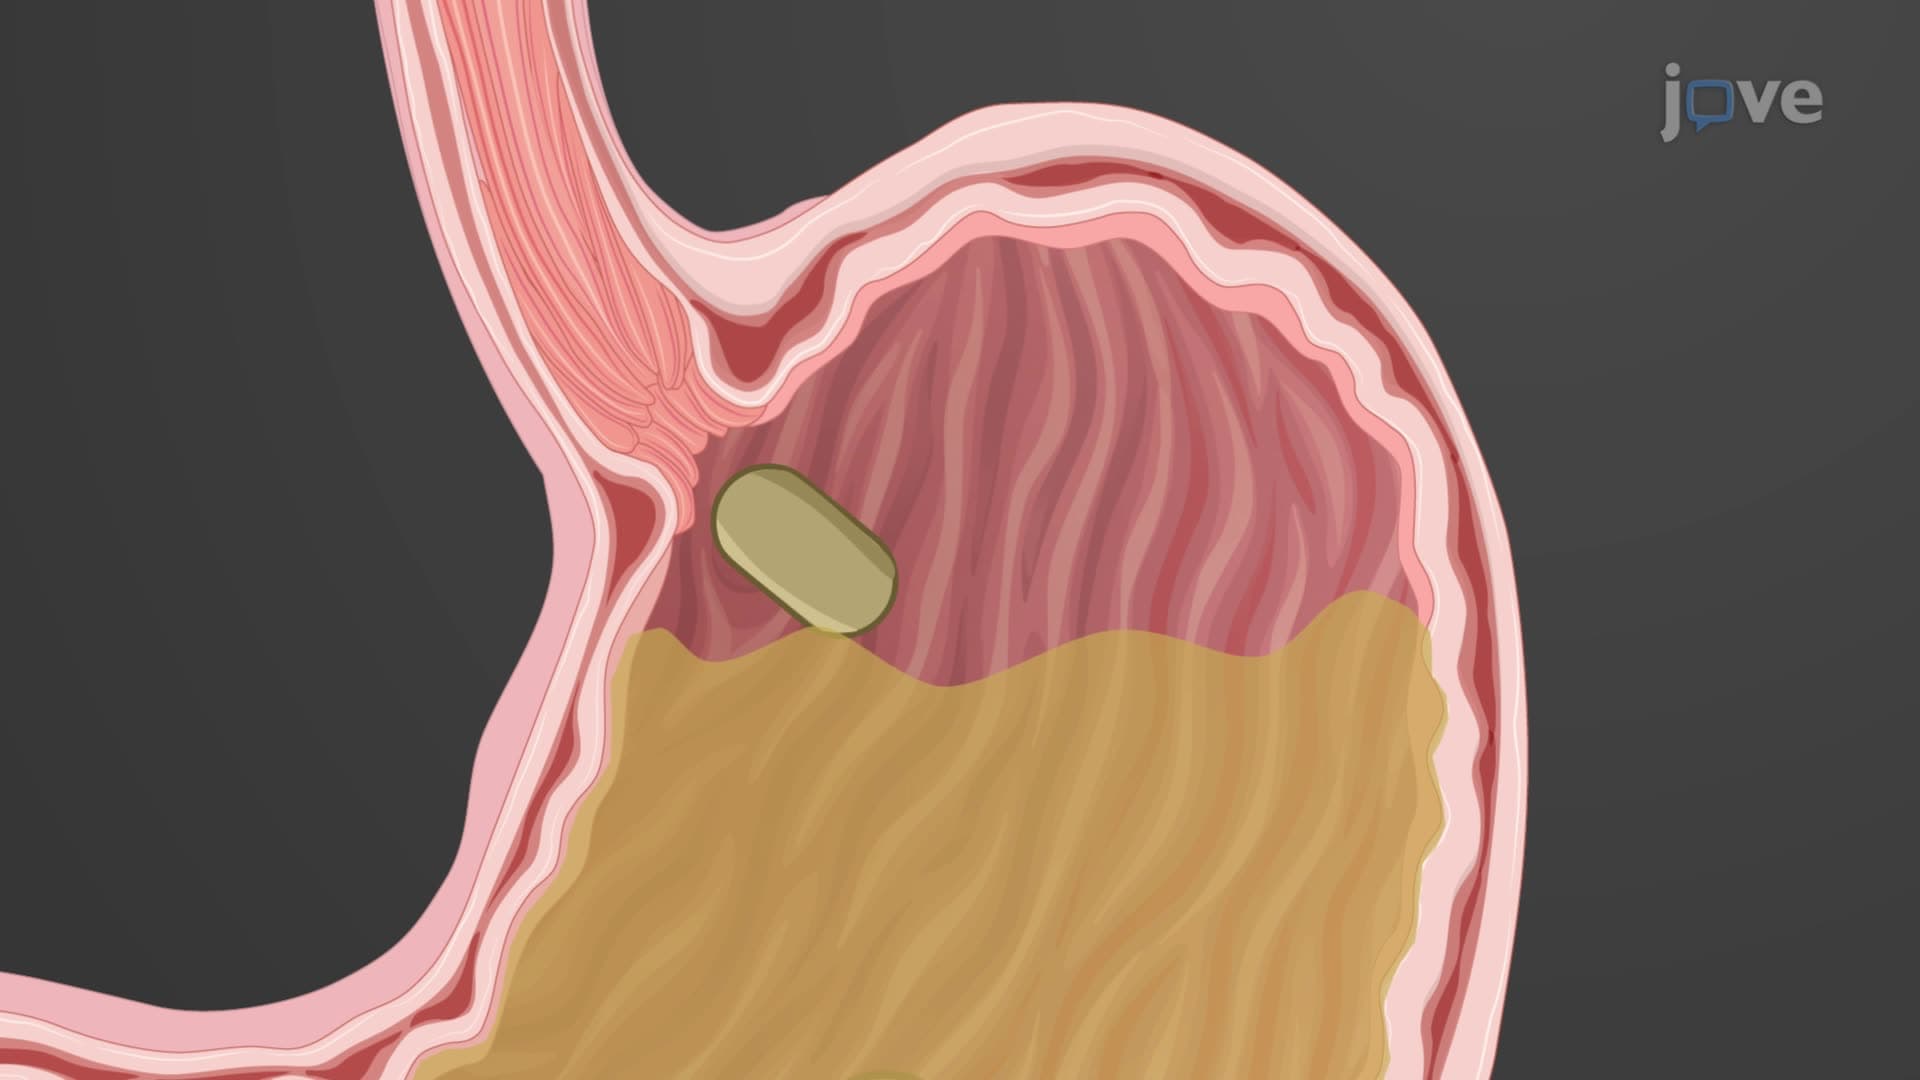 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:26
Gastritis II: Pathophysiology