Related Experiment Video
Updated: Aug 10, 2026
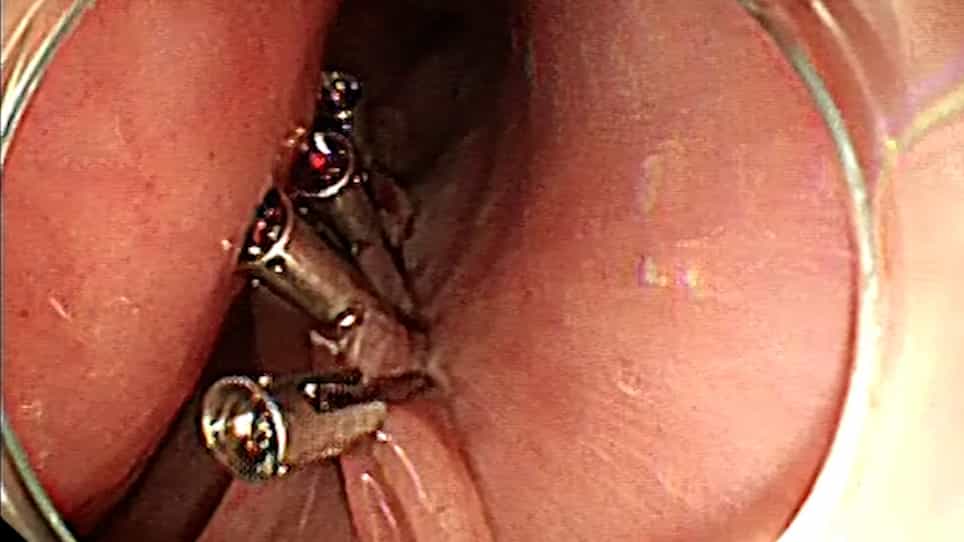

Use of the Scissor-Type Knife During the Peroral Endoscopy Myotomy Procedure for the Treatment of Achalasia
Published on: March 3, 2023
Laparoscopic and thoracoscopic esophagomyotomy for children with achalasia
M Mehra1, R J Bahar, M E Ament
1Department of Pediatrics, Division of Gastroenterology and Nutrition, University of California Los Angeles School of Medicine, Los Angeles, California 90095-1752, USA. mmehra@mednet.ucla.edu

Insights
Minimally invasive esophagomyotomy offers excellent symptom relief for pediatric achalasia patients. This surgical approach significantly reduces dysphagia and regurgitation, improving children's quality of life.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Minimally Invasive Procedures
Background:
- Minimally invasive esophagomyotomy (laparoscopic or thoracoscopic) is a preferred treatment for adult achalasia.
- This study evaluates the clinical outcomes of minimally invasive esophagomyotomy in pediatric achalasia patients.
Purpose of the Study:
- To assess the efficacy and safety of minimally invasive esophagomyotomy in children with achalasia.
- To evaluate postoperative outcomes including hospitalization duration, feeding resumption, and symptom relief.
Main Methods:
- A multicenter study involving 22 pediatric patients (1995-2000) diagnosed with achalasia.
- Patients underwent either transabdominal laparoscopic esophagomyotomy with fundoplication or thoracoscopic esophagomyotomy.
- Pre- and postoperative symptom severity scores for dysphagia and regurgitation were recorded.
Main Results:
- Transabdominal laparoscopic esophagomyotomy resulted in shorter hospital stays and faster resumption of feeding compared to converted open or thoracoscopic approaches.
- Significant improvements were observed in mean severity scores for dysphagia (2.6 to 0.4) and regurgitation (1.7 to 0.2) post-surgery.
- Two patients required conversion to open surgery due to intraoperative esophageal perforation.
Conclusions:
- Minimally invasive esophagomyotomy is an effective treatment for achalasia in children.
- The procedure provides substantial symptomatic relief from dysphagia and regurgitation, enhancing patient well-being.
Background:
Minimally invasive esophagomyotomy, consisting of a laparoscopic or thoracoscopic approach, has become a preferred surgical treatment for adults with achalasia. This multicenter study reports on the clinical status of children who have undergone minimally invasive esophagomyotomy for achalasia.
Methods:
Symptomatology for achalasia was assessed in 22 pediatric patients who underwent minimally invasive esophagomyotomy for achalasia between 1995 and 2000. All patients were evaluated for duration of hospitalization, postoperative resumption of feeds, postoperative complications, and symptomatic relief. Participants were assigned pre-and postoperative symptom severity scores ranging from 0 (no symptoms) to 3 (severe).
Results:
The median age of the 10 females and 12 males at time of surgery was 11.3 years +/- 3.4 (standard deviation). Transabdominal laparoscopic esophagomyotomy with fundoplication was performed in 18 patients, and thoracoscopic esophagomyotomy without fundoplication was performed in 4. Two patients required conversion from transabdominal laparoscopic esophagomyotomy to open esophagomyotomy because of intraoperative esophageal perforation. The mean duration of postsurgical follow-up was 17 +/- 16 (standard deviation) months (range, 1-54 months). Mean duration of hospitalization (days +/- standard error or mean) was less for transabdominal laparoscopic esophagomyotomy than for converted open esophagomyotomy (2.7 +/- 0.3 vs. 9.0 +/- 3.0 days; P < 0.05) or for thoracoscopic esophagomyotomy (4.8 +/- 1.7 days; P = not significant). Mean time to resumption of soft feedings (days +/- standard error or mean) occurred sooner after transabdominal laparoscopic esophagomyotomy than after converted open esophagomyotomy (2.0 +/- 0.2 vs. 5.5 +/- 0.5 days; P < 0.001) or after thoracoscopic esophagomyotomy (4.0 +/- 1.3 days; P = not significant). Patients experienced significant pre-to postoperative improvement in mean severity score with regard to dysphagia (2.6 vs. 0.4; P < 0.001) and regurgitation (1.7 vs. 0.2; P < 0.001).
Conclusions:
Minimally invasive esophagomyotomy can provide excellent symptomatic relief from dysphagia and regurgitation for children with achalasia.


