Related Experiment Video
Updated: Aug 16, 2026

Contractility Measurements on Isolated Papillary Muscles for the Investigation of Cardiac Inotropy in Mice
Published on: September 17, 2015
FK506 does not affect cardiac contractility and adrenergic response in vitro
H Milting1, P M Janssen, T Wangemann
1Martin-Luther-Universität Halle-Wittenberg, Clinic for Cardiothoracic Surgery, Research Laboratory, Ernst Grube Str. 40, D-06120, Halle an der Saale, Germany. hmilting@hdz-nrw.de

Insights
FK506 (tacrolimus) does not directly impact heart muscle contraction. This study found no positive or negative inotropic effects of FK506 on human and rabbit heart muscle preparations.
Area of Science:
- Cardiology
- Pharmacology
- Immunology
Background:
- FK506 (tacrolimus) is an immunosuppressant used in heart transplantation.
- The inotropic effects of FK506 on cardiac muscle are not well understood.
- FK506 binds to FKBP proteins, which are associated with cardiac calcium release channels.
Purpose of the Study:
- To investigate the direct inotropic effect of FK506 on isolated human and rabbit cardiac muscle preparations.
- To determine if FK506 alters myocardial contractility.
Main Methods:
- Experiments utilized isolated right atrial muscle strips from human myocardium and right ventricular trabeculae from rabbit hearts.
- Muscle preparations were electrically stimulated and exposed to varying concentrations of FK506.
- Dose-response curves were generated using isoprenaline as a beta-adrenoceptor agonist.
Main Results:
- FK506 exposure did not induce any positive or negative inotropic effects in human myocardium.
- FK506 exposure did not induce any positive or negative inotropic effects in rabbit myocardium.
Conclusions:
- FK506 does not exert a direct inotropic influence on cardiac muscle.
- The findings suggest FK506's role in cardiac transplantation is not mediated by direct effects on myocardial contractility.
Abstract:
FK506 (tacrolimus) is a new immunosuppressant being used in cardiac allograft transplantation. While cyclosporine A has been shown to exert an acute negative inotropic effect on isolated heart muscle preparations, little is known of the inotropic influence of FK506. The Ca(2+) release channel of human skeletal muscle and cardiac muscle is associated with FK506 binding proteins (FKBP), FKBP12 and FKBP12.6, respectively. FKBPs can be dissociated by treatment with FK506. As a consequence of FK506 exposure, isolated skeletal muscle and cardiac muscle ryanodine receptors show altered gating characteristics. Therefore, we analyzed the direct inotropic effect of FK506 exposure to isolated, intact heart muscle preparations from the human and rabbits. Experiments were performed on isolated, electrically stimulated right atrial auricular muscle strips obtained from human myocardium during elective open heart surgery and on intact right ventricular trabeculae from rabbit hearts. The human preparations were exposed to concentrations of 8 x 10(-9), 8 x 10(-8) and 8 x 10(-6) M FK506 followed by a cumulative dose-response curve with isoprenaline as a non-selective beta-adrenoceptor agonist. Our data suggest that FK506 does not exert any positive or negative inotropic effect in either human or rabbit myocardium.


Related Concept Videos
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:26
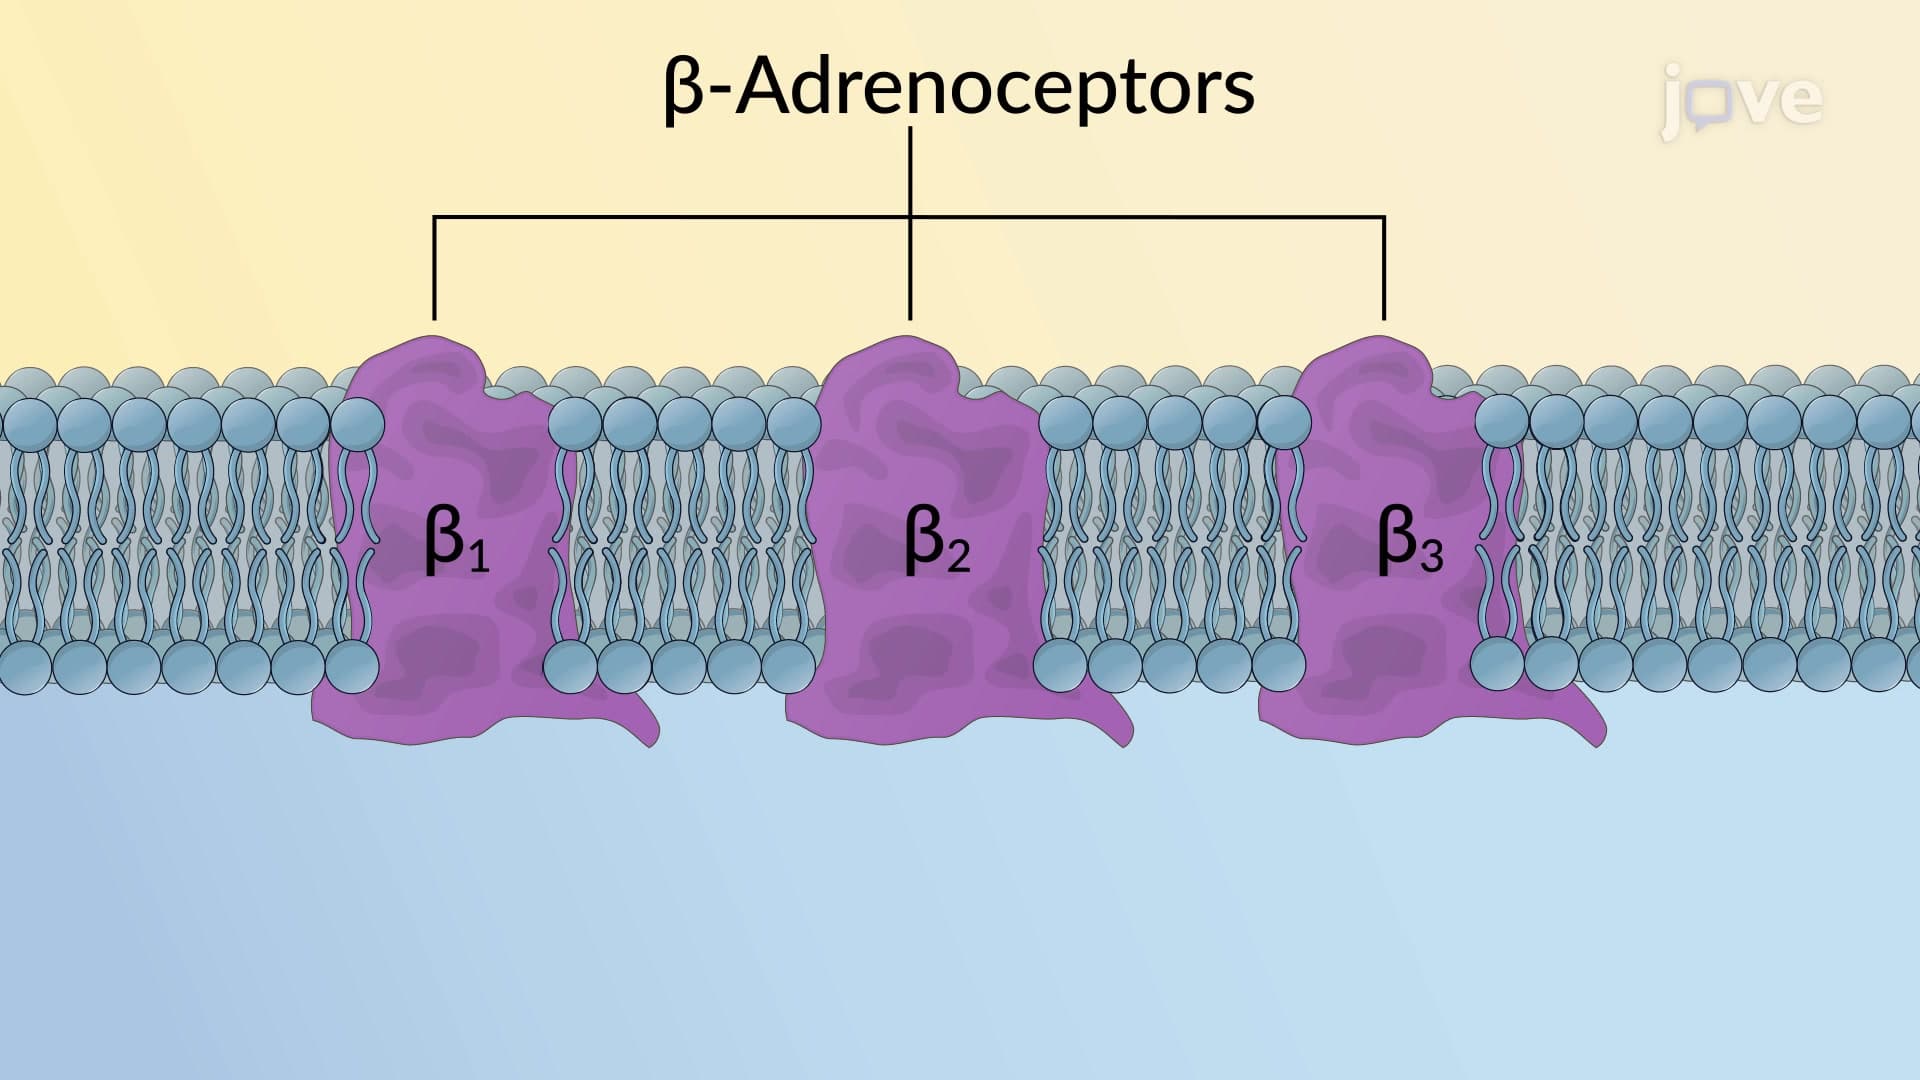
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:26
Heart Failure Drugs: Inotropic Agents
 01:22
Heart Failure Drugs: β-Blockers