Related Experiment Video
Updated: Jul 28, 2026
A Simple Protocol for Platelet-mediated Clumping of Plasmodium falciparum-infected Erythrocytes in a Resource Poor Setting
Published on: May 16, 2013
Factors contributing to anemia after uncomplicated falciparum malaria
R N Price1, J A Simpson, F Nosten
1Shoklo Malaria Research Unit, Mae Sod, Tak Province, Thailand. ricprice@doctors.org.uk

The factors contributing to anemia in falciparum malaria were characterized in 4,007 prospectively studied patients on the western border of Thailand. Of these, 727 patients (18%) presented with anemia (haematocrit < 30%), and 1% (55 of 5,253) required blood transfusion. The following were found to be independent risk factors for anemia at admission: age < 5 years, a palpable spleen, a palpable liver, recrudescent infections, being female, a prolonged history of illness (> 2 days) before admission, and pure Plasmodium falciparum infections rather than mixed P. falciparum and Plasmodium vivax infections. The mean maximum fractional fall in hematocrit after antimalarial treatment was 14.1% of the baseline value (95% confidence interval [CI], 13.6-14.6). This reduction was significantly greater in young children (aged < 5 years) and in patients with a prolonged illness, high parasitemia, or delayed parasite clearance. Loss of parasitized erythrocytes accounted for < 10% of overall red blood cell loss. Hematological recovery was usually complete within 6 weeks, but it was slower in patients who were anemic at admission (adjusted hazards ratio [AHR], 1.9, 95% CI, 1.5-2.3), and those whose infections recrudesced (AHR, 1.2, 95% CI, 1.01-1.5). Half the patients with treatment failure were anemic at 6 weeks compared with 19% of successfully treated patients (relative risk, 2.8, 95% CI, 2.0-3.8). Patients coinfected with P. vivax (16% of the total) were 1.8 (95% CI, 1.2-2.6) times less likely to become anemic and recovered 1.3 (95% CI, 1.0-1.5) times faster than those with P. falciparum only. Anemia is related to drug resistance and treatment failure in uncomplicated malaria. Children aged < 5 years of age were more likely than older children or adults to become anemic. Coinfection with P. vivax attenuates the anemia of falciparum malaria, presumably by modifying the severity of the infection.
The factors contributing to anemia in falciparum malaria were characterized in 4,007 prospectively studied patients on the western border of Thailand. Of these, 727 patients (18%) presented with anemia (haematocrit < 30%), and 1% (55 of 5,253) required blood transfusion. The following were found to be independent risk factors for anemia at admission: age < 5 years, a palpable spleen, a palpable liver, recrudescent infections, being female, a prolonged history of illness (> 2 days) before admission, and pure Plasmodium falciparum infections rather than mixed P. falciparum and Plasmodium vivax infections. The mean maximum fractional fall in hematocrit after antimalarial treatment was 14.1% of the baseline value (95% confidence interval [CI], 13.6-14.6). This reduction was significantly greater in young children (aged < 5 years) and in patients with a prolonged illness, high parasitemia, or delayed parasite clearance. Loss of parasitized erythrocytes accounted for < 10% of overall red blood cell loss. Hematological recovery was usually complete within 6 weeks, but it was slower in patients who were anemic at admission (adjusted hazards ratio [AHR], 1.9, 95% CI, 1.5-2.3), and those whose infections recrudesced (AHR, 1.2, 95% CI, 1.01-1.5). Half the patients with treatment failure were anemic at 6 weeks compared with 19% of successfully treated patients (relative risk, 2.8, 95% CI, 2.0-3.8). Patients coinfected with P. vivax (16% of the total) were 1.8 (95% CI, 1.2-2.6) times less likely to become anemic and recovered 1.3 (95% CI, 1.0-1.5) times faster than those with P. falciparum only. Anemia is related to drug resistance and treatment failure in uncomplicated malaria. Children aged < 5 years of age were more likely than older children or adults to become anemic. Coinfection with P. vivax attenuates the anemia of falciparum malaria, presumably by modifying the severity of the infection.
More Related Videos
 10:22
Methods to Investigate the Regulatory Role of Small RNAs and Ribosomal Occupancy of Plasmodium falciparum
Published on: December 4, 2015
 09:57
Measuring Naturally Acquired Phagocytosis-Inducing Antibodies to Plasmodium falciparum Parasites by a Flow Cytometry-Based Assay
Published on: August 6, 2020
Related Concept Videos
 01:24
Factors Affecting Respiration
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:24
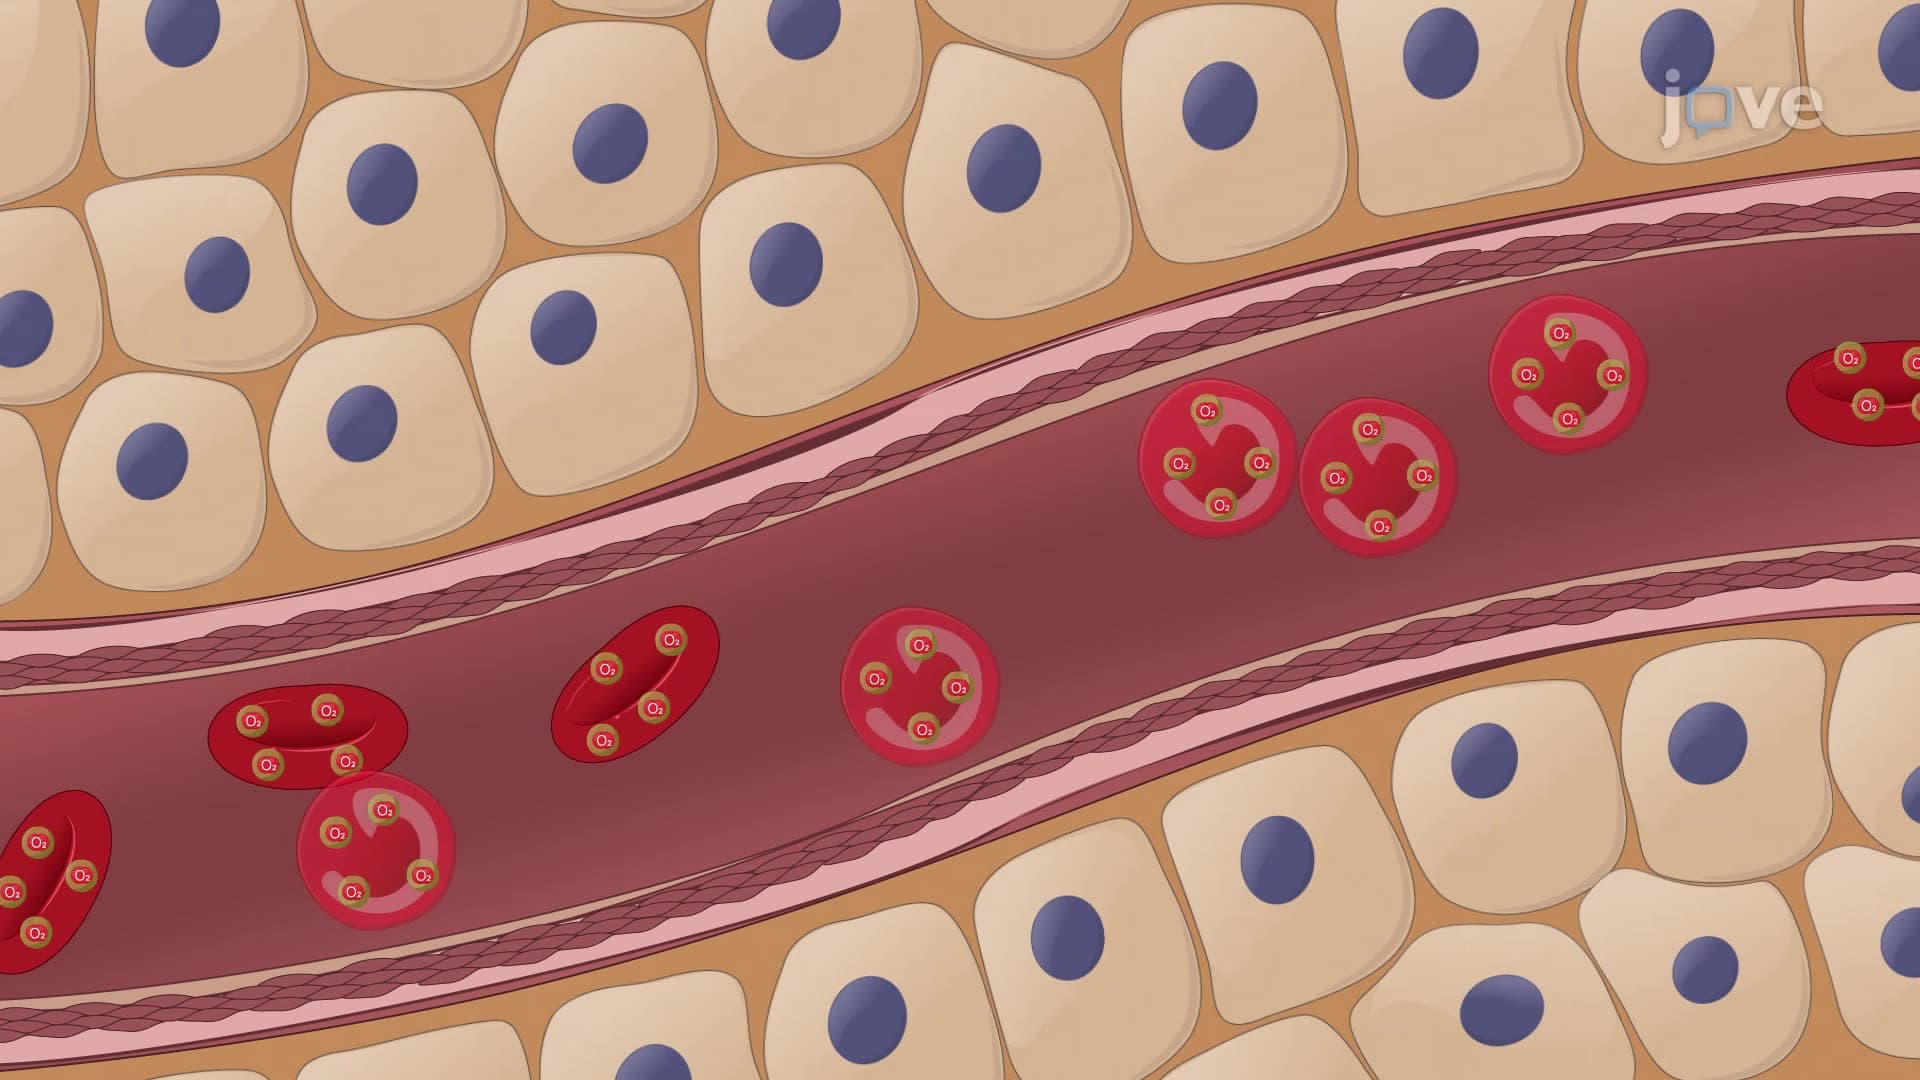
Factors Affecting Erythropoiesis
Several factors influence the erythrocyte production rate, with tissue oxygen level being among the most critical. Intense exercise or high altitudes can cause tissue hypoxia, which triggers the kidneys to release more erythropoietin (EPO) into the bloodstream.
EPO then...
 01:29
Malaria
 01:28
Amebiasis