Related Experiment Video
Updated: Oct 3, 2026
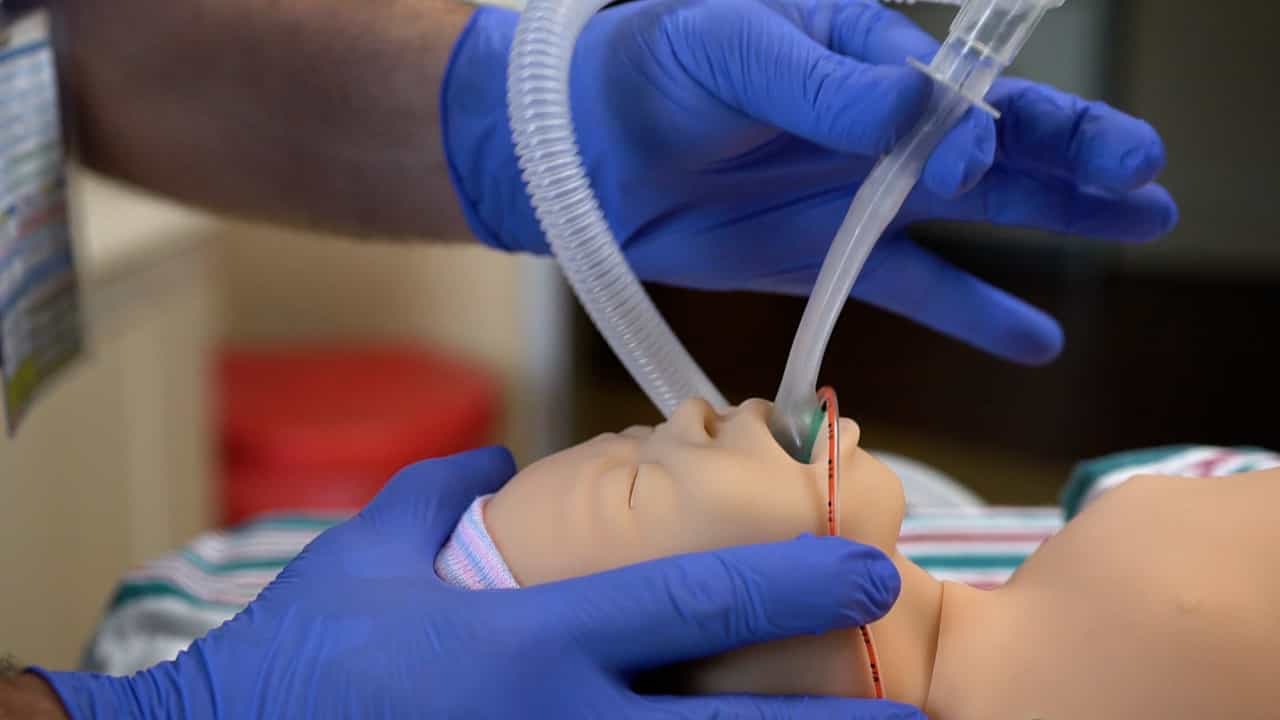

Laryngeal Mask Airway (LMA) Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway (SGA)
Published on: July 14, 2023
Comparison of methods of bag and mask ventilation for neonatal resuscitation
1Division of Neonatology, Department of Pediatrics, San Diego Medical Center, University of California, 200 West Arbor Drive, 8774, San Diego, CA 92103-8774, USA. nfiner@ucsd.edu

Background:
There are a variety of manual bagging devices used for neonatal resuscitation. To our knowledge, there has been no comparison of the ability of different operators to utilize such devices for the delivery of predetermined inspiratory and end-expiratory pressures. In addition, the use of prolonged inflation may be of benefit for infants who require bag and mask ventilation, and there has been no evaluation of the ability of a variety of operators to reliably deliver such breaths using currently available equipment.
Methods:
We utilized a neonatal manikin (Laerdal Armonk, NY) with a functional larynx and lungs, and a clear cushioned mask (Owens-BriGam, Morganton, NC). We studied a latex-free disposable anesthesia type bag (Model 5126 Vital Signs, Totawa, NJ), a Jackson-Rees (JR) type anesthesia bag (Model E191 Anesthesia Associates, San Marcos, CA) fitted with a Norman elbow and a flow-control tail-piece (Dupaco, Oceanside, CA), and the Neopuff (Fisher and Paykel, Auckland, New Zealand), an FDA approved mechanical device that is flow-controlled and pressure-limited, specifically designed to facilitate neonatal resuscitation. The ventilating pressures were continuously recorded throughout the process. We evaluated neonatal nurses, neonatal nurse practitioners, neonatal staff and fellows, pediatric residents and neonatal respiratory therapists.
Results:
The peak inspiratory pressure (PIP) was significantly different between operators using either anesthesia bag, P<0.001. Similar results were found for positive end-expiratory pressure (PEEP) with a significant difference among the operator groups, P<0.001. All the differences in post hoc analysis were between the therapists and the other groups, P<0.05. Therapists produced significantly higher pressures than the other groups for both PIP and PEEP (P<0.001). The PIP was similar for all groups using the Neopuff device. The PIP and PEEP delivered by the Neopuff differed from the other two devices independent of the operators (P<0.05). On post hoc analysis, there was a significant difference between the disposable anesthesia bag and Neopuff for both PIP and PEEP for the therapists, whereas among the non-therapists, there was a difference in PIP with the JR device producing a greater PIP (26.6+/-3.8 cmH(2)O) compared with the Neopuff and disposable anesthesia bag (24.8+/-1.1 cmH(2)O, 24.8+/-4.3 cmH(2)O). The level of PEEP was significantly different among all three devices for the non-therapists (1.3+/-1.6 cmH(2)O, Disposable; 2.9+/-1.2 cmH(2)O, JR; 4.7+/-0.5 cmH(2)O, Neopuff; P<0.05). Only the therapists were able to consistently deliver PEEP with the anesthesia bags, whereas all operators could generate the target PEEP with the Neopuff (P<0.05). We compared the pressure delivered during the first second to the pressure delivered during the fifth second during prolonged 5-s inflations. The absolute differences between the first and fifth second for the Neopuff versus the anesthesia bags were significantly different with a median of 7.1 cmH(2)O for the anesthesia bags compared with 0.2 cmH(2)O for the Neopuff, P<0.001, reflecting the difficulty in obtaining and maintaining the target inflation pressures.
Conclusions:
Our experience suggests that the Neopuff, a purpose-built neonatal resuscitator ventilator, facilitates the delivery of the desired airway pressures while maximizing the operators ability to obtain and maintain a patent airway, and facilitates the delivery of prolonged inflations. Further research is required to determine the clinical benefit of end-expiratory pressure and prolonged inflations in neonatal resuscitation.

Related Concept Videos
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:26
Oxygen Delivering System I: Nasal Cannula and Face Mask
Nasal Cannula
A nasal cannula is a lightweight tube split at one end into two prongs and placed in the nostrils. It is typically used to deliver low to medium levels of oxygen.
Suggested flow rate: The suggested flow rate for a nasal cannula typically ranges between 1 and 6 L/min.
Oxygen percentage setting:...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:30
Administering Oxygen by Mask
Administering oxygen by mask is a common nursing intervention that provides supplemental oxygen to patients with respiratory distress or chronic lung conditions. This procedure involves delivering oxygen at a specified rate through a face mask connected to an oxygen source.
Equipment
The equipment necessary for this procedure includes: