Related Experiment Video
Updated: Oct 3, 2026
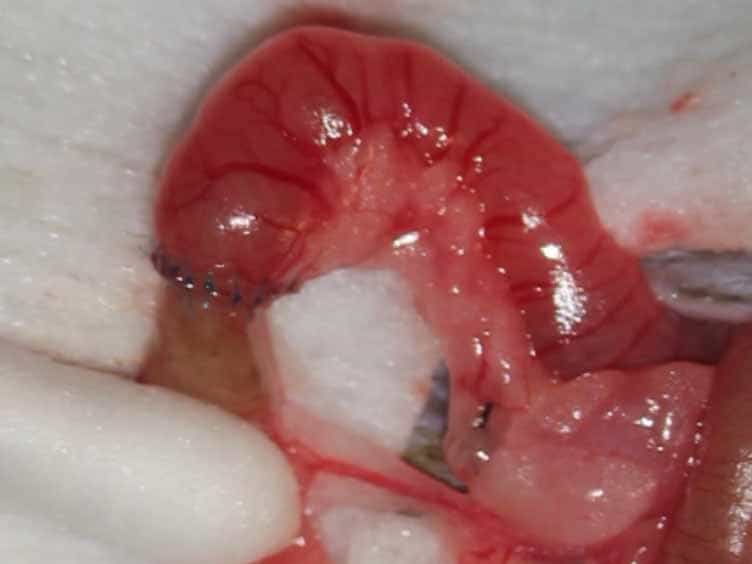
Murine Ileocolic Bowel Resection with Primary Anastomosis
Published on: October 29, 2014
Colonic atresia: surgical management and outcome
I Karnak1, A O Ciftci, M E Senocak
1Department of Pediatric Surgery, Hacettepe University Medical Faculty, Ankara, Turkey.

Insights
Colonic atresia (CA) management requires prompt intestinal decompression via ostomy. Primary anastomosis without prior colostomy and associated anomalies significantly increase the risk of poor outcomes in infants with CA.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Neonatal Medicine
Background:
- Colonic atresia (CA) is an exceedingly rare congenital anomaly causing intestinal obstruction in neonates.
- Limited data exists regarding optimal management strategies and prognostic indicators for CA.
- This study aims to analyze clinical characteristics, surgical interventions, and outcomes in CA patients.
Purpose of the Study:
- To delineate the clinical features of colonic atresia (CA).
- To evaluate surgical management approaches for CA.
- To identify factors influencing patient outcomes in CA.
Main Methods:
- Retrospective review of pediatric patients diagnosed with CA between 1977 and 1998.
- Analysis of patient demographics, clinical presentation, diagnostic imaging (X-ray, barium enema), atresia types, associated anomalies, surgical procedures, and outcomes.
- Statistical evaluation of factors affecting mortality and morbidity.
Main Results:
- 18 patients (14 boys, 4 girls) aged 1 day to 5 months presented with intestinal obstruction.
- Common atresia types included IIIa (n=9), I (n=6), and II (n=3). Type I was more frequent than previously reported.
- Initial management was enterostomy (83%) or primary anastomosis (17%). Overall mortality was 61%, significantly higher with primary anastomosis and major associated anomalies (e.g., multiple small-intestinal atresias, gastroschisis).
Conclusions:
- Prompt intestinal decompression via ostomy is crucial for initial CA management.
- Surgical approach (primary anastomosis vs. staged repair) and presence of associated anomalies are key determinants of outcome.
- Type I colonic atresia may be associated with proximal multiple atresias, warranting thorough investigation.
Abstract:
Colonic atresia (CA) is a very rare cause of intestinal obstruction, and little information has been available about the management and predictors of outcome. A retrospective clinical trial was performed to delineate the clinical characteristics of CA with special emphasis on surgical treatment and factors affecting outcome. Children with CA who were treated in our department between 1977 and 1998 were reviewed: 14 boys and 4 girls aged 1 day to 5 months. All but 2 referred patients and 1 with prenatal diagnosis presented with intestinal obstruction. Plain abdominal X-ray films showed findings of intestinal obstruction in 14 cases; a barium enema demonstrated a distal atretic segment and microcolon in 4. The types of atresia were IIIa (n=9), I (n=6), and II (n=3). Type IIIa atresias were located proximal to the splenic flexure (n=8) and in the sigmoid colon (n=1), type I atresias were encountered throughout the colon; and all type II atresias were proximal to the hepatic flexure. Associated anomalies were multiple small-intestinal atresias (MSIA) (n=4), gastroschisis (GS) (n=2), pyloric atresia (n=1), Hirschsprung's disease (n=1), and complex urologic abnormalities (n=1). The initial management was an enterostomy in 15 patients (83%), including 2 referred and 2 with GS, and primary anastomosis in the remaining 3 (17%). Secondary procedures were the Santulli operation (n=2), colostomy closure and recolostomy followed by a Swenson operation (n=1), sacroabdominoperineal pull-through (n=1), and colostomy closure (n=1). Leakage was encountered in all primarily anastomosed patients. The overall mortality was 61%. Deaths occurred in patients with associated major anomalies (GS 2, MSIA 3, pyloric atresia 1) (55%) and in 3 patients who were initially managed by primary anastomosis (27%). Two additional patients died of sudden infant death syndrome (18%). Type I atresia was more common than in previously reported series and was associated with proximal multiple atresias. The initial management of CA should be prompt decompression of the intestine by an ostomy procedure, preferably end- or double-barrel. The type of surgery (primary anastomosis without prior colostomy) and associated abnormalities are the major determinants of poor outcome.
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...