Hemodynamic responses to intrapleural insufflation with hemipulmonary collapse
Related Experiment Video
Updated: Oct 3, 2026
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome (ARDS)
Published on: April 7, 2021
T Ohtsuka1, J Nakajima, Y Kotsuka
1Department of Cardiothoracic Surgery, University of Tokyo, 7-3-1 Hongo, Bunkyo-ku, Tokyo 113-8655, Japan. OHTSUKA-THO@h.u-tokyo.ac.jp

Background:
The hemodynamic effects of carbon dioxide (CO2) insufflation with hemipulmonary collapse were studied in consecutive thoracoscopic harvests of the left or right internal mammary artery (IMA), which were used for video-assisted coronary artery bypass grafting.
Methods:
Thirty-eight patients (30 male, eight female) with a mean age of 69.5 +/- 11.5 years were selected, and 33 left and five right IMA were harvested thoracoscopically. After hemipulmonary collapse was established by single-lung ventilation, low-flow (2-3 L/min) CO2 was delivered at a constant intrapleural pressure of 8-10 mmHg. Using electrocardiography, a radial arterial catheter, a Swan-Ganz catheter, and transesophageal echocardiography, we obtained values for seven hemodynamic variables. Baseline data were collected during bilateral lung ventilation. Each variable was then measured during hemipulmonary collapse and insufflation. The significance of any changes was established with Student's t-test after correcting for baseline differences.
Results:
Insufflation facilitated IMA harvest by expanding the pleural space between the anterior chest wall and heart. Mean insufflation times were 40.8 +/- 12.2 min on the left and 33.5 +/- 8.5 min on the right. Significant increases from the baseline values were observed in the mean central venous pressure (L:4.7-9.0 mmHg, R: 5.1-14.0 mmHg, p < 0.05), the pulmonary arterial pressure (L: 11.3-17.3 mmHg, R: 12.1-19.9 mmHg, p < 0.05), and the pulmonary capillary wedge pressure (L: 7.2-10.5 mmHg, R: 6.5-10.0 mmHg, p < 0.05). On the right, but not on the left, slight decreases were noted in the mean arterial pressure and cardiac index (71.3-62.6 mmHg, 2.01-1.76 L min-1 m-2, p < 0.05).
Conclusions:
The hemodynamic effect resulting from one-lung collapse plus low-flow CO2 insufflation at 8-10 mmHg for 30-40 min is mild in both hemithoraces, although the impact is greater on the right.
Related Concept Videos
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:08
Pneumothorax II: Pathophysiology
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
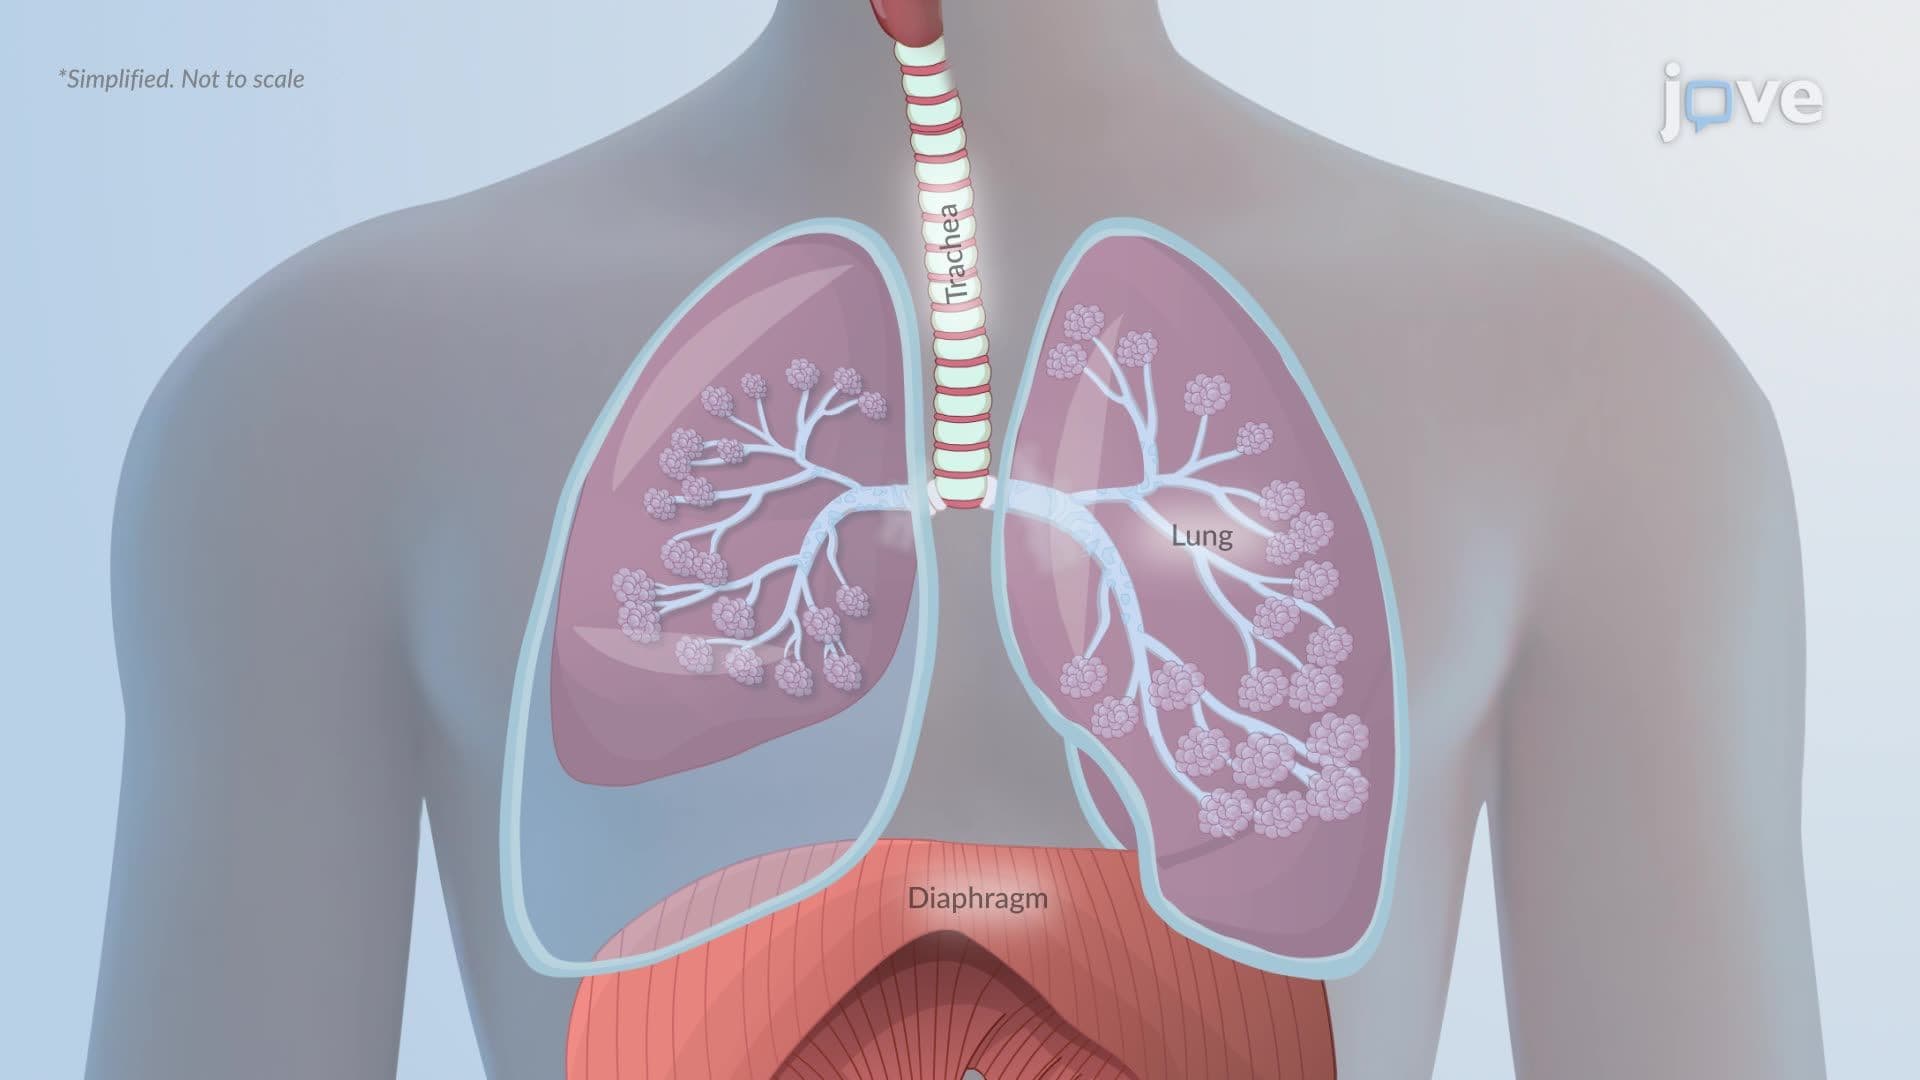
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:10
Atelectasis II: Pathophysiology
 01:29
Pulmonary Embolism I: Introduction
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: