Related Experiment Video
Updated: Aug 17, 2026

An Optimized Hemagglutination Inhibition (HI) Assay to Quantify Influenza-specific Antibody Titers
Published on: December 1, 2017
Antibody response to 17D yellow fever vaccine in Ghanaian infants
M Osei-Kwasi1, S K Dunyo, K A Koram
1Virology Unit, Noguchi Memorial Institute for Medical Research (NNIMR), University of Ghana, Legon.

Insights
Yellow fever vaccination in infants at 6 or 9 months shows similar, high seroconversion rates and no significant adverse effects. This suggests the 17D vaccine is safe and effective for early infant immunization in high-risk areas.
Area of Science:
- * Pediatric Infectious Diseases
- * Vaccinology
- * Immunology
Background:
- * Yellow fever remains a significant public health concern, particularly in endemic regions.
- * Current vaccination schedules often recommend yellow fever vaccine administration later in infancy.
- * Understanding early seroresponses and safety is crucial for optimizing infant immunization strategies.
Purpose of the Study:
- * To evaluate seroresponses to the 17D yellow fever vaccine in infants immunized at 6 versus 9 months of age.
- * To assess the safety and adverse effects of the 17D yellow fever vaccine in infants, with a focus on 6-month-old infants.
- * To determine the feasibility of earlier infant yellow fever vaccination.
Main Methods:
- * A randomized controlled trial involving 420 infants who had completed primary immunizations (BCG, OPV, DPT).
- * Infants were randomized to receive the 17D yellow fever vaccine at either 6 or 9 months of age.
- * Serum samples were collected pre-immunization and 3 months post-immunization for antibody titration against the vaccine virus.
Main Results:
- * Both 6-month and 9-month immunization groups demonstrated high seroconversion rates (98.6% and 98%, respectively).
- * Geometric Mean Titers (GMTs) of yellow fever antibodies were comparable between the two groups (158.5 at 6 months vs. 129.8 at 9 months).
- * Common adverse reactions included fever, cough, diarrhea, and local site reactions, with no statistically significant differences between the age groups.
Conclusions:
- * The 17D yellow fever vaccine elicits similar and robust seroresponses when administered at 6 or 9 months of age.
- * Immunization at 6 months of age showed good seroresponse with no significant adverse effects, supporting its potential use.
- * The 17D yellow fever vaccine can be recommended for infants at 6 months in outbreak situations or endemic areas with high risk.
Objectives:
To assess the seroresponses to yellow fever vaccination at 6 and 9 months of age; assess any possible adverse effects of immunization with the 17D yellow fever vaccine in infants, particularly at 6 months of age.
Methods:
Four hundred and twenty infants who had completed BCG, OPV and DPT immunizations were randomized to receive yellow fever immunization at either 6 or 9 months. A single dose of 0.5 ml of the reconstituted vaccine was administered to each infant by subcutaneous injection. To determine the yellow fever antibody levels of the infants, each donated 1 ml whole blood prior to immunization and 3 months post-immunization. Each serum sample was titred on Vero cells against the vaccine virus.
Findings:
The most common adverse reactions reported were fever, cough, diarrhoea and mild reactions at the inoculation site. The incidences of adverse reactions were not statistically different in both groups. None of the pre-immunization sera in both age groups had detectable yellow fever antibodies. Infants immunized at 6 months recorded seroconversion of 98.6% and those immunized at 9 months recorded 98% seroconversion. The GMT of their antibodies were 158.5 and 129.8, respectively.
Conclusions:
The results indicate that seroresponses to yellow fever immunization at 6 and 9 months as determined by seroconversion and GMTs of antibodies are similar. The findings of good seroresponses at 6 months without significant adverse effects would suggest that the 17D yellow fever vaccine could be recommended for use in children at 6 months in outbreak situations or in high risk endemic areas.
More Related Videos


Related Concept Videos
 00:42
Cross-reactivity
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
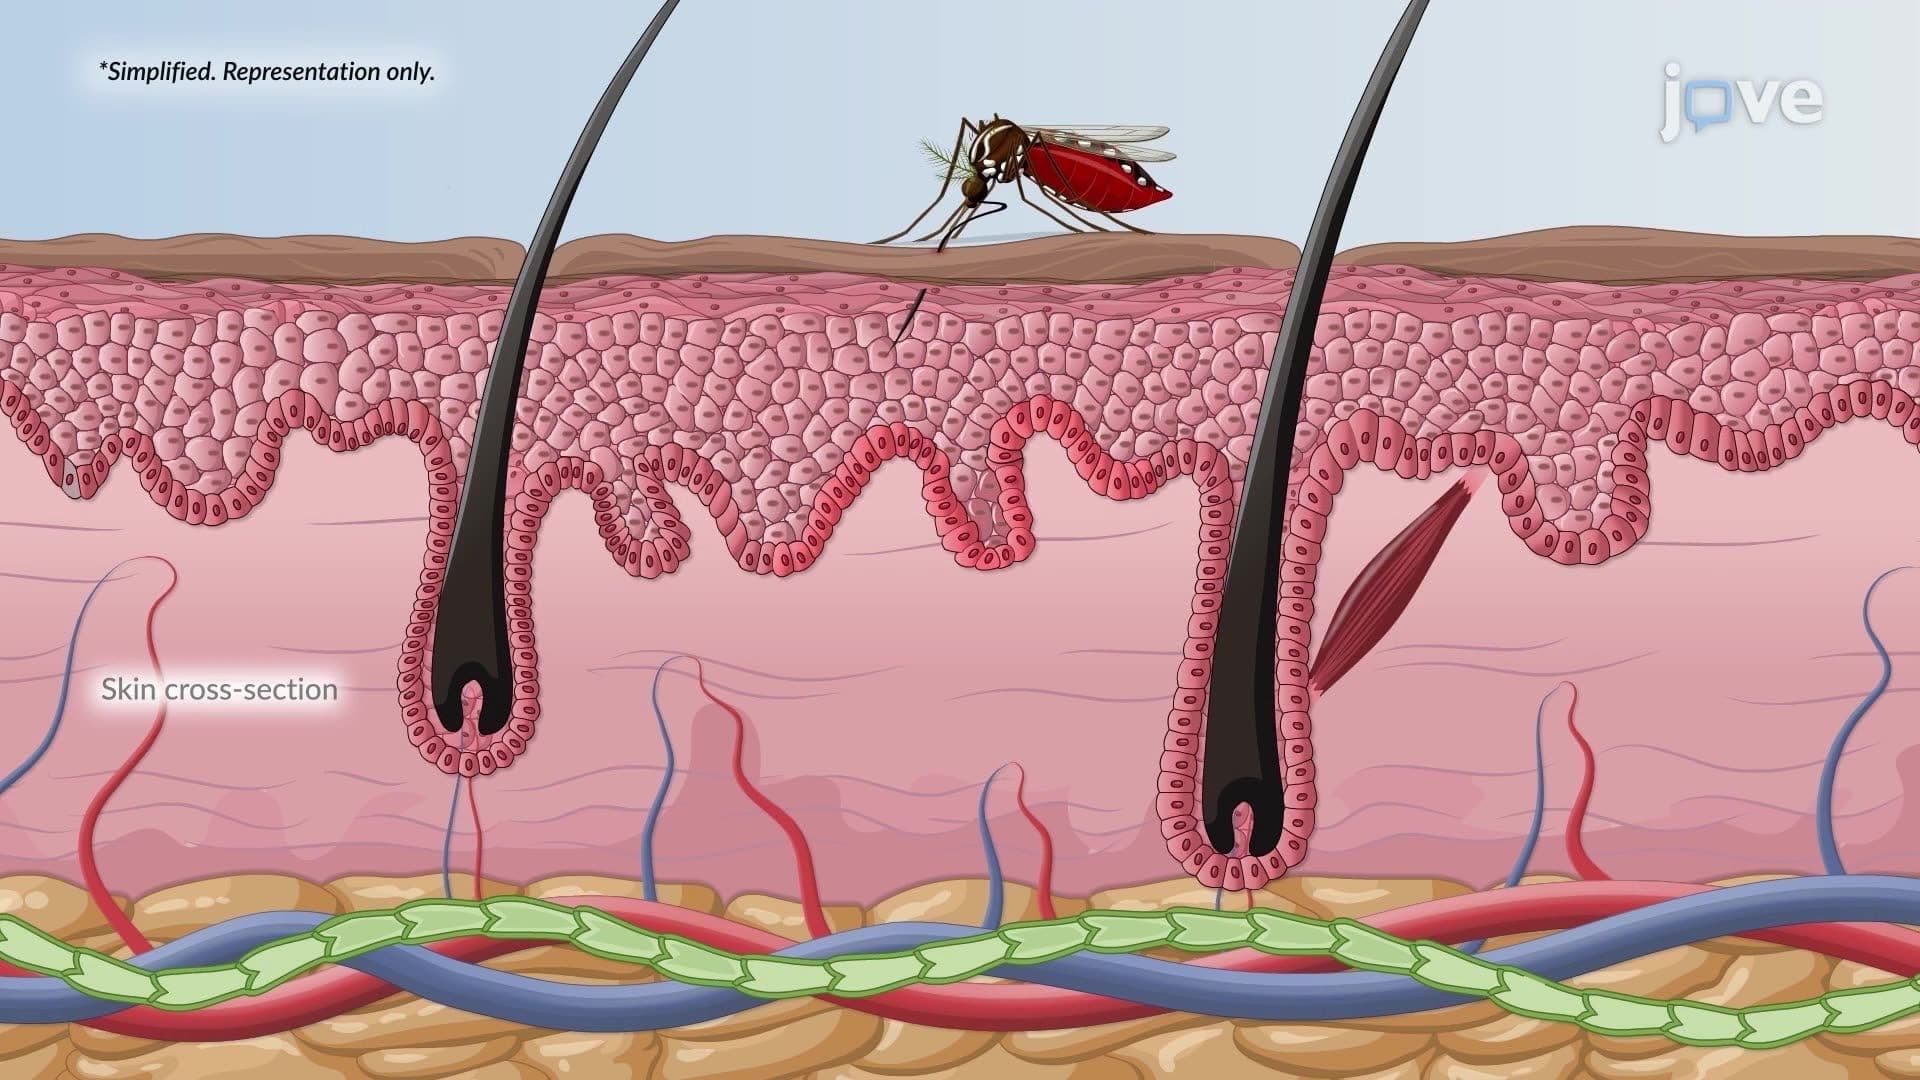 01:18
Yellow Fever