Related Experiment Video
Updated: Jul 28, 2026
Physiology Lab Demonstration: Glomerular Filtration Rate in a Rat
Published on: July 26, 2015
Peak rates of diuresis in healthy humans during oral fluid overload
T D Noakes1, G Wilson, D A Gray
1University of Cape Town Research Unit for Exercise Science and Sports Medicine, University of Cape Town Medical School and Sports Science Institute of South Africa, Cape Town.

Objective:
To determine whether rates of intestinal fluid absorption and renal diuresis can match high rates of fluid ingestion in healthy humans exposed to oral fluid overload, thereby preventing the development of hyponatraemia either by reverse sodium movement across the intestine (the Priestley-Haldane effect) or by expansion of the extracellular fluid volume.
Methods:
Changes in renal function and in plasma chemical measurements in response to an oral fluid overload (0.9-1.8 l/h x 3 h) were investigated in 6 healthy control subjects at rest, and in a subject with a history of exercise-induced symptomatic hyponatraemia, during both prolonged (160-minute) exercise and at rest.
Findings:
All control subjects gained weight (2.7 +/- 0.2 kg, mean +/- standard error of mean (SEM)) because the rate of oral fluid intake exceeded the peak rate of urine production (778 +/- 39 ml/h). Blood volume rose by 7.1 (+/- 0.5)% and plasma sodium concentrations fell progressively from 144 +/- 2.6 to 136 +/- 1.1 mmol/l (P < 0.05) in the control subjects. Plasma potassium and angiotensin II concentrations were unchanged and creatinine clearance was normal (approximately 125 ml/min). Free water clearance reached a maximum of 11.2 +/- 0.9 ml/min after 2 hours. The increase in body mass could be accounted for by calculated or measured changes in extra- and intracellular fluid volumes. Similar changes were measured in the subject with a previous history of symptomatic hyponatraemia.
Conclusion:
The rate of intestinal fluid absorption appeared to match the rate of oral fluid ingestion and there was no evidence of fluid accumulation in the intestine with reverse sodium movement from the extracellular space into intestinal fluid. The results of this study are therefore at variance with the Priestley-Haldane hypothesis and suggest that reverse sodium movement did not contribute to the hyponatraemia induced by oral fluid overload in these subjects. Rather it appears that humans may have a limited capacity to excrete fluid at rates in excess of approximately 900 ml/h in response to higher rates of oral fluid intake. When the rate of intestinal fluid absorption matches the rate of fluid ingestion and exceeds the kidneys' maximum capacity for fluid excretion, the excess fluid accumulates in the extra- and intracellular fluid compartments, inducing the dilutional hyponatraemia of water intoxication. These findings may have relevance to other clinical conditions in which hyponatraemia develops in response to high rates of oral or intravenous fluid provision.
Related Concept Videos
 01:20
Formation of Dilute Urine
Filtrate Osmolarity in the PCT
Initially, as the filtrate passes through the proximal convoluted tubule (PCT), its...
 01:24
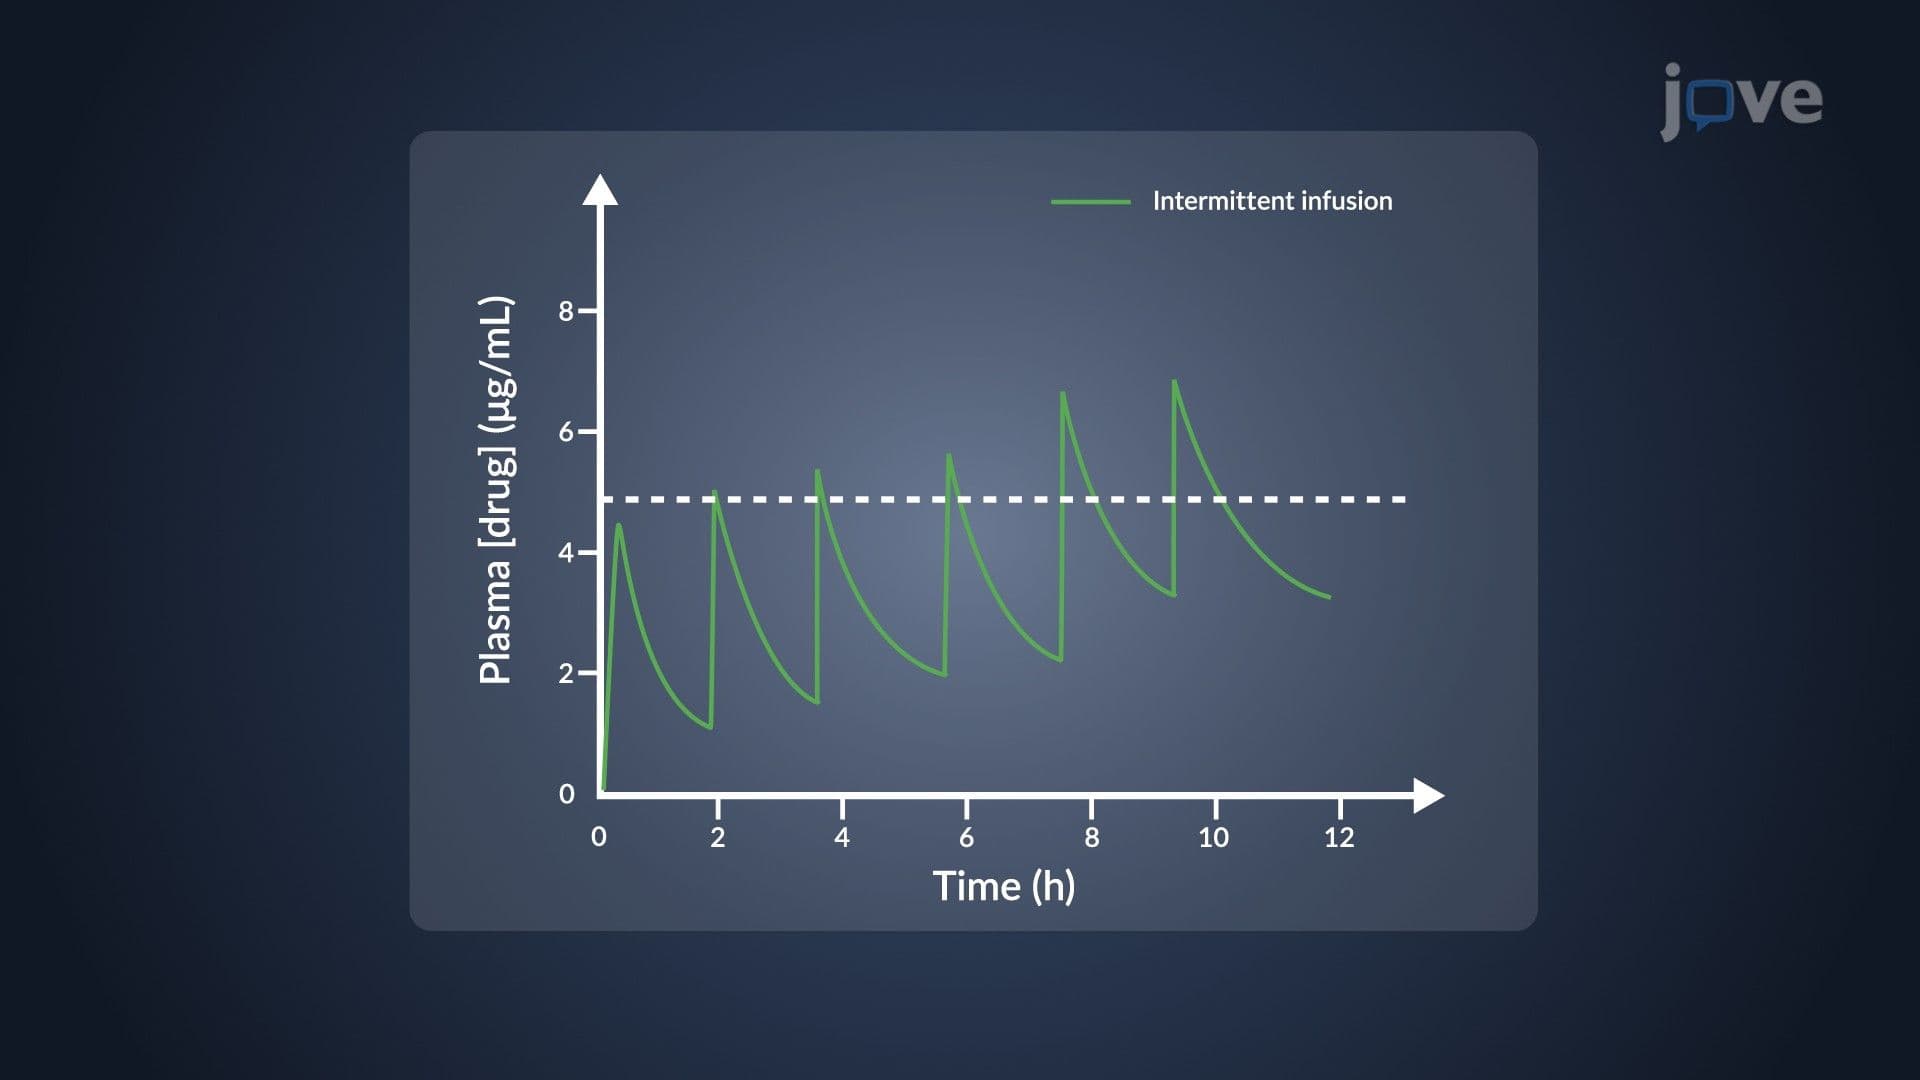
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:20
Physiology of the Genitourinary System III: Urine Concentration and Dilution
 01:30
Peritoneal Dialysis I: Introduction and Procedure
 01:19
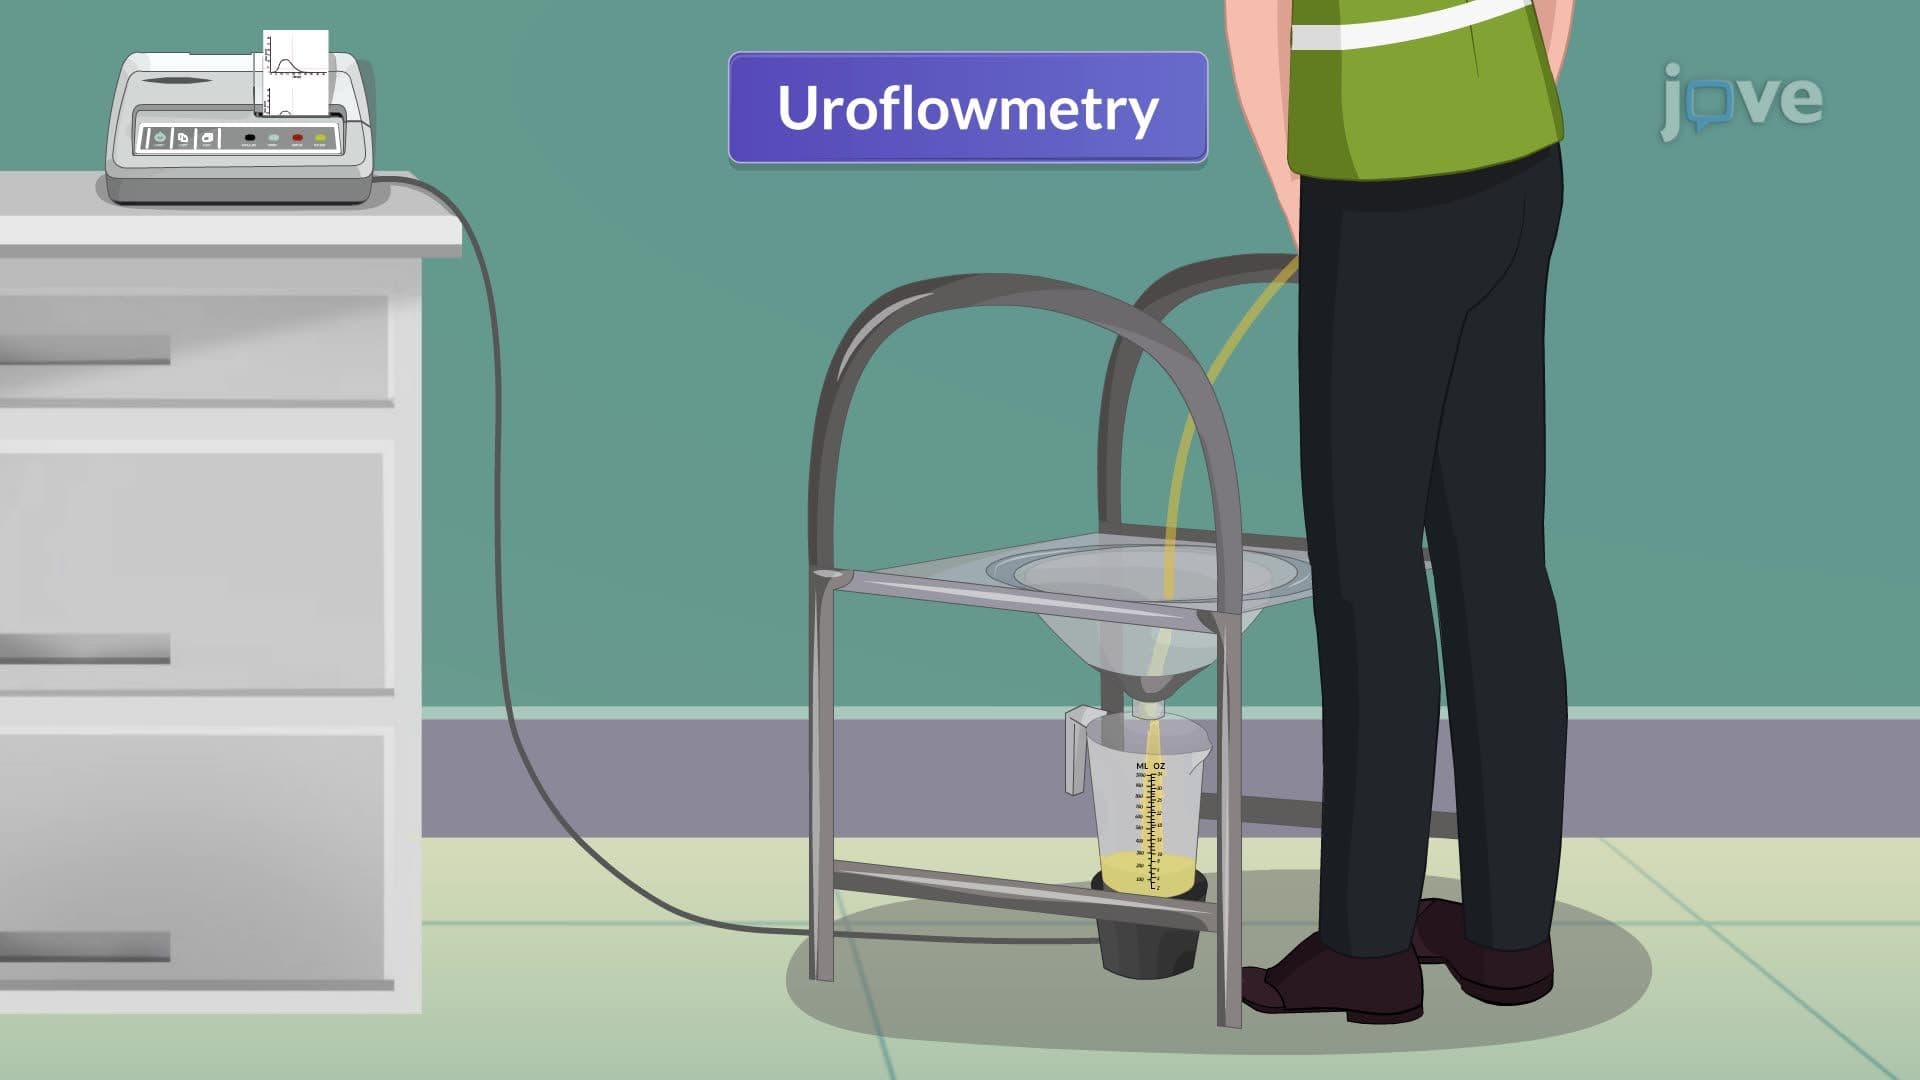
Urodynamic Studies: Uroflowmetry