Related Experiment Video
Updated: Oct 3, 2026
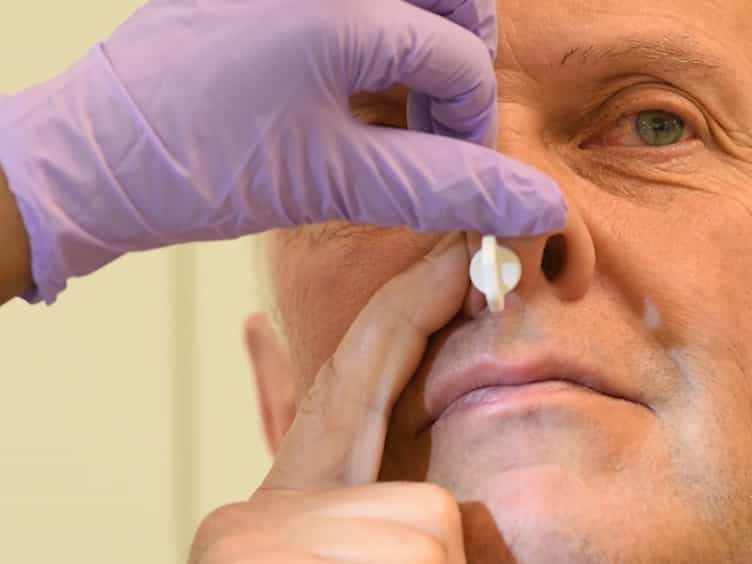
Absorption of Nasal and Bronchial Fluids: Precision Sampling of the Human Respiratory Mucosa and Laboratory Processing of Samples
Published on: January 21, 2018
Rhinovirus-induced airway inflammation in asthma: effect of treatment with inhaled corticosteroids before and during
K Grünberg1, R F Sharon, J K Sont
1Department of Pulmonology, Department of Medical Decision Making, Leiden University Medical Center (LUMC), Leiden, The Netherlands.

Abstract:
Asthma exacerbations are frequently linked to rhinovirus infections. However, the associated inflammatory pathways are poorly understood, and treatment of exacerbations is often unsatisfactory. In the present study we investigated whether antiinflammatory treatment with inhaled corticosteroids prevents any rhinovirus-induced worsening of lower airway inflammation. To that end, we selected 25 atopic patients with mild asthma who underwent experimental rhinovirus 16 (RV16) infection, while receiving double-blind, placebo-controlled treatment with the inhaled corticosteroid budesonide (800 microg twice a day) throughout the study period, starting 2 wk before infection. We assessed inflammatory cell numbers in the bronchial mucosa as obtained by bronchial biopsies 2 d before and 6 d after RV16 infection, and analyzed those in relation to cold symptoms, changes in blood leukocyte counts, airway obstruction, and airway hyperresponsiveness. RV16 colds induced an increase in CD3(+) cells in the lamina propria (p = 0.03) and tended to decrease the numbers of epithelial eosinophils (p = 0.06) in both groups analyzed as a whole. The T cell accumulation was positively associated with cold symptoms. Budesonide pretreatment improved airway hyperresponsiveness (p = 0.02) and eosinophilic airways inflammation (p = 0.04). Yet it did not significantly affect the RV16-associated changes in the numbers of any of the inflammatory cell types. We conclude that RV16 infection by itself induces only subtle worsening of airway inflammation in asthma, which is not improved (or worsened) by inhaled corticosteroids. The latter finding is in keeping with the limited protection of inhaled corticosteroids against acute asthma exacerbations.
Related Concept Videos
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:29
Asthma-I: Introduction
 01:17
Drugs Used in Lower Respiratory Disorders: Overview
Bronchodilators, the first step of respiration enhancement, come in various forms, each with its own mechanism...
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...