Related Experiment Video
Updated: Oct 3, 2026


Glucose-Stimulated Insulin Secretion via Perfusion through the Mice Vasculature with an Intact Pancreas
Published on: July 25, 2025
Diabetes attenuates the minimum anaesthetic concentration (MAC) and MAC-blocking adrenergic response reducing actions
1Department of Anesthesiology, Osaka Medical Center for Cancer and Cardiovascular Diseases, Higashinari, Osaka, Japan. tkita@cvn.bai.ne.jp

Background:
It is well known that clonidine, an alpha2 agonist, reduces anaesthetic requirement and attenuates haemodynamic responses against noxious stimuli. However, the diabetic state is known to affect several functions of alpha2 adrenoceptors. We investigated the effects of streptozotocin (STZ)-induced diabetes mellitus (DM) on these beneficial actions of clonidine in halothane-anaesthetized rats.
Methods:
The rats were randomly assigned to one of three groups: diabetes (n=24, induced by 50 mg x kg(-1) IV STZ), diabetes treated with insulin (n=24), or control (n=24). We evaluated the effects of clonidine on minimum anaesthetic concentration (MAC) and minimum concentration of halothane needed to suppress cardiovascular responses evoked by a noxious stimulus (MAC-blocking adrenergic responses: MAC-BAR) in each group. MAC and MAC-BAR of halothane were determined by the tail clamp method. MAC-BAR was defined as the MAC which attenuated haemodynamic responses within 10% following the tail clamp.
Results:
The diabetic state decreased MAC of halothane by approximately 10%, while MAC-BAR of halothane had been little affected. In the diabetes group, MAC reducing action of clonidine (30 and 100 microg x kg(-1), IV) was completely abolished and MAC-BAR reducing action of clonidine was partially reduced (30 but not 100 microg x kg(-1), IV). Insulin treatment preserved these actions of clonidine.
Conclusion:
It is suggested that the diabetic state attenuates the beneficial actions of clonidine and that insulin treatment of diabetes preserves these actions of clonidine.
Related Concept Videos
 01:28
Drugs Acting on Autonomic Ganglia: Blockers
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:25
Adrenergic Agonists: Indirect-Acting Agents
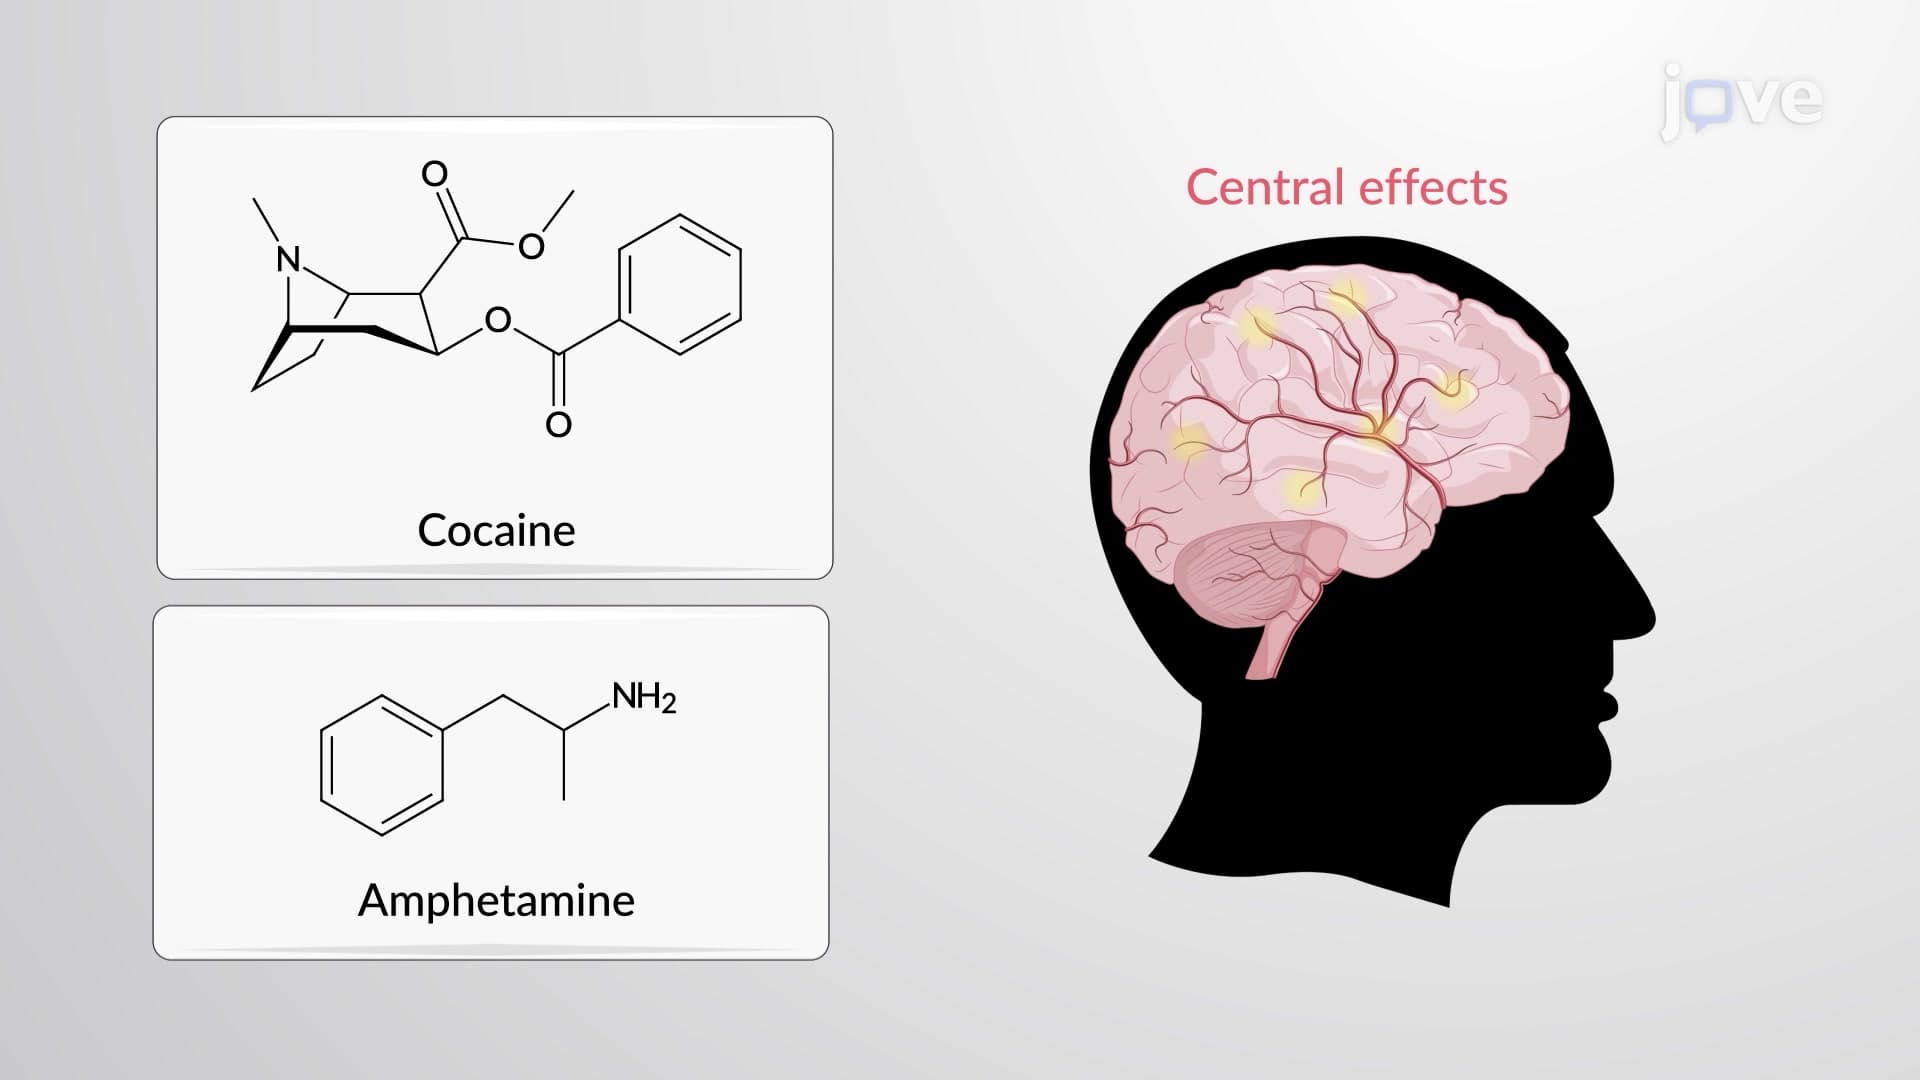
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral bioavailability, and...
 01:19
Depolarizing Blockers: Pharmocokinetics