Related Experiment Video
Updated: Oct 3, 2026
Murine Mesenteric Lymphadenectomy for Selective Disruption of Lymphatic Communication with Region-Specific Gut
Published on: December 30, 2025
Lymphatic ascites following lymphadenectomy for gynecological malignancy
C S Krishnan1, P T Grant, G Robertson
1Department of Gynaecological Oncology, Royal Hospital for Women, Sydney, Australia.

Abstract:
Seven patients seen between January 1995 and December 1998 developed symptomatic lymphatic ascites following either pelvic or para-aortic lymph node dissection. The incidence of symptomatic lymphatic ascites during this 4-year period was 2.7% (7 of 263 cases). The accumulation of ascites postoperatively was associated with a prolonged postoperative ileus, abdominal pain, and extended postoperative hospitalization. Once the condition was recognized, abdominal paracentesis resulted in rapid improvement of symptoms in two patients but repeated paracenteses were required for a further two patients who had significant complications as a result of these procedures. Two patients improved following spontaneous drainage of a large amount of ascites per vagina and did not require further intervention. The final patient settled with observation only. This condition can be difficult to recognize and is a potential cause of significant postoperative morbidity.
Related Concept Videos
 01:19
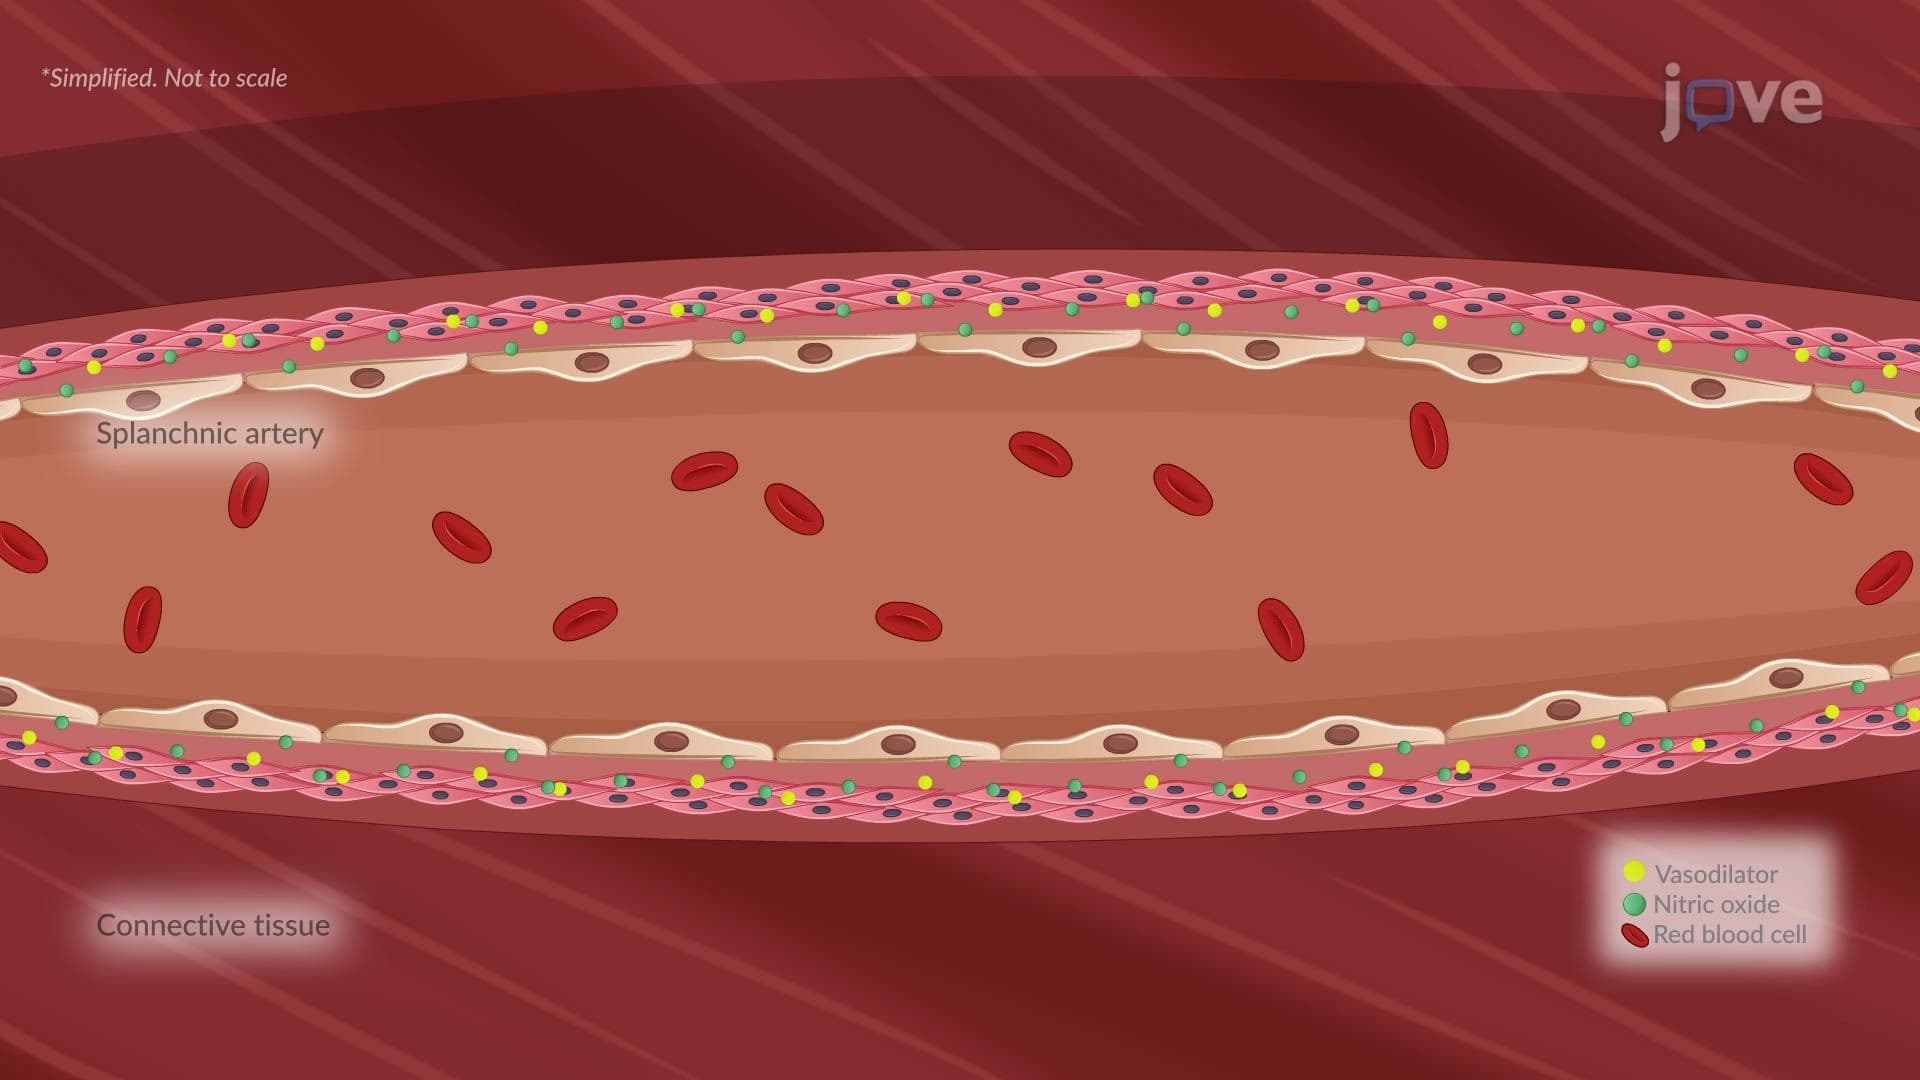
Ascites
 01:16
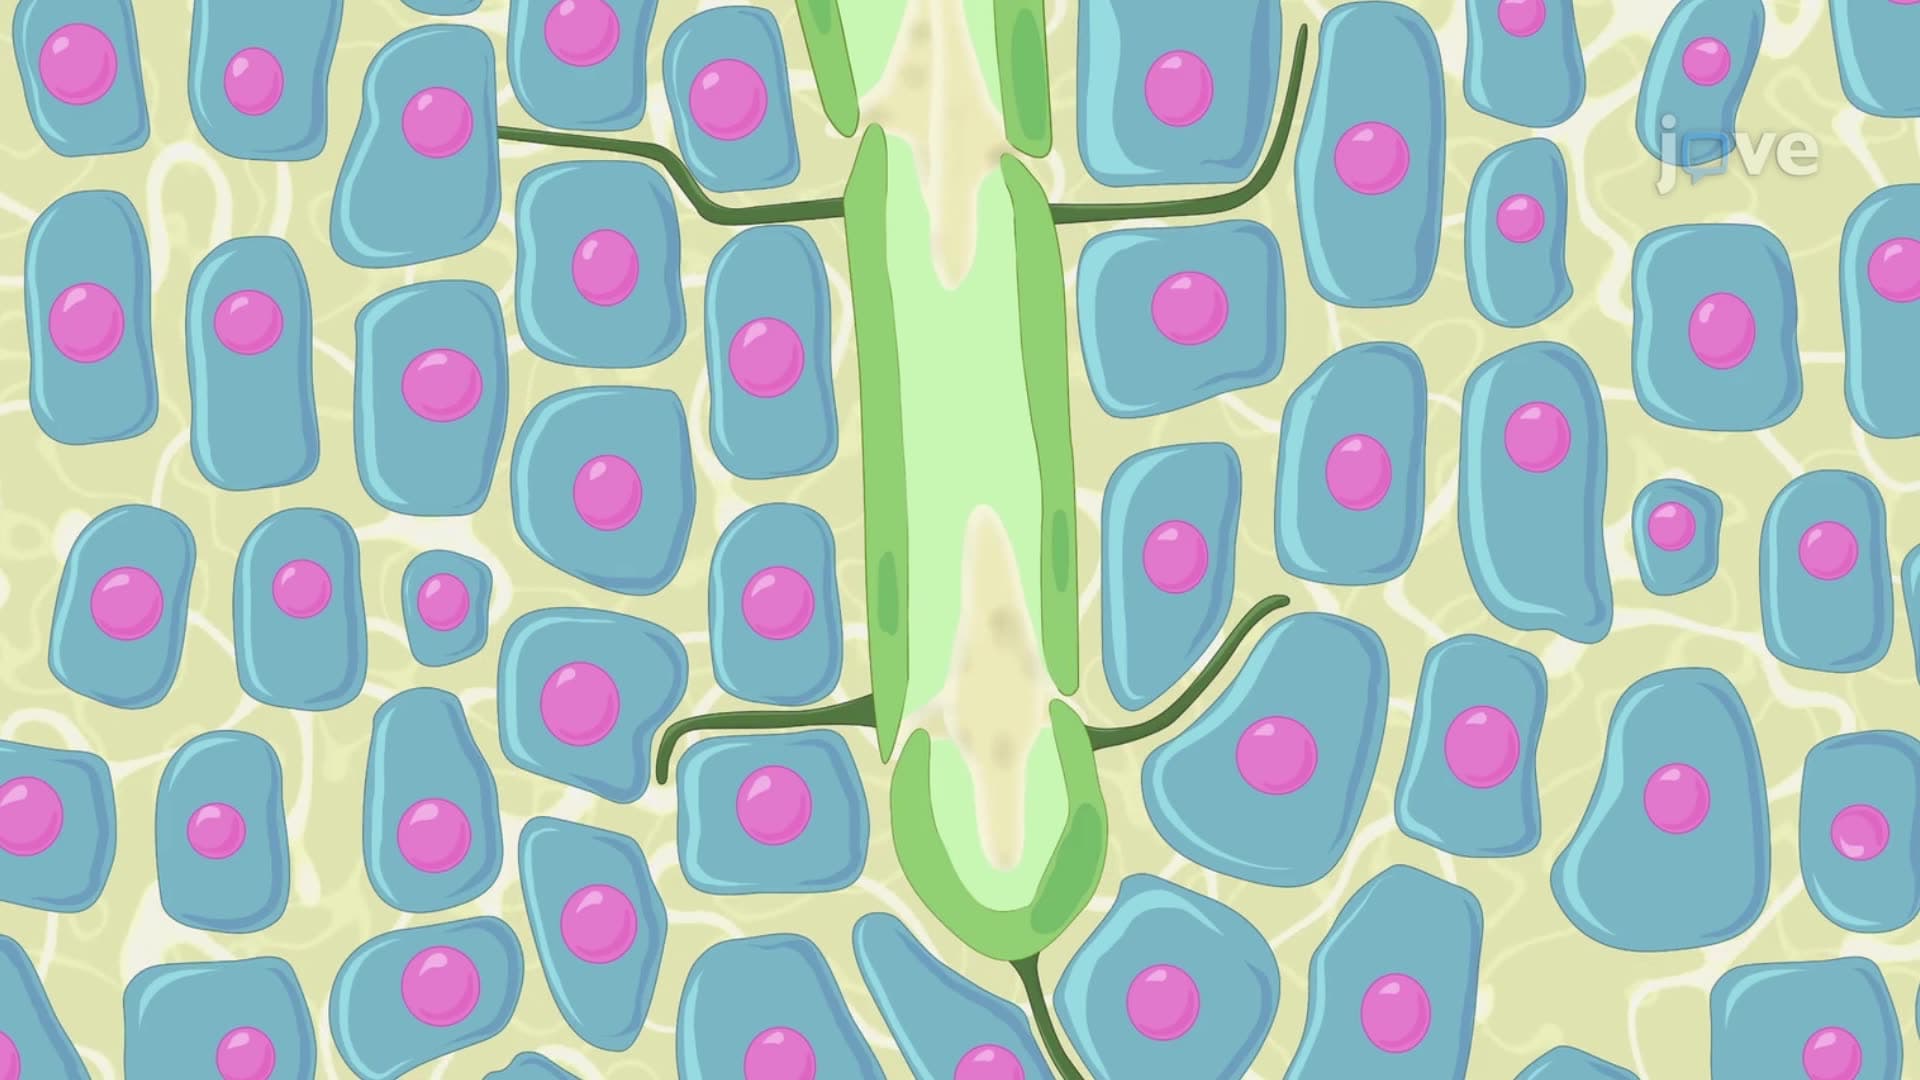
Lymphatic Vessels and Lymph Transport
This one-way system allows fluids, solutes, and even pathogens to enter but prevents their return to the intercellular spaces.
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...