Related Experiment Video
Updated: Aug 7, 2026

Tractable Mammalian Cell Infections with Protozoan-primed Bacteria
Published on: April 2, 2013
Legionella-like and other amoebal pathogens as agents of community-acquired pneumonia
T J Marrie1, D Raoult, B La Scola
1Department of Medicine, University of Alberta, Edmonton, Canada. tom.marrie@ualberta.ca

Abstract:
We tested serum specimens from three groups of patients with pneumonia by indirect immunofluorescence against Legionella-like amoebal pathogens (LLAPs) 1-7, 9, 10, 12, 13; Parachlamydia acanthamoeba strains BN 9 and Hall's coccus; and Afipia felis. We found that LLAPs play a role (albeit an infrequent one) in community-acquired pneumonia, usually as a co-pathogen but sometimes as the sole identified pathogen.
Insights
Legionella-like amoebal pathogens (LLAPs) are infrequently involved in community-acquired pneumonia. These LLAPs can act as a sole pathogen or co-pathogen in pneumonia cases.
Area of Science:
- Microbiology
- Infectious Diseases
- Immunology
Background:
- Community-acquired pneumonia (CAP) is a significant global health concern.
- The etiology of CAP is diverse, involving numerous bacterial, viral, and fungal pathogens.
- The role of less common or emerging pathogens in CAP requires further investigation.
Observation:
- Serum specimens from pneumonia patients were tested using indirect immunofluorescence.
- The testing targeted Legionella-like amoebal pathogens (LLAPs) 1-7, 9, 10, 12, 13.
- Additional targets included Parachlamydia acanthamoeba strains and Afipia felis.
Findings:
- Legionella-like amoebal pathogens (LLAPs) were identified in a subset of pneumonia cases.
- LLAPs were found to play an infrequent role in community-acquired pneumonia.
- In some instances, LLAPs acted as the sole identified pathogen, while in others, they were co-pathogens.
Implications:
- These findings suggest LLAPs should be considered in the differential diagnosis of CAP.
- Further research is warranted to understand the prevalence and clinical significance of LLAPs in pneumonia.
- Improved diagnostic approaches may be needed to detect LLAP infections effectively.


Related Concept Videos
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia II: Pathophysiology
 01:29
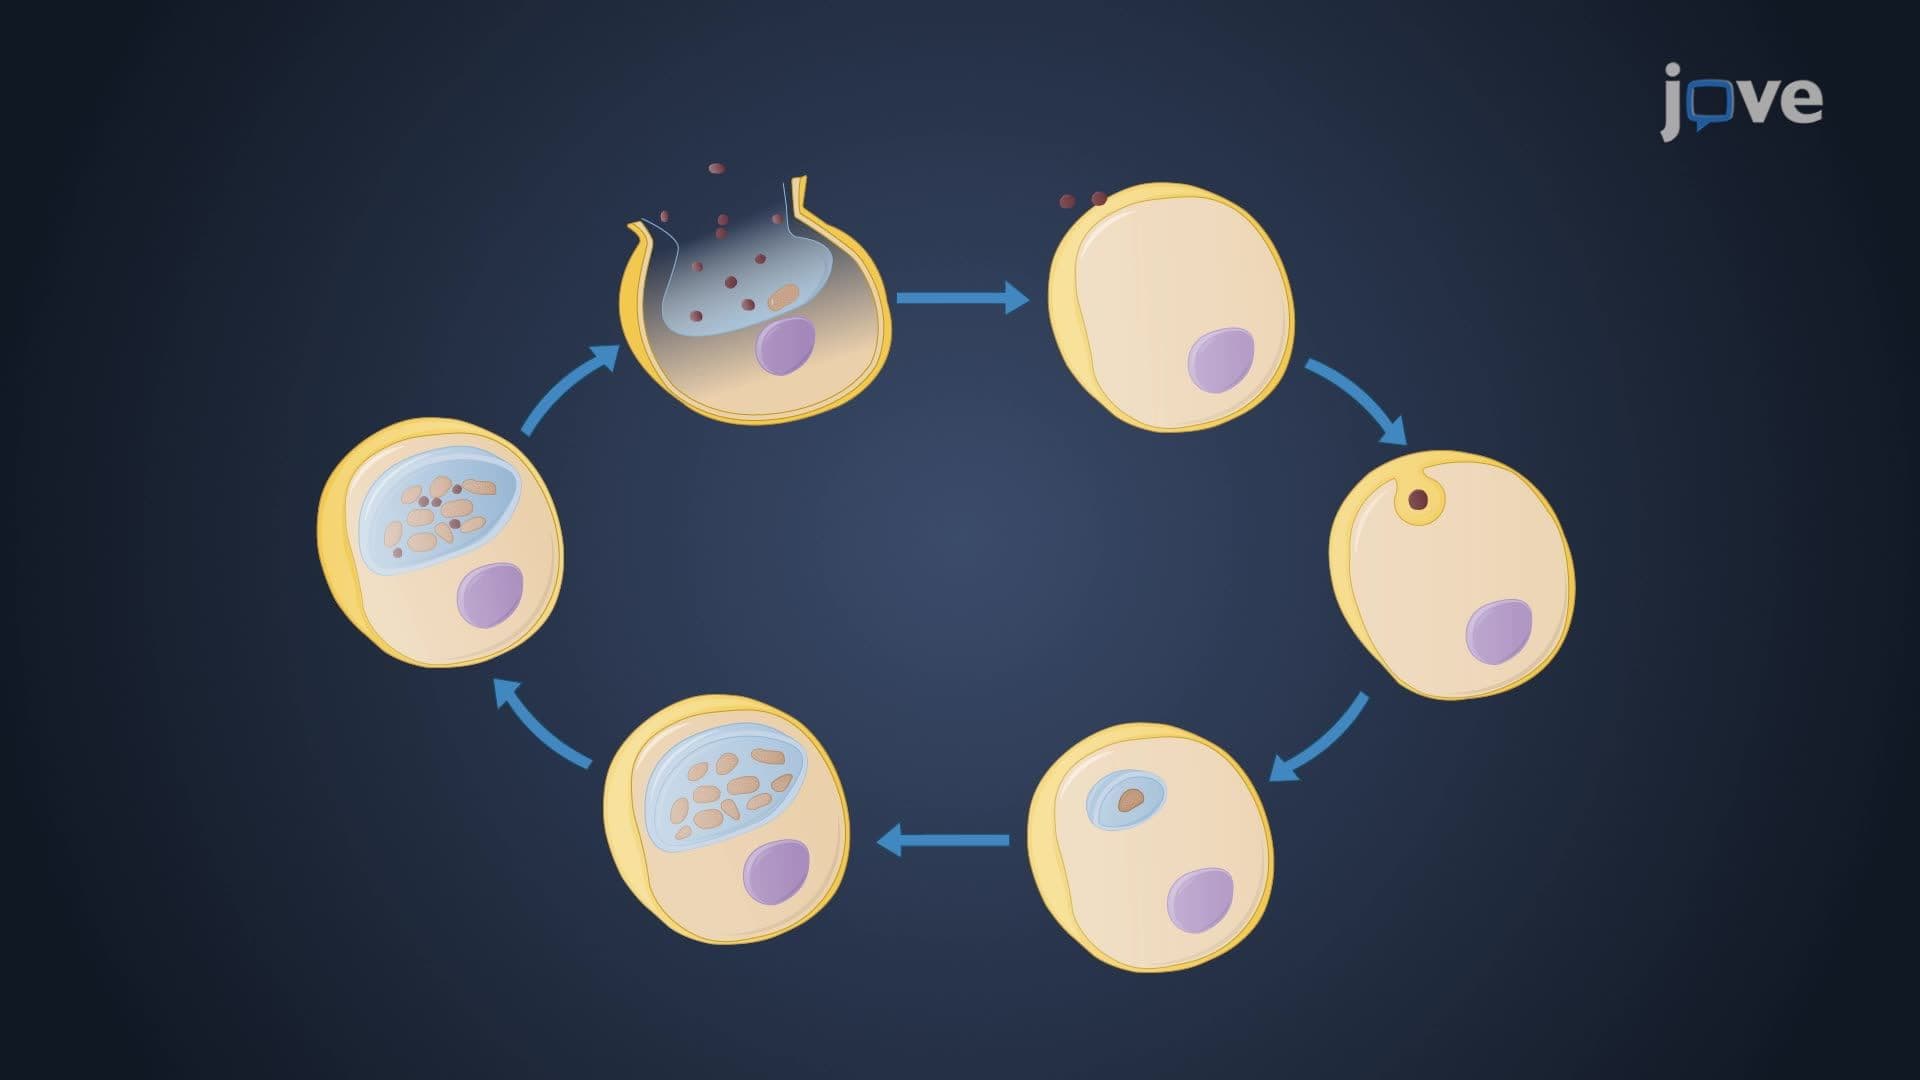
Bacterial Phylum Chlamydiae
 01:14
Atypical Pneumonia
 01:28
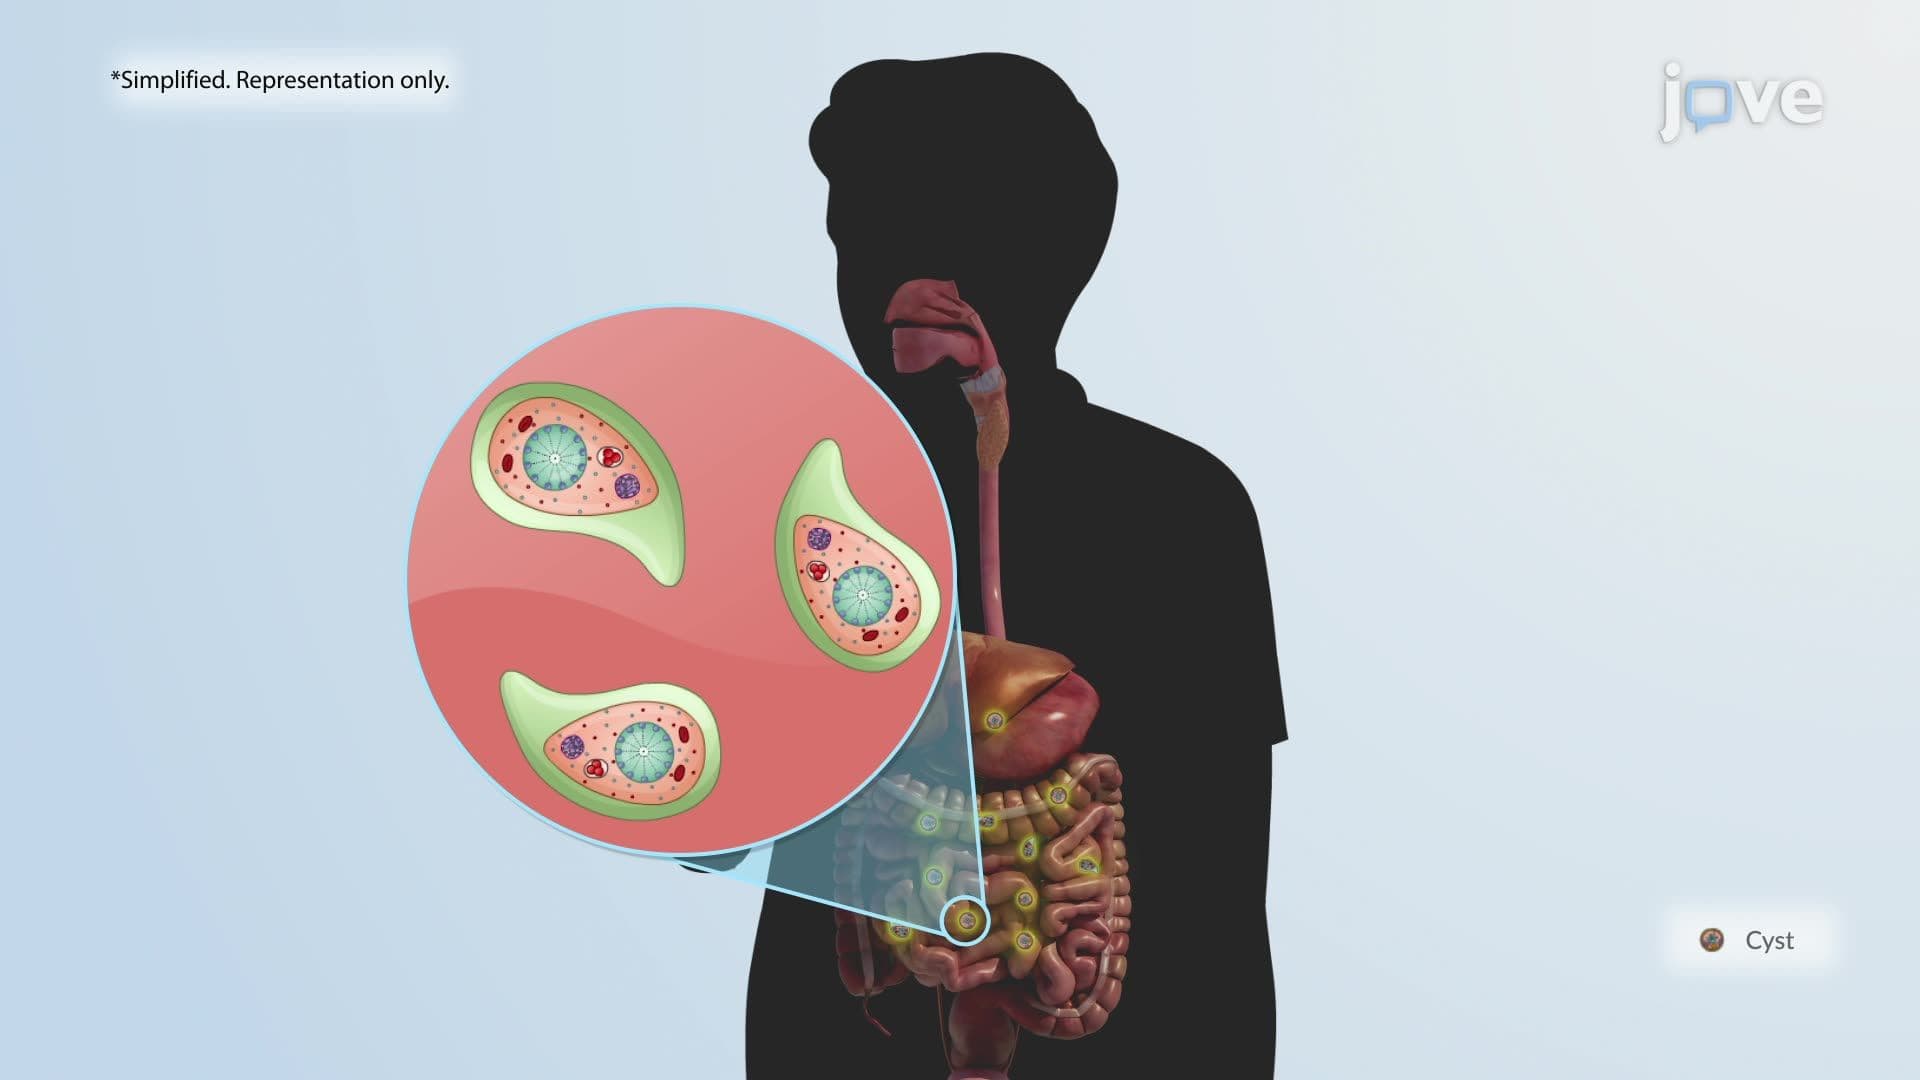
Amebiasis
 01:29
Pneumonia I: Introduction