Related Experiment Video
Updated: Oct 3, 2026


Dynamic Digital Biomarkers of Motor and Cognitive Function in Parkinson's Disease
Published on: July 24, 2019
[A 64-year-old man with parkinsonism as an initial symptom followed by dementia associated with marked abnormal
A Suzuki1, S Ikebe, Y Komatsuzaki
1Department of Neurology, Juntendo University School of Medicine, 2-1-1 Hongo, Bunkyo, Tokyo 113-8421, Japan.

Abstract:
We report a 64-year-old man with parkinsonism as an initial symptom, which was followed by dementia and abnormal behaviours. He was well until 1985, when he was 49 years old, when he noted rest tremor in his right hand. Soon tremor appeared in his left hand as well. He was seen in our clinic and levodopa was prescribed. He was doing well with this medication, however, in 1993, he started to suffer from on-off phenomenon. He also noted visual hallucination. In 1994, he stole a watermelon and ate it in the shop. He repeated such abnormal behaviours. In 1995, he was admitted to the neurology service of Hatsuishi Hospital. On admission, he was alert and oriented. He did not seem to be demented; however, he admitted stealing and hypersexual behaviours. No aphasia, apraxia, or agnosia was noted. In the cranial nerves, downward gaze was markedly restricted. He showed masked and seborrhoic face, and small voice. No motor palsy was noted, but he walked in small steps with freezing and start hesitation. Marked neck and axial rigidity was noted. Tremor was absent except for in the tongue. No cerebellar ataxia was noted. Deep tendon reflexes were diminished. Plantar response was extensor bilaterally. Forced grasp was noted also bilaterally. He was treated with levodopa and pergolide, but he continued to show on-off phenomenon. His balance problem and akinesia became progressively worse; still he showed hypersexual behaviour problems. He also showed progressive decline in cognitive functions. In 1997, he started to show dysphagia. He developed aspiration pneumonia in July of 1998. In 1999, he developed emotional incontinence and became unable to walk. He also developed repeated aspiration pneumonia. He died on March 1, 2000. He was discussed in a neurological CPC and the chief discussant arrived at a conclusion that the patient had corticobasal degeneration. Other diagnoses entertained included dementia with Lewy bodies, diffuse Lewy body disease, and frontotemporal dementia. Majority of the participants thought that diffuse Lewy body disease was most likely. Post-mortem examination revealed marked nigral neuronal loss, gliosis and Lewy bodies in the remaining neurons. Abundant Lewy bodies of cortical type were seen wide spread in the cortical areas, but particularly many in the amygdaloid nucleus. Lewy bodies were also seen in the subcortical structures such as the dorsal motor nucleus, oculomotor nucleus, Meynert nucleus, putamen, and thalamus. What was interesting was marked neuronal loss of the pontine nuclei, demyelination of the pontocerebellar fiber, and moderate neuronal loss of the cerebellar Purkinje neurons, a reminiscent of pontocerebellar atrophy. However, the inferior olivary nucleus was intact.
Insights
This case study details a patient with parkinsonism, dementia, and behavioral changes, ultimately diagnosed with diffuse Lewy body disease post-mortem, characterized by widespread Lewy bodies and neuronal loss.
Area of Science:
- Neurology
- Neuroscience
- Pathology
Background:
- Parkinsonism can present with diverse initial symptoms, including tremor and rigidity.
- Cognitive decline and behavioral abnormalities can emerge in later stages of neurodegenerative diseases.
Observation:
- A 64-year-old man initially presented with parkinsonism, progressing to dementia, visual hallucinations, and disinhibition (e.g., stealing).
- Clinical examination revealed restricted downward gaze, masked facies, hypophonia, gait freezing, axial rigidity, and diminished reflexes.
- Despite treatment with levodopa and pergolide, the patient experienced worsening motor symptoms, cognitive decline, dysphagia, and aspiration pneumonia.
Findings:
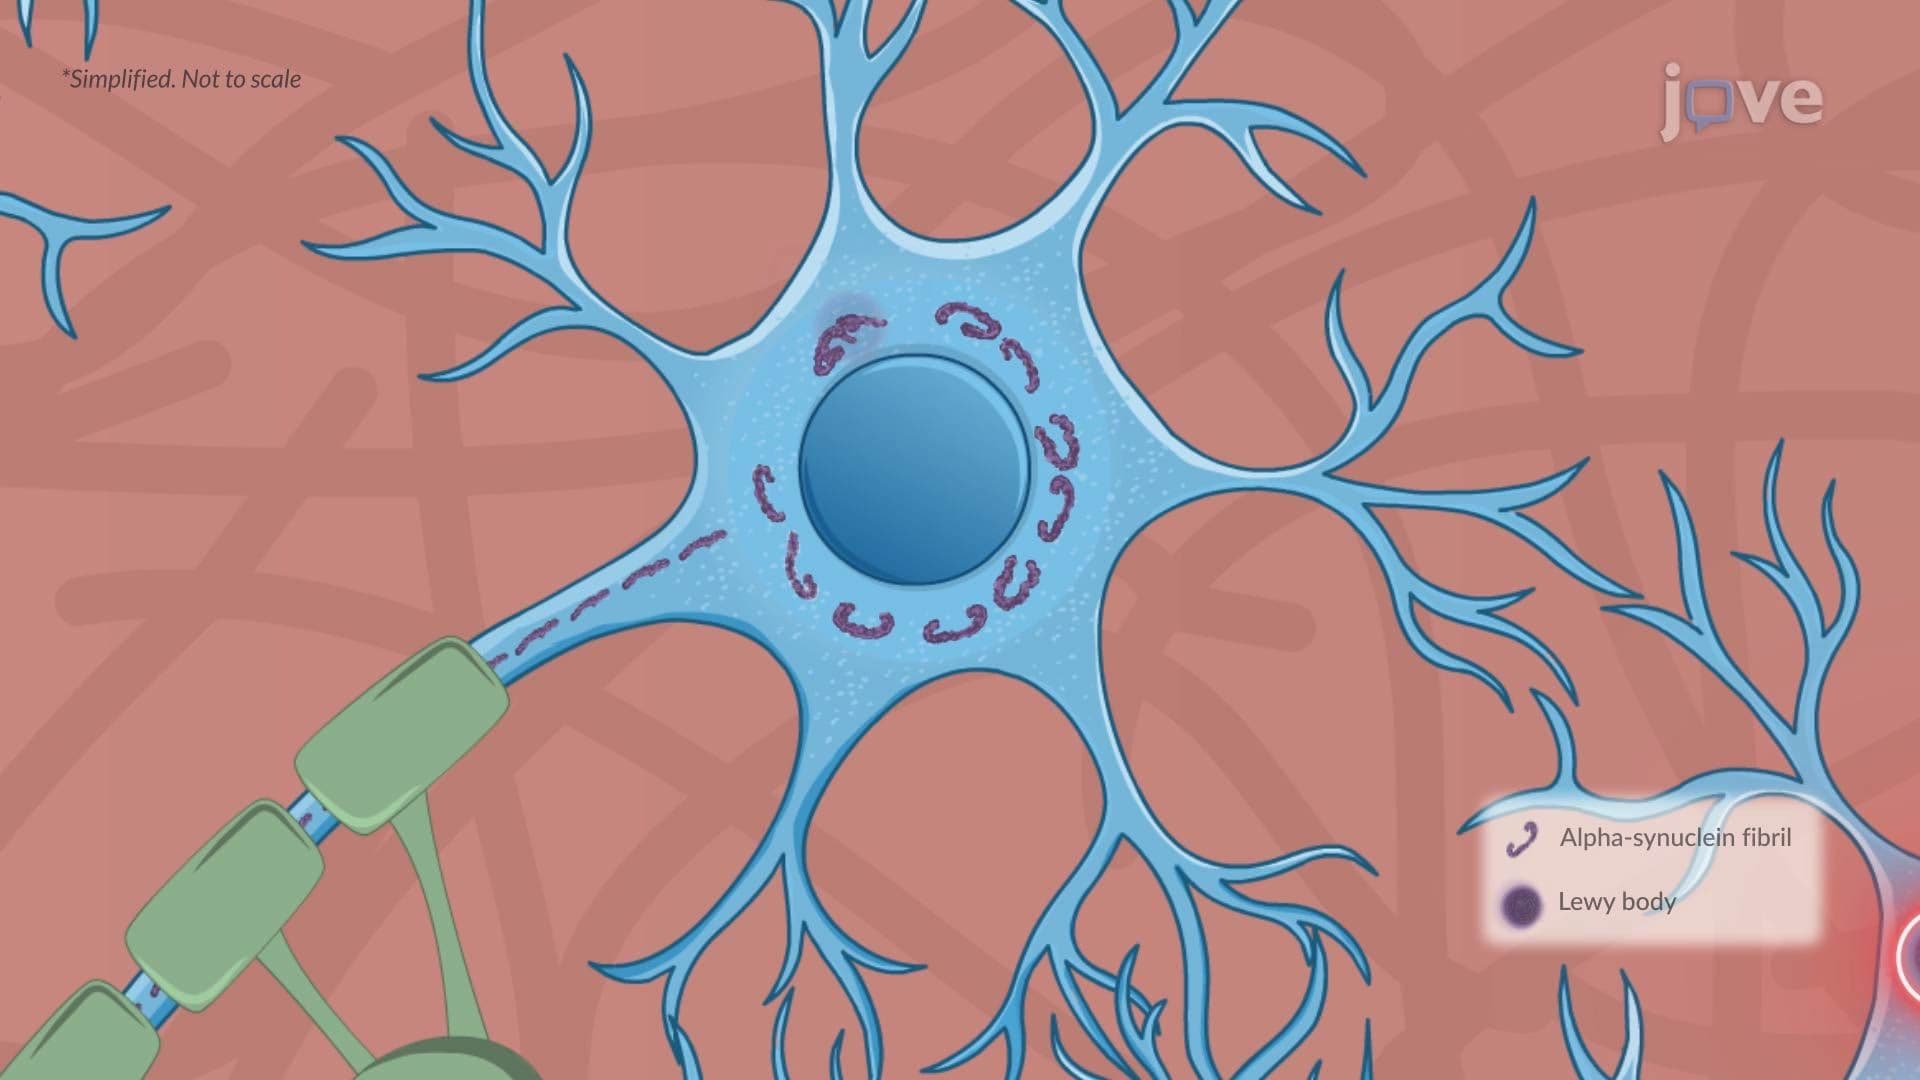
- Post-mortem examination confirmed marked nigral neuronal loss, gliosis, and widespread cortical Lewy bodies, particularly in the amygdala.
- Subcortical Lewy bodies were observed in various nuclei, alongside pontine nuclei neuronal loss and cerebellar Purkinje cell loss.
- The pathological findings were most consistent with diffuse Lewy body disease, though corticobasal degeneration and frontotemporal dementia were considered.
Implications:
- This case highlights the complex clinical presentation of diffuse Lewy body disease, emphasizing the overlap with other parkinsonian syndromes.
- The pathological findings underscore the widespread neurodegeneration affecting both cortical and subcortical structures in this condition.
- Understanding these diverse manifestations is crucial for accurate diagnosis and management of patients with parkinsonism and dementia.
Related Concept Videos
 01:24
Parkinson Disease l: Introduction
 01:15
Parkinson's Disease: Overview
 01:22
Dementia l: Introduction
 01:30
Dementia
The progression of dementia is generally gradual.
 01:29
Alzheimer Disease l: Introduction
 01:24
Parkinson Disease ll: Pathophysiology