Related Experiment Video
Updated: Aug 17, 2026
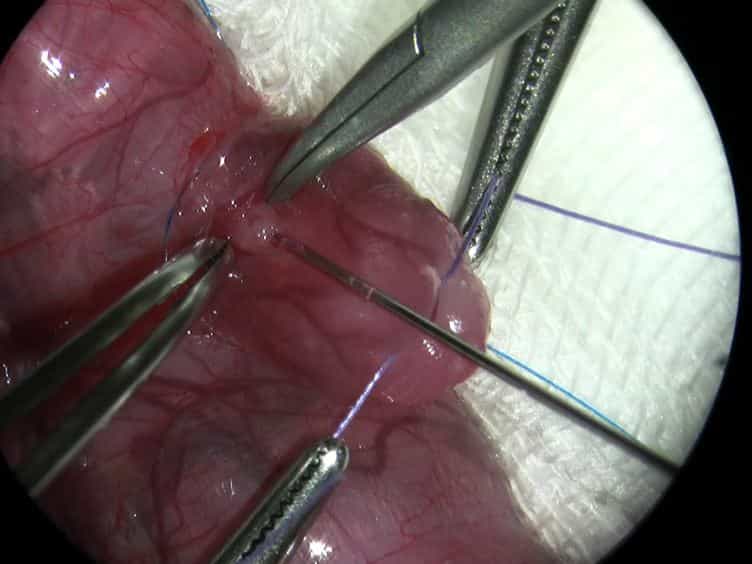
A Novel Surgical Approach for Intratracheal Administration of Bioactive Agents in a Fetal Mouse Model
Published on: October 31, 2012
Is there a role for antenatal TRH therapy for the prevention of neonatal lung disease?
1Department of Pediatrics and Children's Clinical Research Center, Yale University School of Medicine, New Haven, CT 06520, USA. ian.gross@yale.edu

Insights
Antenatal thyrotropin-releasing hormone (TRH) plus glucocorticoid therapy may reduce respiratory distress syndrome in infants when surfactant is unavailable. This combination therapy showed significant benefits in presurfactant trials, particularly for infants born 1-10 days after treatment.
Area of Science:
- Neonatal Medicine
- Endocrinology
- Pharmacology
Background:
- Surfactant therapy is crucial for treating respiratory distress syndrome (RDS) in preterm infants but is not universally accessible due to cost.
- Antenatal glucocorticoid therapy is a standard treatment to mature fetal lungs, but its efficacy can be enhanced.
- Thyrotropin-releasing hormone (TRH) is a potential adjunct to antenatal glucocorticoid therapy.
Purpose of the Study:
- To evaluate the efficacy of antenatal thyrotropin-releasing hormone (TRH) combined with glucocorticoid therapy as an alternative to surfactant therapy for preventing respiratory distress syndrome (RDS).
- To analyze data from randomized clinical trials comparing antenatal glucocorticoid plus TRH versus glucocorticoid alone, with and without surfactant use.
- To assess the impact of this combined therapy on neonatal outcomes and maternal complications.
Main Methods:
- Meta-analysis of randomized clinical trials comparing antenatal glucocorticoid plus TRH with glucocorticoid alone.
- Separate analyses were conducted for trials with and without surfactant therapy, including subgroup analysis excluding the ACTOBAT trial data.
- Data were examined for "intention to treat" and specific delivery time windows post-therapy (1-10 days).
Main Results:
- In presurfactant trials, antenatal TRH plus glucocorticoid significantly decreased respiratory distress syndrome (RDS), especially in infants born 1-10 days after treatment.
- Significant reductions in oxygen dependency at 28 days and combined oxygen dependency or death were observed in the same subgroup.
- Antenatal TRH did not significantly affect other neonatal complications but caused transient maternal side effects and suppressed the pituitary-thyroid axis.
Conclusions:
- Antenatal glucocorticoid treatment remains the priority for fetal lung maturation.
- The addition of antenatal TRH to glucocorticoid therapy should be considered in settings where surfactant is unavailable, particularly for infants born within 1-10 days of treatment.
- While effective, the potential transient maternal side effects and pituitary-thyroid axis suppression associated with TRH warrant careful consideration.
Abstract:
Unfortunately, surfactant therapy is not routinely available to infants in some parts of the world because of its cost. It is the hypothesis of this article that in situations where surfactant is not available, there may be a role for antenatal thyrotropin-releasing hormone (TRH) plus glucocorticoid therapy. Data from randomized clinical trials, which compared therapy with antenatal glucocorticoid plus TRH to that with glucocorticoid alone were extracted and subjected to meta-analysis. The trials that incorporated surfactant therapy were analyzed separately from those in which surfactant was not used. In addition, because surfactant therapy was only available to some patients in the Australian ACTOBAT trial, each group analysis was performed with and without the ACTOBAT data. A characteristic of the earlier presurfactant trials is that few were designed for "intention to treat" analysis. In most of these studies, it was decided a priori to include babies who delivered within a specified time period after hormone therapy. The addition of TRH did not decrease respiratory distress syndrome in those trials in which surfactant therapy was used. In the presurfactant trials, respiratory distress syndrome was significantly decreased when "intention to treat" data were examined, as well as in those infants who delivered between 1 and 10 days after maternal therapy. There was also a significant decrease in oxygen dependency at 28 days after birth, and in oxygen dependency or death at this time, in those infants who delivered 1 to 10 days after treatment. Antenatal TRH had no significant effect of on neonatal complications such as air leak, intraventricular hemmorhage, patent ductus arteriosus, retinopathy of prematurity, or necrotizing enterocolitis. However, TRH did produce transient suppression of the pituitary thyroid axis. There were also a variety of transient complications in the mothers, including nausea, vomiting or flushing, light-headed feeling, and increased blood pressure. The authors conclude that the implementation of appropriate antenatal glucocorticoid treatment is the first priority. Once this has been established, the data presented here suggest that addition of antenatal TRH should be considered in those situations where surfactant is not available.


Related Concept Videos
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by anesthetizing...
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme (ECE). Of...
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:29
Microbiota of the Respiratory Tract