[Respiratory emergencies in infants]
Related Experiment Video
Updated: Oct 3, 2026
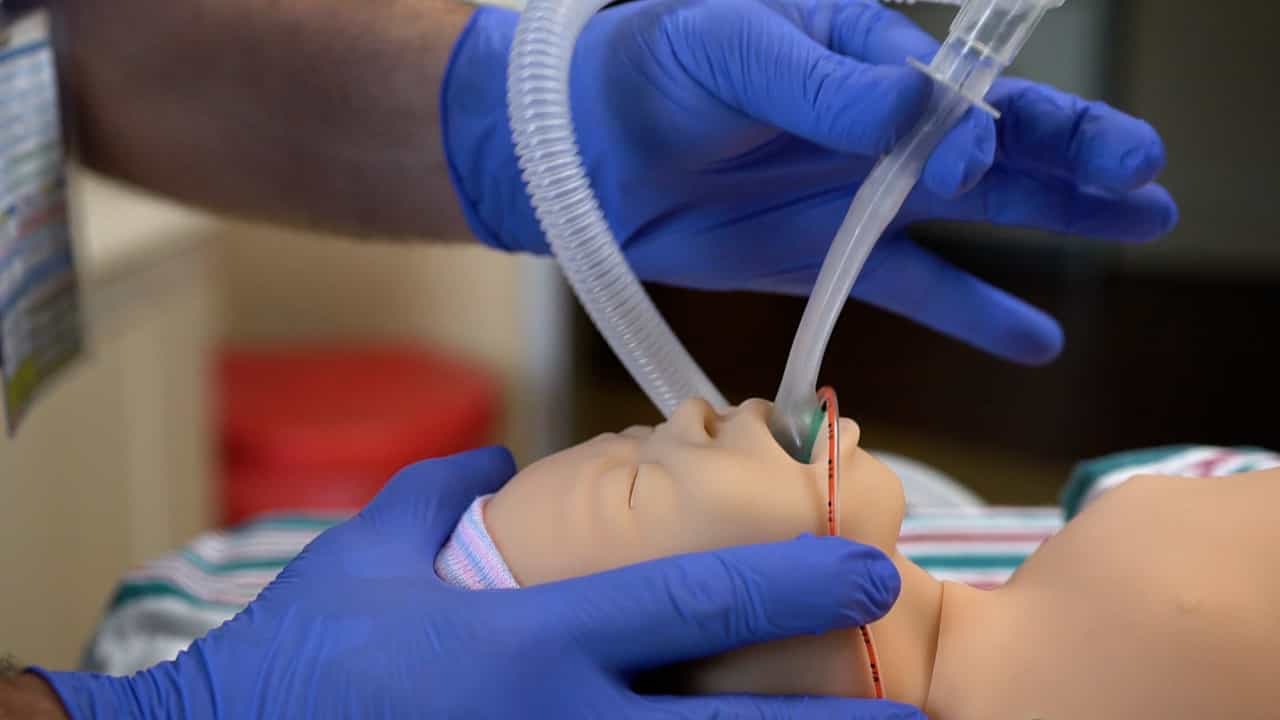
Laryngeal Mask Airway (LMA) Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway (SGA)
Published on: July 14, 2023
B Llanas1, P Pillet, L Pedespan
1Service des urgences pédiatriques, Hôpital des enfants Pellegrin 33 076 Bordeaux. brigitte.llanas@chu-bordeaux.fr

Insights
Rapid evaluation of childhood respiratory distress is crucial for prompt intervention, preventing severe outcomes like cardiac arrest. Common causes include nasal obstruction, laryngitis, and acute viral bronchiolitis, with inhaled foreign bodies a key diagnostic consideration.
Area of Science:
- Pediatrics
- Emergency Medicine
- Pulmonology
Context:
- Childhood respiratory distress is a common emergency department admission.
- Timely clinical assessment is vital for effective management.
- Recognizing common etiologies and potential hazards is essential.
Purpose:
- To outline the critical initial management of pediatric respiratory distress.
- To highlight frequent causes and diagnostic considerations.
- To emphasize the importance of prevention and awareness.
Summary:
- Respiratory distress in children necessitates rapid evaluation to initiate interventions, preventing hypoxic complications. Common causes vary by age, including nasal obstruction (infants) and laryngitis (older infants).
- Acute viral bronchiolitis is a prevalent winter illness in infants, while inhaled foreign bodies require constant diagnostic suspicion. Prevention strategies involve educating families and healthcare providers on inhalation risks.
- Effective management hinges on prompt diagnosis and intervention, addressing conditions like bronchiolitis and potential foreign body aspiration to improve patient outcomes.
Impact:
- Improves emergency department protocols for pediatric respiratory distress.
- Reduces morbidity and mortality associated with severe respiratory events in children.
- Enhances awareness and preventative measures regarding childhood inhalation hazards.
Abstract:
Respiratory distress in childhood is a frequent cause of admission to the emergency department. The initial management requires a rapid clinical evaluation in order to initiate appropriate interventions, which will improve respiratory status, and avoid cardiac arrest and hypoxic encephalopathy. There are many possible etiologies but in the vast majority of cases the following conditions are observed: nasal obstruction before 3 months and laryngitis after 6 months. Moreover, during winter acute viral bronchiolitis is the most common disease of the respiratory tract during the first year of life, and occurs in annual epidemics. The diagnostic of an inhaled foreign body must always be suspected. Prevention is based upon information given to families, as well as the medical community, which often minimises the seriousness of inhalation hazards.
Related Concept Videos
 01:23
Acute Respiratory Failure-IV
 01:30
Acute Respiratory Failure-III
 01:17
Pulmonary Cycle: Exhalation
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: