Related Experiment Video
Updated: Aug 16, 2026


Following in Real Time the Impact of Pneumococcal Virulence Factors in an Acute Mouse Pneumonia Model Using Bioluminescent Bacteria
Published on: February 23, 2014
The emerging role of atypical pathogens in community-acquired pneumonia
1College of Pharmacy, University of Minnesota, Minneapolis, USA.

Abstract:
Community-acquired pneumonia (CAP) constitutes a major cause of morbidity and mortality. Although Streptococcus pneumoniae remains the bacterium most commonly implicated in CAP, the atypical respiratory pathogens Mycoplasma pneumoniae, Legionella species, and Chlamydia pneumoniae are being isolated with increasing frequency Contrary to previous beliefs, these agents are capable of causing severe as well as mild-to-moderate illness. Moreover, they can affect all age groups. Indeed, atypical pathogens are implicated in up to 40% of CAP cases and commonly occur as copathogens in mixed-infection CAP, an etiology associated with particularly high mortality (up to 25%). Laboratory methods for detecting atypical pathogens are slow, and there is significant overlap between atypical and typical CAP manifestations. For these reasons, accurate prediction of etiology cannot be made purely on clinical or radiologic grounds. Consequently, empiric antimicrobial therapy for atypical pathogens (with agents such as macrolides, fluoroquinolones, in some cases tetracyclines, or the new ketolides) warrants careful consideration and now is recommended for the treatment of CAP.
Insights
Atypical pathogens like Mycoplasma pneumoniae cause severe community-acquired pneumonia (CAP) in all ages. Empiric treatment for these pathogens is now recommended for CAP management.
Area of Science:
- Infectious Diseases
- Pulmonology
- Microbiology
Background:
- Community-acquired pneumonia (CAP) is a significant cause of illness and death.
- Streptococcus pneumoniae is the most common cause, but atypical pathogens are increasingly recognized.
- Atypical pathogens, including Mycoplasma pneumoniae, Legionella, and Chlamydia, cause a spectrum of illness and affect all age groups.
Purpose of the Study:
- To highlight the growing importance of atypical pathogens in CAP.
- To emphasize their role in severe and mixed infections.
- To underscore the need for considering atypical pathogens in empiric treatment strategies.
Main Methods:
- Review of current literature and clinical observations regarding CAP etiology.
- Analysis of the clinical presentations and diagnostic challenges associated with atypical pathogens.
- Evaluation of antimicrobial treatment recommendations.
Main Results:
- Atypical pathogens are implicated in up to 40% of CAP cases.
- They can cause severe illness and are often co-pathogens in mixed infections, associated with high mortality.
- Laboratory detection is slow, and clinical differentiation from typical CAP is difficult.
Conclusions:
- Empiric antimicrobial therapy targeting atypical pathogens is crucial for CAP management.
- Agents like macrolides, fluoroquinolones, tetracyclines, and ketolides should be considered.
- Accurate prediction of etiology solely on clinical or radiologic grounds is not feasible.
More Related Videos


Related Concept Videos
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia II: Pathophysiology
 01:30
Pneumonia III: Complications and Assessment
 01:29
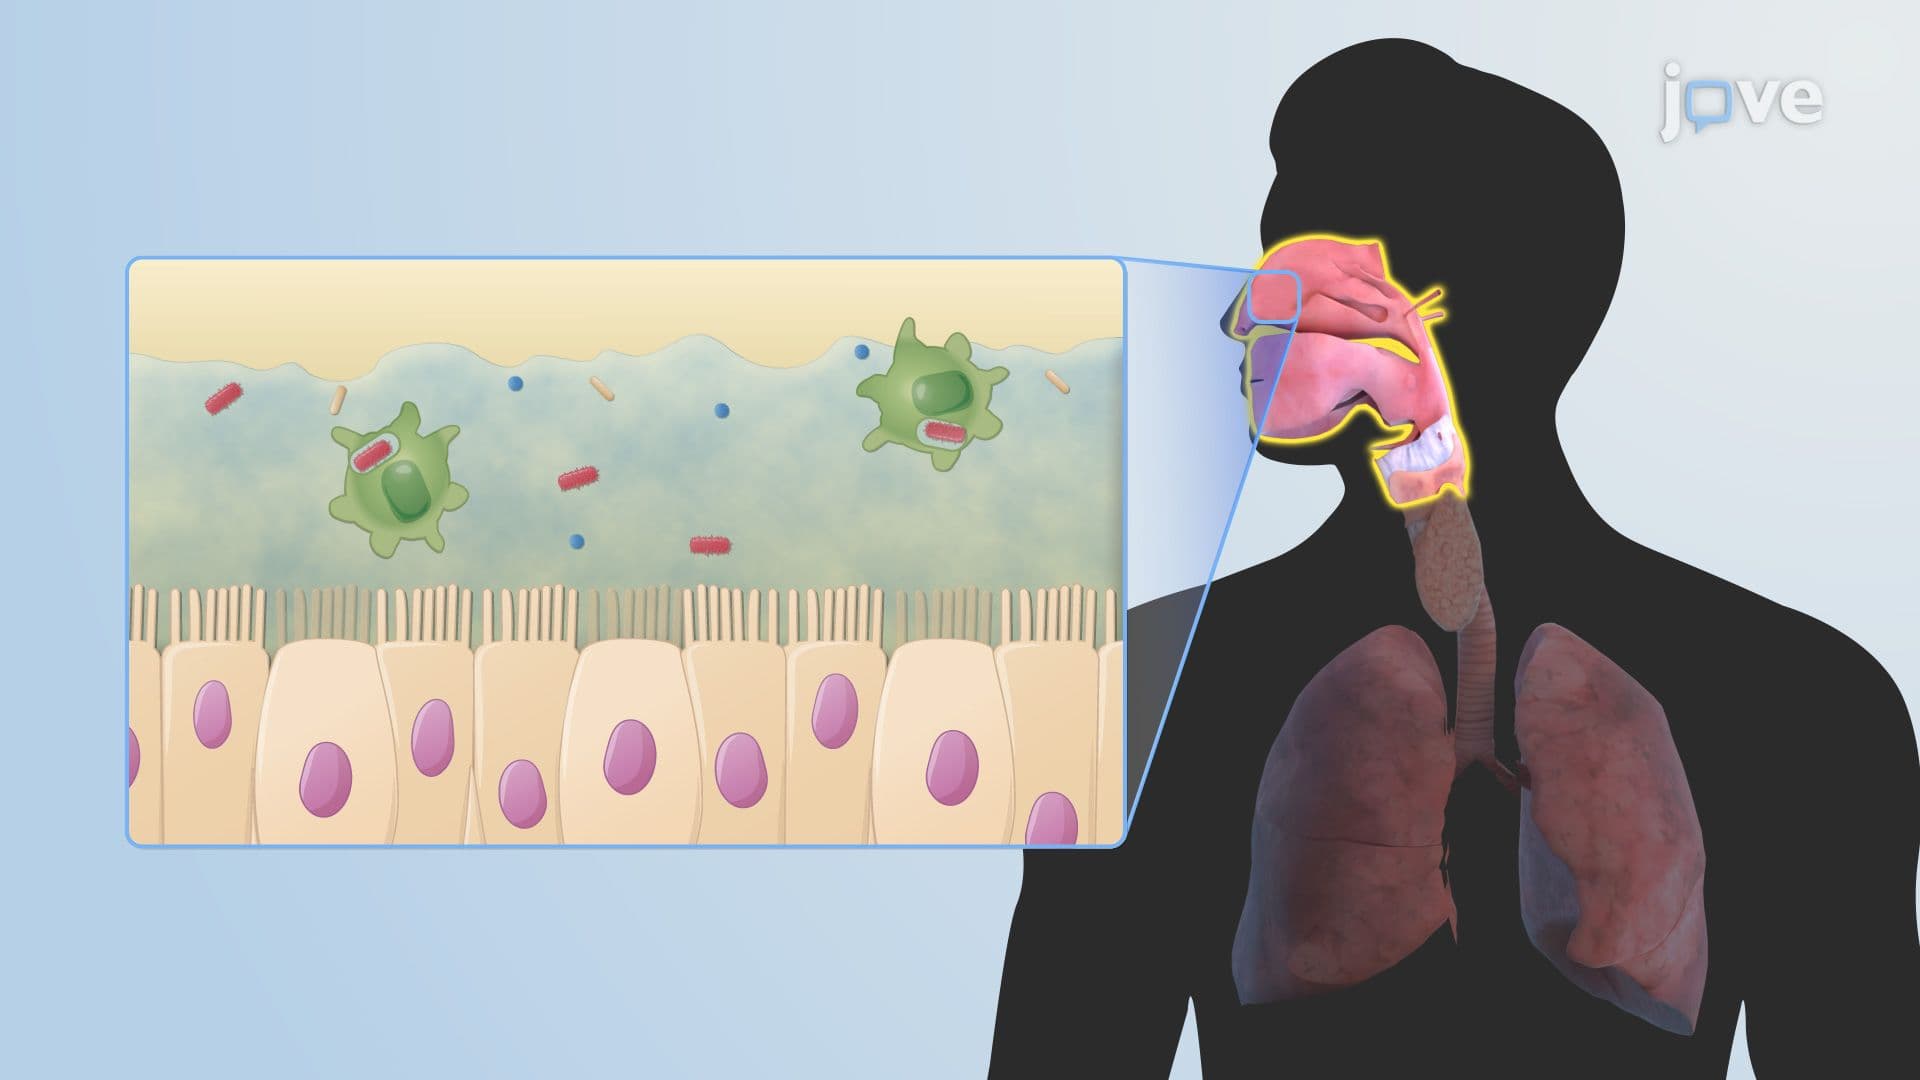
Microbiota of the Respiratory Tract
 01:14
Atypical Pneumonia
 01:29
Pneumonia I: Introduction