Total fluoride intake and urinary excretion in German children aged 3-6 years
Related Experiment Video
Updated: Oct 2, 2026
Impact of Common Fruit Juices and Toothbrushing on the Discoloration of Primary Teeth
Published on: March 27, 2026
M Haftenberger1, G Viergutz, V Neumeister
1Department of Paediatric Dentistry, University of Technology, Dresden, Germany.

Insights
Few studies examine total fluoride intake and urinary excretion in preschoolers. This study found preschoolers excrete about half of ingested fluoride, highlighting the need for larger studies on fluoride exposure and excretion rates.
Area of Science:
- Pediatric Nutrition
- Environmental Health
- Toxicology
Background:
- Limited research exists on total fluoride intake and urinary excretion in preschool-aged children.
- Existing studies present conflicting results regarding fluoride metabolism in this age group.
Purpose of the Study:
- To assess total daily fluoride intake from various sources in healthy preschool children.
- To determine the proportion of ingested fluoride excreted in urine among these children.
Main Methods:
- Utilized the duplicate-diet approach to measure fluoride intake from food and beverages.
- Calculated fluoride intake from toothbrushing by quantifying swallowed toothpaste and rinsing water.
- Recorded the use of fluoridated salt and fluoride supplements.
Main Results:
- Average daily fluoride intake from food was 202.5 ± 116.2 µg F/day.
- Average swallowed fluoride during toothbrushing was 273.9 ± 175.6 µg F/day.
- Total daily fluoride ingestion averaged 930.7 ± 391.5 µg (53.0 ± 21.4 µg/kg body weight).
- Approximately 51.5% of ingested fluoride was excreted in urine.
Conclusions:
- Preschool children excrete a significant proportion of their total fluoride intake via urine.
- Wide inter-individual variations in fluoride excretion necessitate further investigation in larger populations with diverse fluoride exposure levels.
Abstract:
There have only been few investigations comparing total fluoride intake and the fluoride proportion excreted in urine in pre-school children. In addition, the results of available studies are conflicting. Total fluoride intake was assessed in 11 healthy children aged 3-6 years on 2 consecutive days and urinary fluoride excretion was determined. The duplicate-diet approach was used for the assessment of fluoride intake from solid and liquid foods. Fluoride intake from toothbrushing was calculated as the difference between the amount of fluoride in the paste put on the toothbrush and the drinking water (fluoride concentration 0.25 mg/l) used for rinsing vs. the fluoride amounts recovered in the toothpaste spat out and in the rinsing water. Use of fluoridated domestic salt and/or fluoride tablets was recorded. The children's intake of fluoride from food averaged 202.5+/-116.2 microg F/day. They swallowed an average amount of 273.9+/-175.6 microg F/day when brushing their teeth. Daily fluoride ingestion from all sources totalled 930.7+/-391.5 microg or 53.0+/-21.4 microg/kg body weight. On average 51.5% of the fluoride ingested was excreted in urine. The wide interindividual variation makes it necessary to evaluate the urinary excretion rate for fluoride in larger study populations with varied fluoride exposure.
Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:11
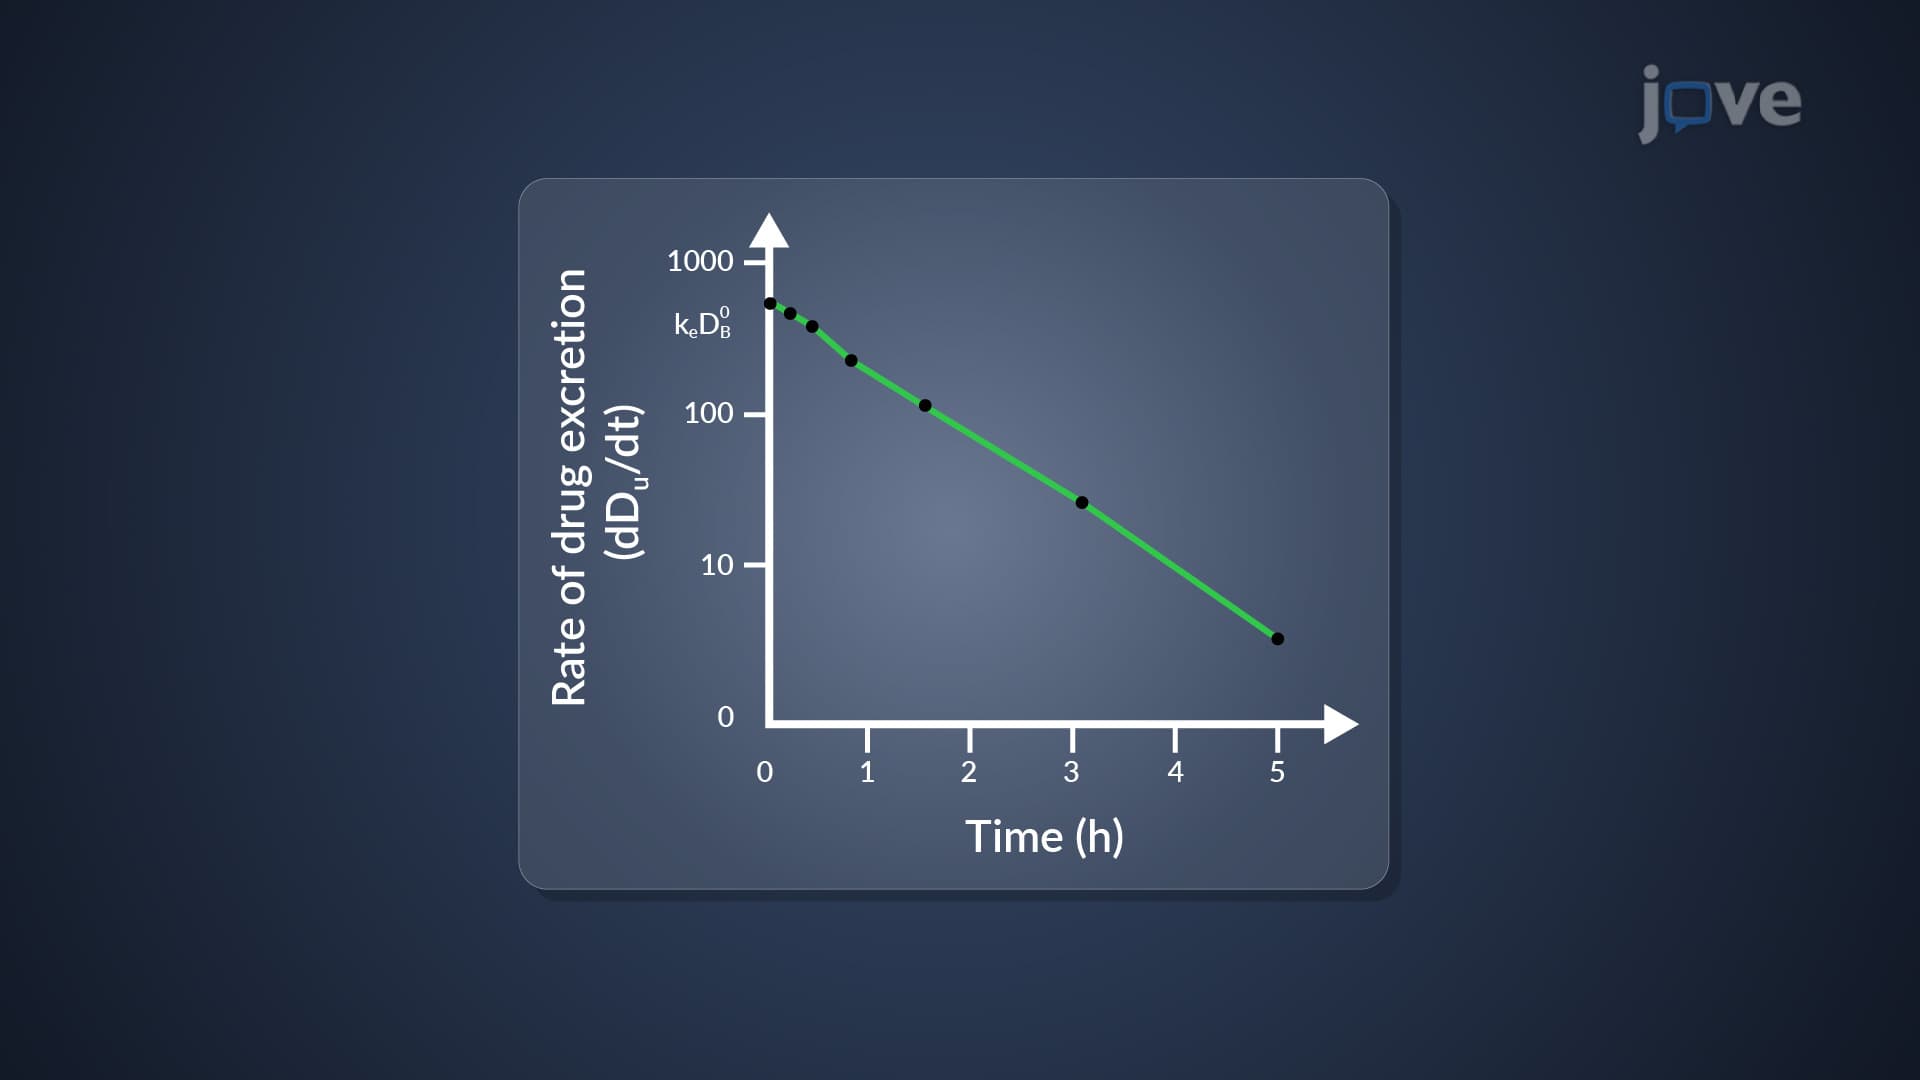
One-Compartment Open Model: Urinary Excretion Data and Determination of k
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:29
Drug Dosing: Infants and Children
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption