

Outcome of out-of-hospital postcountershock asystole and pulseless electrical activity versus primary asystole and
J T Niemann1, S J Stratton, B Cruz
1UCLA School of Medicine, the Department of Emergency Medicine, Harbor-UCLA Medical Center, Torrance, CA, USA.

Objective:
In the prehospital setting, countershock terminates ventricular fibrillation (VF) in about 80% of cases. However, countershock is most commonly followed by asystole or pulseless electrical activity (PEA). The consequences of such a countershock outcome have not been well studied. The purpose of this investigation was to compare the outcome of prehospital VF victims shocked into asystole or PEA with that of patients whose first documented rhythm was asystole or PEA (primary asystole or PEA).
Design:
Observational, retrospective study conducted over 5 yrs (1995-1999).
Setting:
A municipal hospital with a catchment area of >200,000.
Patients:
Consecutive adult patients with out-of-hospital nontraumatic cardiopulmonary arrest of cardiac origin. Patients found in VF who developed asystole or PEA after countershocks (group 1) and patients found in asystole or PEA (primary asystole or PEA) (group 2) were included if the reported downtime was <10 min.
Interventions:
None.
Measurements And Results:
Study end points included restoration of circulation (defined as a pulse for any duration), survival to hospital admission, and survival to hospital discharge. Ratios were determined, 95% confidence intervals were calculated, and observed differences were compared. For group 1 patients (n = 101), 61% of patients had a bystander-witnessed collapse and 34% received bystander cardiopulmonary resuscitation. For group 2 patients (n = 140), collapse was bystander witnessed in 71% and 45% received bystander cardiopulmonary resuscitation. These differences were not statistically significant. Restoration of circulation was significantly more frequent in group 2 than group 1 (42% vs. 16%, p <.001) as was survival to hospital admission (36% vs. 11%, p =.001). Survival to hospital discharge was greater in group 2 patients, but the difference failed to achieve statistical significance (10% vs. 3%, p =.062).
Conclusions:
Countershock of prolonged VF followed by a nonperfusing rhythm has a worse prognosis than primary asystole or PEA and may be related to myocardial electrical injury.
More Related Videos
 09:47
A Rat Model of Ventricular Fibrillation and Resuscitation by Conventional Closed-chest Technique
Published on: April 26, 2015
 10:55
A Piglet Perinatal Asphyxia Model to Study Cardiac Injury and Hemodynamics after Cardiac Arrest, Resuscitation, and the Return of Spontaneous Circulation
Published on: January 13, 2023
Related Concept Videos
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac muscle...
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:30
Cardiac Action Potential
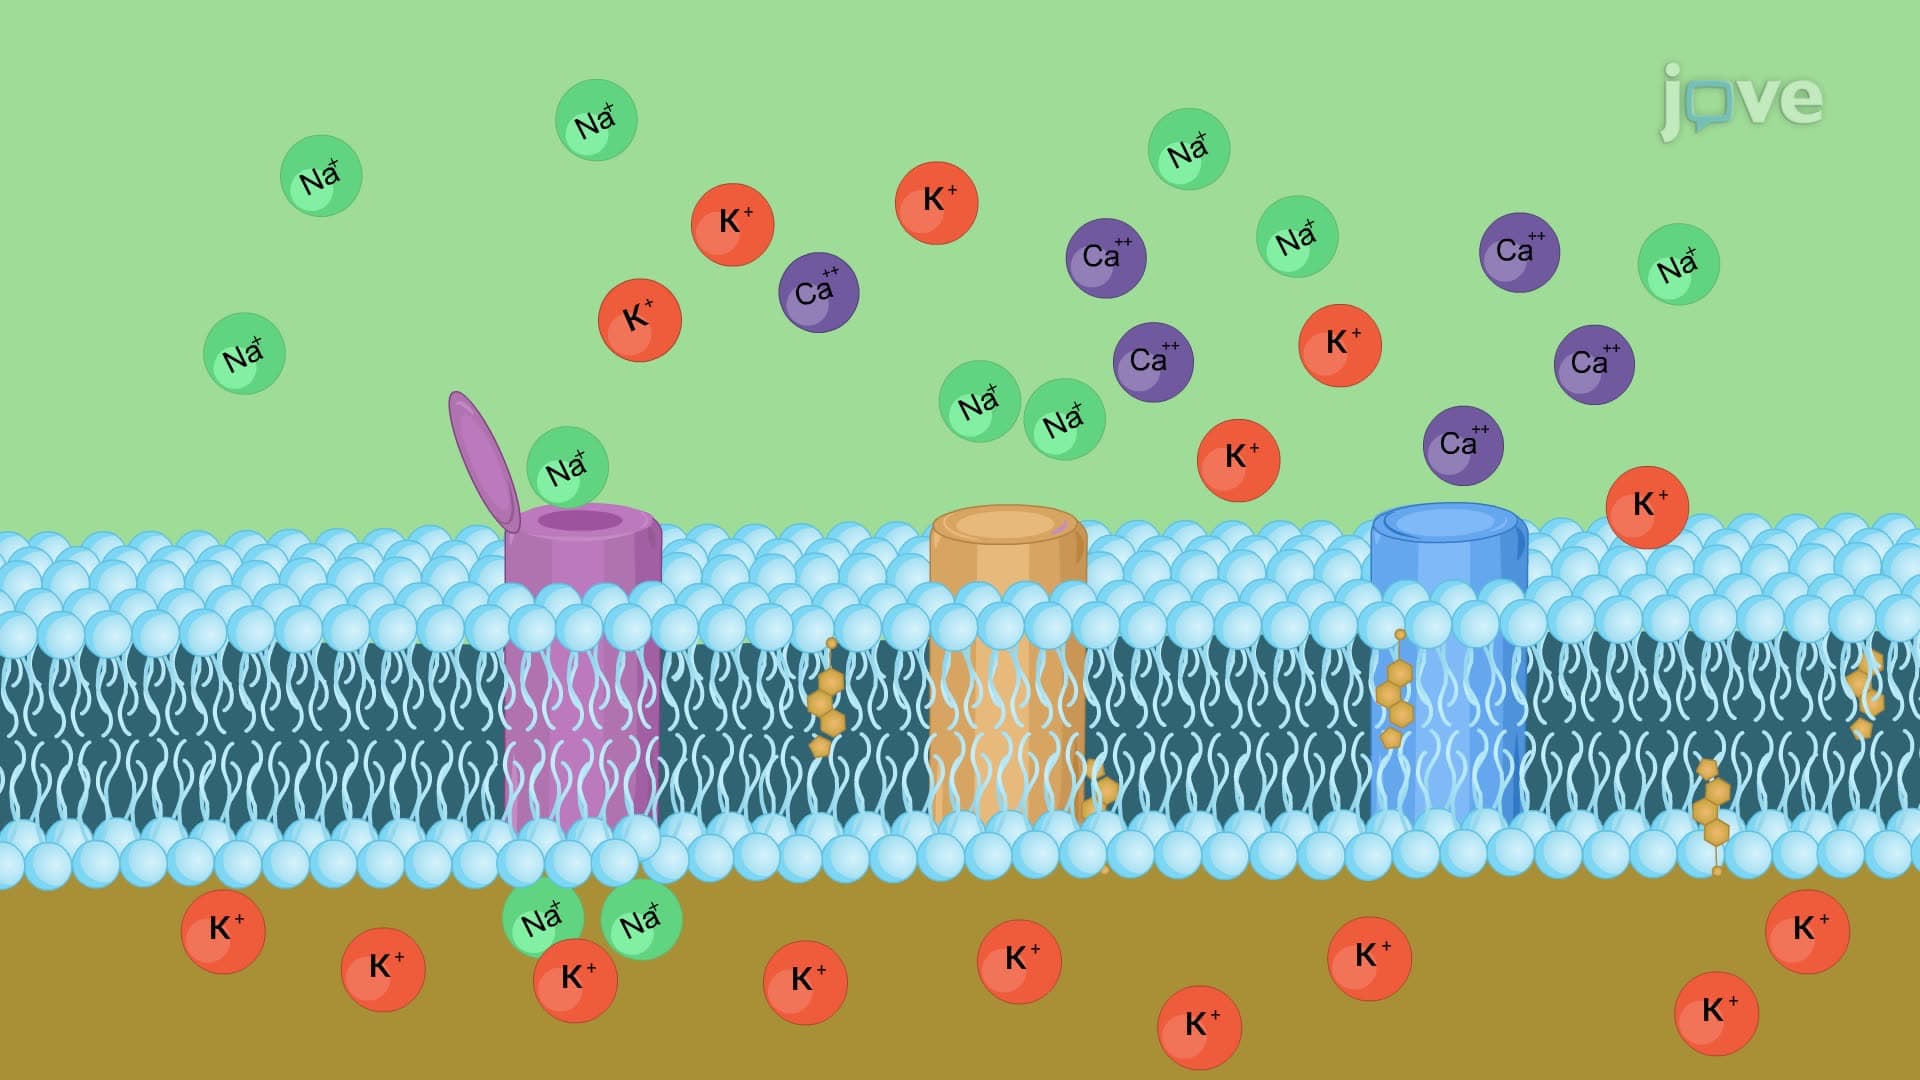
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management