Related Experiment Video
Updated: Oct 2, 2026
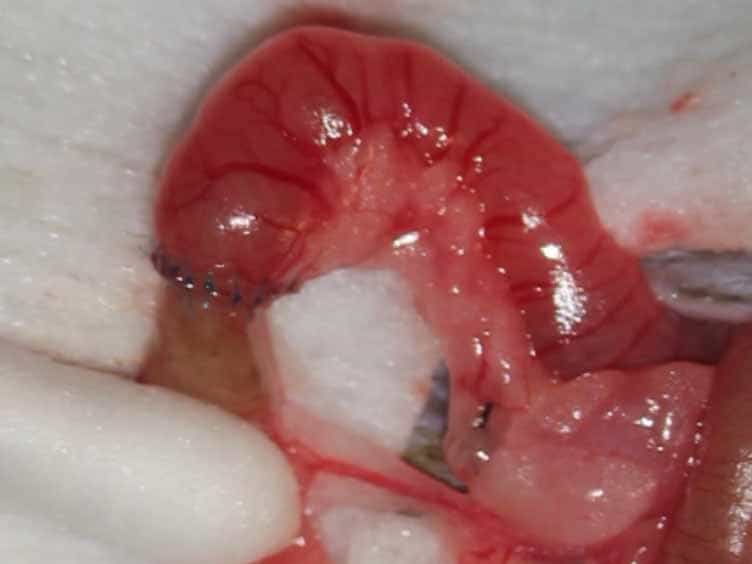
Murine Ileocolic Bowel Resection with Primary Anastomosis
Published on: October 29, 2014
Risk of small bowel obstruction after the ileal pouch-anal anastomosis
Anthony R MacLean1, Zane Cohen, Helen M MacRae
1IBD Research Unit, Department of Surgery, Mount Sinai Hospital and University of Toronto, Canada.

Objective:
To determine the incidence of small bowel obstruction (SBO), to identify risk factors for its development, and to determine the most common sites of adhesions causing SBO in patients undergoing ileal pouch-anal anastomosis (IPAA).
Methods:
All patients undergoing IPAA at Mount Sinai Hospital were included. Data were obtained from the institution's database, patient charts, and a mailed questionnaire. SBO was based on clinical, radiologic, and surgical findings. Early SBO was defined as a hospital stay greater than 10 or 14 days because of delayed bowel function, or need for reoperation or readmission for SBO within 30 days. All patients readmitted after 30 days with a discharge diagnosis of SBO were considered to have late SBO.
Results:
Between 1981 and 1999, 1,178 patients underwent IPAA (664 men, 514 women; mean age 40.7 years). A total of 351 episodes of SBO were documented in 272 (23%) patients during a mean follow-up of 8.7 years (mean 1.29 episodes/patient). Fifty-four patients had more than one SBO. One hundred fifty-four (44%) of the SBOs occurred in the first 30 days; 197 (56%) were late SBOs. The cumulative risk of SBO was 8.7% at 30 days, 18.1% at 1 year, 26.7% at 5 years, and 31.4% at 10 years. The need for surgery for SBO was 0.8% at 30 days, 2.7% at 1 year, 6.7% at 5 years, and 7.5% at 10 years. In patients requiring laparotomy, the obstruction was most commonly due to pelvic adhesions (32%), followed by adhesions at the ileostomy closure site (21%). A multivariate analysis showed that when only late SBOs were considered, performance of a diverting ileostomy and pouch reconstruction both led to a significantly higher risk of SBO.
Conclusions:
The risk of SBO after IPAA is high, although most do not require surgical intervention. Thus, strategies that reduce the risk of adhesions are warranted in this group of patients to improve patient outcome and decrease healthcare costs.

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:07
Intestinal Obstruction II: Pathophysiology
 01:29
Intestinal Obstruction I: Introduction
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by transmural...
 01:27
Diverticular Disease of the Colon