Related Experiment Video
Updated: Jun 27, 2026


Murine Appendectomy Model of Chronic Colitis Associated Colorectal Cancer by Precise Localization of Caecal Patch
Published on: August 24, 2019
Risk factors for ileoanal J pouch-related septic complications in ulcerative colitis and familial adenomatous
Udo A Heuschen1, Ulf Hinz, Erik H Allemeyer
1Department of Surgery, University of Heidelberg, Heidelberg, Germany. Udo_Heuschen@med.uni-heidelberg.de

Insights
Pouch-related septic complications (PRSC) after ileal pouch-anal anastomosis (IPAA) surgery are significant in ulcerative colitis (UC) and familial adenomatous polyposis (FAP) patients. Identifying risk factors like corticosteroid use in UC and anastomotic tension in FAP is crucial for tailored surgical strategies.
Area of Science:
- Gastroenterology
- Surgical Oncology
- Colorectal Surgery
Background:
- Ileal pouch-anal anastomosis (IPAA) is the preferred surgical treatment for ulcerative colitis (UC) and familial adenomatous polyposis (FAP).
- Pouch-related septic complications (PRSC) can compromise surgical outcomes in a significant number of patients undergoing IPAA.
Purpose of the Study:
- To investigate pre- and perioperative factors associated with pouch-related septic complications (PRSC).
- To identify patient subgroups at high risk for PRSC following IPAA in both UC and FAP cohorts.
Main Methods:
- A retrospective analysis of 706 patients (494 UC, 212 FAP) who underwent IPAA.
- Kaplan-Meier estimation was used to analyze PRSC rates over time.
- Patients were stratified by disease type (UC vs. FAP) and analyzed for various risk factors, including age, sex, surgeon experience, ileostomy use, prior colectomy, and anastomotic tension.
Main Results:
- Overall, 19.2% of patients experienced PRSC (23.4% in UC, 9.4% in FAP).
- For UC patients, risk factors for PRSC included younger age (<50 years), severe proctitis, low hemoglobin (<10 g/L), and corticosteroid use (especially >40 mg/day prednisolone equivalent).
- Anastomotic tension was a significant risk factor for PRSC in FAP patients.
Conclusions:
- PRSC are often late-onset complications requiring specific long-term follow-up.
- Distinct risk factors for PRSC exist for UC and FAP patients.
- Individualized surgical strategies should consider these identified risk factors to optimize patient outcomes.
Objective:
To analyze the association between pre- and perioperative factors and pouch-related septic complications (PRSC) in ulcerative colitis (UC) and in familial adenomatous polyposis (FAP) after ileal pouch-anal anastomosis (IPAA).
Summary Background Data:
For patients with UC and FAP, IPAA is the surgical therapy of choice, but in some patients the outcome is compromised by PRSC.
Methods:
A total of 706 consecutive patients (494 UC, 212 FAP) were assessed in a study aimed at identifying subgroups of patients who were at high risk for PRSC. The rate of PRSC was analyzed as a time-dependent function (Kaplan-Meier estimation). Patients with UC and FAP were stratified separately according to associated factors (age, sex, surgeon's experience, temporary ileostomy, colectomy before IPAA, anastomotic tension, and several factors specific for UC).
Results:
In all, 131 (19.2%) patients had PRSC (23.4% UC, 9.4% FAP). In patients with UC, the estimated 1-year PRSC rate was 15.6% and the estimated 3-year PRSC rate was 24.2%. In patients with FAP, the estimated 1-year and 3-year PRSC rates were 9.2%. The difference between the estimated rates of PRSC was significant (P <.001). In the univariate analysis, patients with UC younger than 50 years, with severe proctitis, with preoperative hemoglobin levels less than 10 g/L, or receiving corticoid medication had a significantly higher risk for PRSC (P =.039, P =.037, P =.047, P =.003, respectively). Multivariate analysis showed that patients with UC receiving a systemic prednisolone-equivalent corticoid medication of more than 40 mg/day had a significantly greater risk of developing pouch-related complications than patients with UC receiving 1 to 40 mg/day and patients with UC who were not receiving corticoid medication (RR: 3.78, 2.25, 1, respectively, P <.001). Patients with FAP proved to have a significantly higher risk for PRSC in the univariate and multivariate analyses if anastomotic tension had occurred (RR 3.60, P =.0086).
Conclusions:
Pouch-related septic complications occur as late complications and should therefore be considered in regular, specific long-term follow-up examinations. The authors identified significant risk factors for PRSC specific to patients with UC and FAP; these must be considered for each individual surgical strategy.


Related Concept Videos
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by transmural...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Inflammatory Bowel Disease I: Introduction
 01:20
Inflammatory Bowel Disease II: Ulcerative Colitis
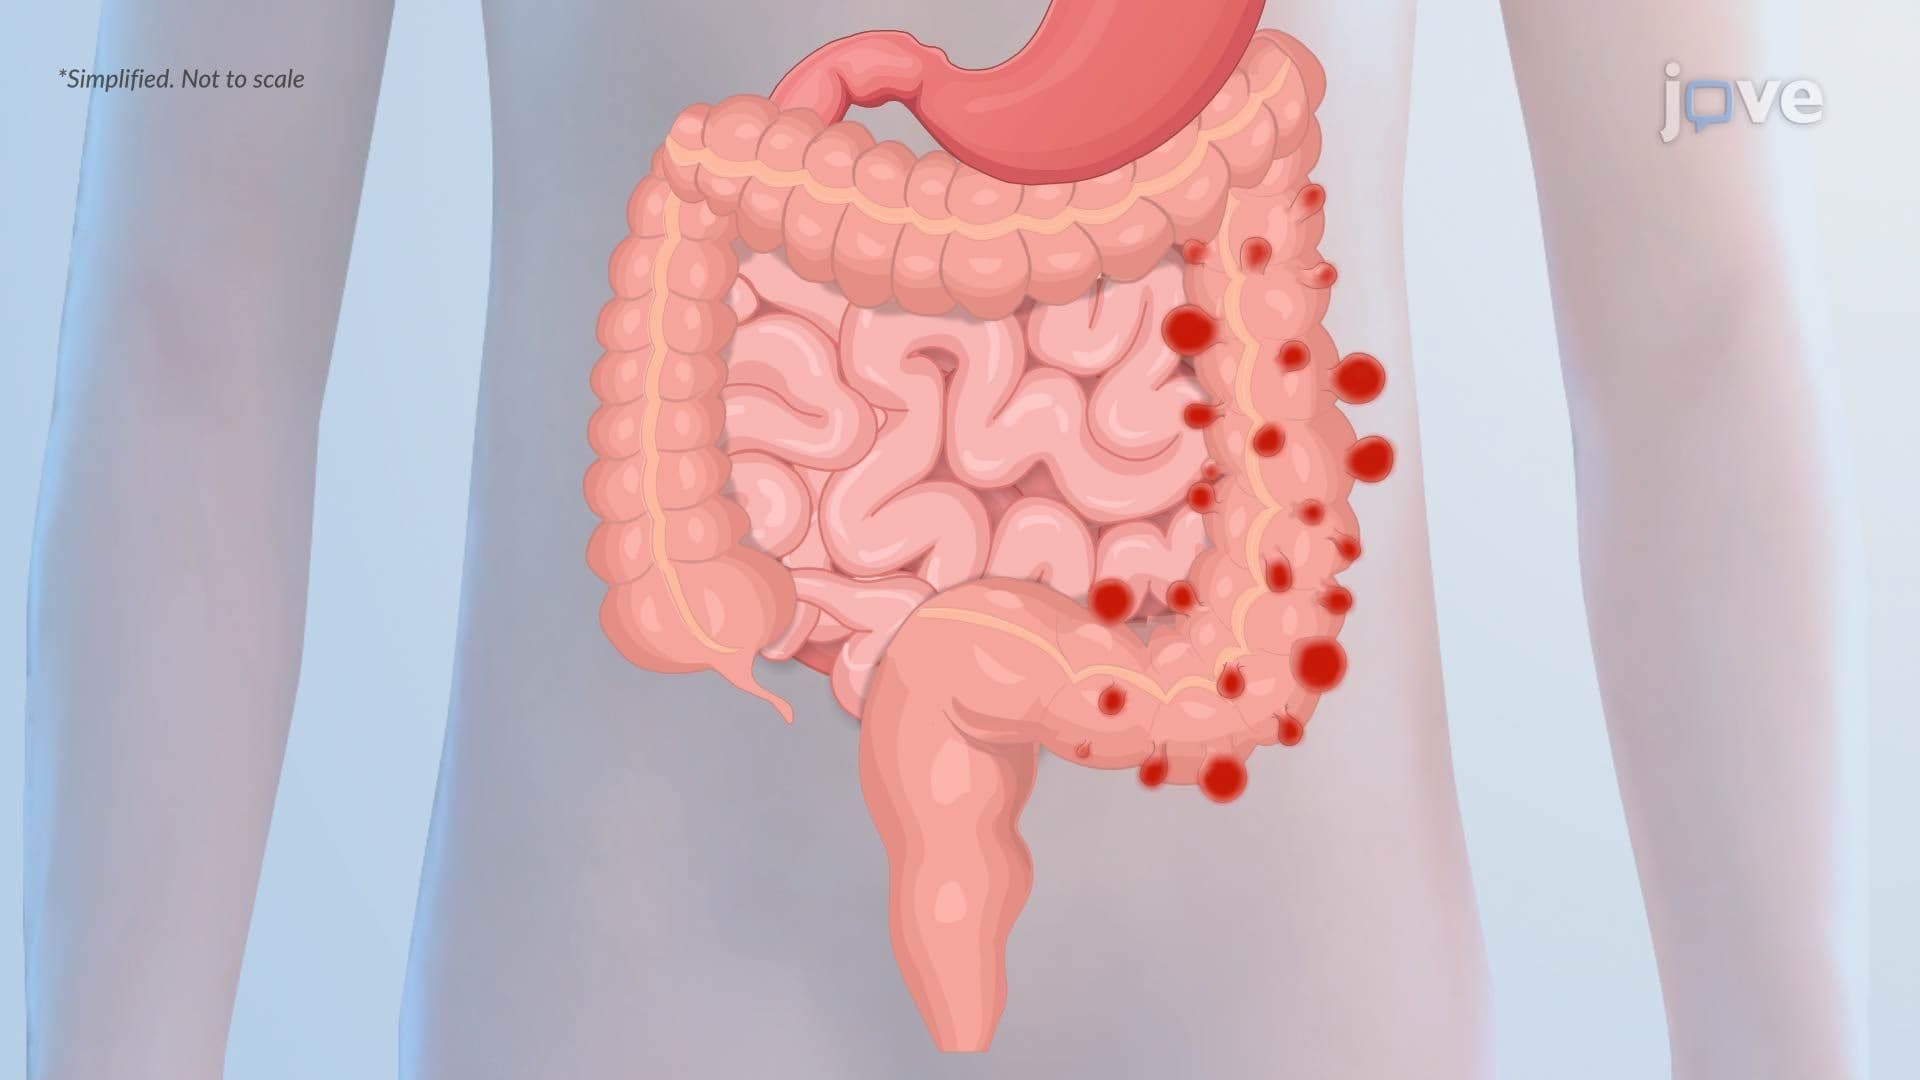 01:27
Diverticular Disease of the Colon