Related Experiment Video
Updated: Oct 2, 2026


Voltage-Dependent Potassium Current Recording on H9c2 Cardiomyocytes via the Whole-Cell Patch-Clamp Technique
Published on: November 11, 2022
[Hyperpolarized cardiac arrest with ATP-sensitive potassium channel opener on myocardial protection during CPB]

Objective:
To investigate the myocardial protective effects of pinacidil-induced hyperpolarized arrest and compare them with those induced with depolarized hyperkalemic arrest.
Methods:
18 dogs were equally divided into three groups. In the hypothermic hyperpolarization group (LH group), after aortic cross-clamping, a single dose of 4 degrees C pinacidil containing St. Thomas cardioplegic was infused through the aortic root. Temperature during CPB was kept between 26 - 28 degrees C and warmed to 37 degrees C before aortic declamping. Global ischemia lasted 60 min and then reperfusion started for 30 min. In the normothermic hyperpolarized group (WH group), the same procedure was set as in the LH group, except maintaining temperature of 35 - 37 degrees C for CPB and pinacidil solution. In the control group (group C), no pinacidil in St. Thomas solution was the only difference to the other 2 groups. Cardiac arrest and its recovery, the ultrastructure of the myocardium and hemodynamic during ischemia and after reperfusion were observed in the 3 groups.
Results:
(1) The percentages of normal mitochondria and glycogen were not changed significantly during ischemia and after reperfusion in the LH group, but declined markedly in the group C at ischemic 30, 60 min, and reperfusion for 20 min (P < 0.01). In the WH group, they were lower than those of the group LH, but higher than those of the group C before ischemia. (2) The recoveries of CO, SV, CI, LVSW, RVSW, MAP in the LH group were significantly better than those in the other two groups after reperfusion for 15 minutes and 30 minutes (P < 0.05 or 0.01). However, they were much better in the WH group than in the group C (P < 0.05 or 0.01). (3) The time from cardioplegic infusion to cardiac arrest was shorter in the group C and the group LH than in the group WH.
Conclusions:
Myocardial protection for global ischemia during CPB could be well achieved with hyperpolarized cardiac arrest induced by ATP-sensitive potassium channel opener, pinacidil, especially in the hypothermic state. The protection is weaker in normothermia but is still stronger than that with traditional depolarized arrest.
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:30
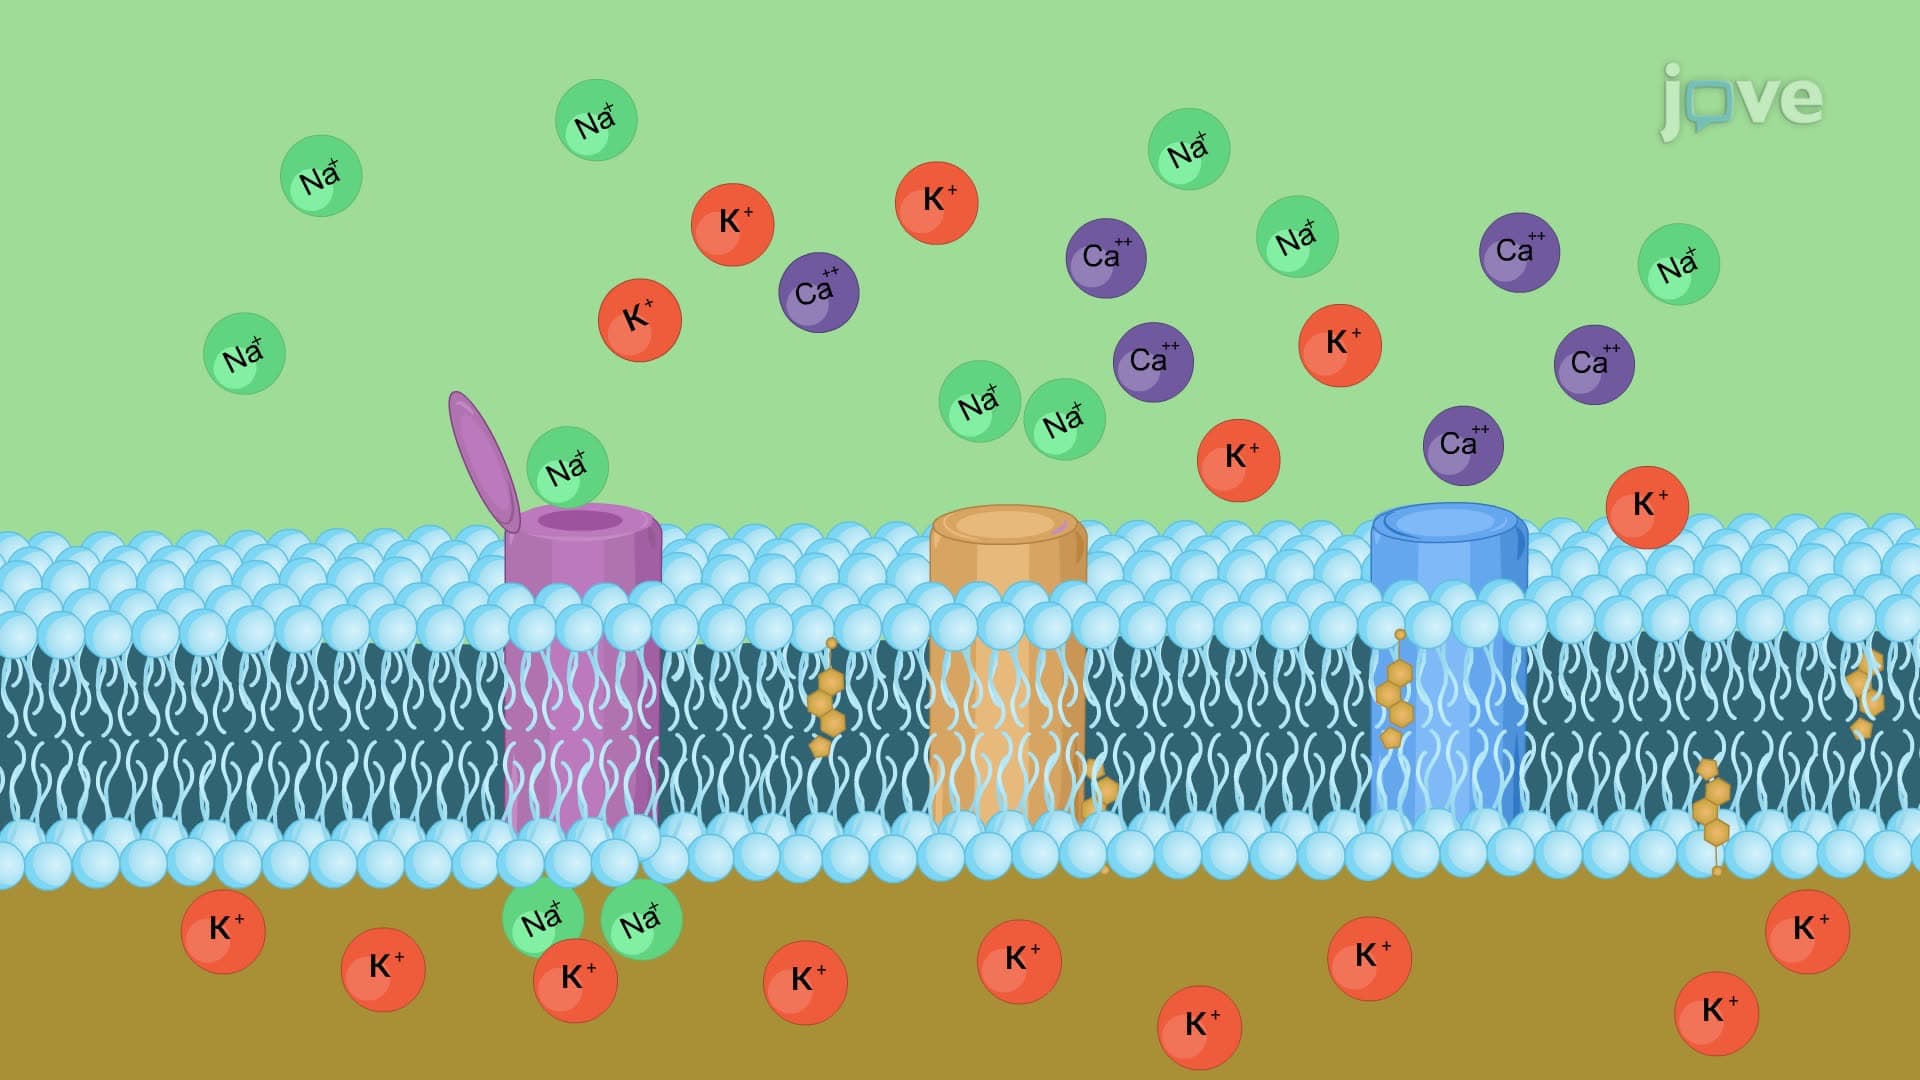
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...