Related Experiment Video
Updated: Jul 18, 2026
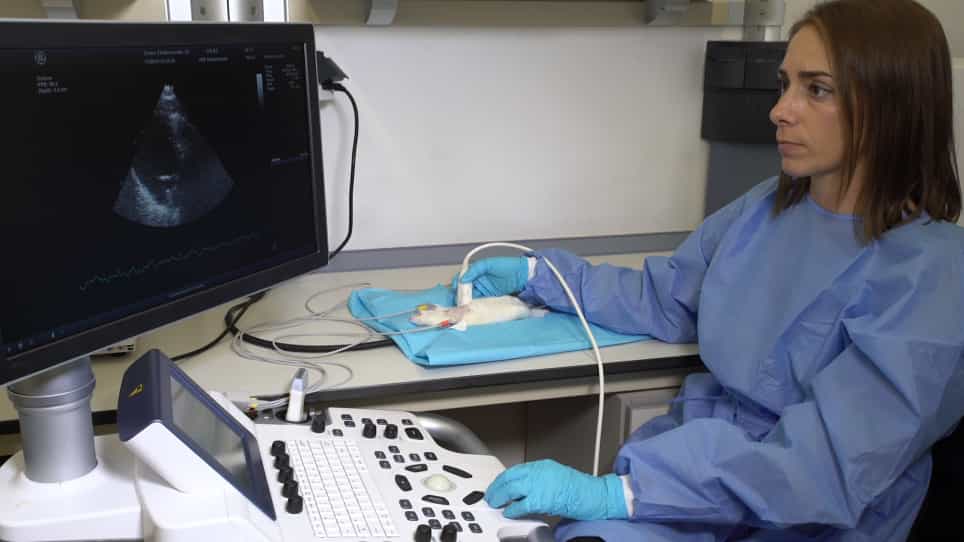
Echocardiographic Assessment of Cardiac Anatomy and Function in Adult Rats
Published on: December 13, 2019
Right ventricular myocardial diastolic dysfunction in different kinds of cardiac hypertrophy: analysis by pulsed
M Galderisi1, S Severino, P Caso
1Chair of Emergency Medicine, Department of Clinical and Experimental Medicine, University Federico II of Naples, Italy. mgalderi@unina.it

Insights
Right ventricular (RV) dysfunction is more pronounced in hypertrophic cardiomyopathy (HCM) than in hypertensive left ventricular hypertrophy (LVH). Impaired RV relaxation is linked to increased septal and RV wall thickness in HCM patients.
Area of Science:
- Cardiology
- Echocardiography
- Cardiac Physiology
Background:
- Right ventricular (RV) involvement is known in hypertrophic cardiomyopathy (HCM) and hypertensive left ventricular hypertrophy (LVH).
- RV myocardial dysfunction in these conditions is not well understood.
- This study compares RV dysfunction in HCM and LVH using Doppler tissue imaging (DTI).
Purpose of the Study:
- To compare right ventricular (RV) myocardial dysfunction in hypertrophic cardiomyopathy (HCM) and hypertensive left ventricular hypertrophy (LVH).
- To assess RV and left ventricular (LV) diastolic function using Doppler tissue imaging (DTI).
- To differentiate the extent of RV dysfunction in various cardiac hypertrophy types.
Main Methods:
- Doppler echocardiography and pulsed DTI were performed on 30 controls, 20 with LVH, and 23 with HCM.
- Measurements included LV lateral mitral annulus and RV lateral tricuspid annulus DTI.
- Analysis focused on global and regional diastolic function, comparing HCM, LVH, and control groups.
Main Results:
- HCM patients exhibited higher blood pressure, septal thickness, and LV mass than LVH and controls.
- RV diastolic function and myocardial relaxation were significantly more impaired in HCM than in LVH.
- RV myocardial relaxation time correlated positively with septal and RV wall thickness in the overall population.
Conclusions:
- RV myocardial relaxation impairment is significantly greater in HCM compared to LVH.
- The degree of RV dysfunction is independently associated with septal and RV wall thickness.
- Pulsed DTI is valuable for distinguishing RV myocardial dysfunction severity in different cardiac hypertrophy conditions.
Background:
Right ventricular (RV) chamber involvement has been demonstrated in hypertrophic cardiomyopathy (HCM) as well as in hypertensive left ventricular hypertrophy (LVH) but little is known about RV myocardial dysfunction occurring in these two pathologies. The aim of this study was to compare Doppler tissue imaging (DTI) of the right ventricle in HCM and LVH in relation to DTI of the left ventricle and Doppler standard of the RV and left ventricular (LV) inflow.
Methods:
Thirty controls, 20 hypertensives with LVH, and 23 patients with HCM involving the interventricular septum underwent Doppler echocardiography and pulsed DTI of the LV lateral mitral annulus and the RV lateral tricuspid annulus.
Results:
Patients with HCM had a higher blood pressure, septal thickness and LV mass in comparison with the other two groups. The RV wall thickness did not differ between HCM and LVH. The fractional shortening, but not the tricuspid annular plane excursion, was higher in HCM. After adjusting for the mean blood pressure, the Doppler-derived global LV and RV diastolic functions were more impaired in HCM than in LVH. Also the majority of DTI LV and RV diastolic measurements were altered more in HCM. At the RV tricuspid annulus, myocardial diastolic indexes were impaired in HCM and LVH in comparison with controls but the deceleration and relaxation times distinguished also HCM and LVH, being much longer in HCM (p < 0.0001). In the overall population, the RV myocardial relaxation time was positively related to the septal wall thickness and the RV wall thickness, even after adjusting for age, heart rate, diastolic blood pressure, fractional shortening and DTI mitral relaxation time.
Conclusions:
The impairment of RV myocardial relaxation is much more evident in HCM than in LVH, its degree being independently associated with the extent of both the septal and RV wall thickness. Pulsed DTI may be useful to distinguish the extent of RV myocardial dysfunction in different types of cardiac hypertrophy.
More Related Videos
 07:38
Comprehensive Echocardiographic Assessment of Right Ventricle Function in a Rat Model of Pulmonary Arterial Hypertension
Published on: January 20, 2023
 08:57
Pulsed Wave Doppler Assessment of Diastolic Dysfunction in the ZSF-1 Rat Model of Pulmonary Hypertension Due to Left Heart Disease
Published on: May 22, 2026
Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy