Related Experiment Video
Updated: Aug 5, 2026


In vivo Imaging Method to Distinguish Acute and Chronic Inflammation
Published on: August 16, 2013
The levels of neutrophils oxidative burst in rheumatic disorders
C Stăvaru1, A Dolganiuc, D Baltaru
1Cantacuzino Institute, Bucharest, Romania.

Abstract:
We investigated the participation of the polymorphonuclear leukocytes (PMNs) as mediators of tissue destruction in 2 variants of rheumatic disorders that affect primarily the joints: the rheumatoid arthritis (RA) and the osteoarthritis (OA). We noted significant differences in the number of PMNs present at the joint level, which was low in OA and high in RA. The unstimulated and in vitro stimulated with opsonized zymozan (OZ) or ConA PMNs from the peripheral blood of these two groups of patients released a normal level of oxygen free radicals (OFR). On the contrary, the neutrophils isolated from the synovial fluid (SF) of RA patients showed a distinct feature: the unstimulated cells released high amounts of OFR, while those in vitro stimulated with OZ or ConA presented a low level of respiratory burst. In OA both in vitro unstimulated and stimulated with OZ or ConA neutrophils isolated from the SF had diminished values of OFR released. We assume that the chemiluminescence assay could detect distinct differences of the PMNs implications in RA and OA injuries and may be a laboratory test in the differential diagnosis of these rheumatic disorders.
Insights
Polymorphonuclear leukocytes (PMNs) play a distinct role in rheumatoid arthritis (RA) versus osteoarthritis (OA) joint damage. Their oxygen free radical release differs significantly in synovial fluid, suggesting a diagnostic potential for PMNs in differentiating these rheumatic conditions.
Area of Science:
- Rheumatology
- Immunology
- Cell Biology
Background:
- Rheumatoid arthritis (RA) and osteoarthritis (OA) are common joint diseases with distinct pathologies.
- Polymorphonuclear leukocytes (PMNs) are implicated in inflammatory tissue destruction.
- Understanding PMN behavior is crucial for differentiating RA and OA.
Purpose of the Study:
- To investigate the role of PMNs in tissue destruction in RA and OA.
- To compare PMN activity, specifically oxygen free radical (OFR) release, in patients with RA and OA.
- To evaluate the potential of chemiluminescence assays for differential diagnosis.
Main Methods:
- Analysis of PMN counts in joint tissues of RA and OA patients.
- Measurement of OFR release from peripheral blood PMNs (unstimulated and stimulated with opsonized zymozan or ConA).
- Assessment of OFR release from synovial fluid (SF) neutrophils in RA and OA patients.
Main Results:
- Higher PMN numbers were observed in RA joints compared to OA joints.
- Peripheral blood PMNs from both groups released normal OFR levels.
- SF neutrophils from RA patients showed high OFR release when unstimulated but low release when stimulated.
- SF neutrophils from OA patients exhibited diminished OFR release in both unstimulated and stimulated states.
Conclusions:
- PMN activity, particularly OFR release from SF neutrophils, differs significantly between RA and OA.
- Chemiluminescence assays can detect these distinct PMN differences.
- This assay may serve as a valuable laboratory test for the differential diagnosis of RA and OA.


Related Concept Videos
 01:38
Inflammation
 01:23
Rheumatic Heart Disease I: Introduction
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:26
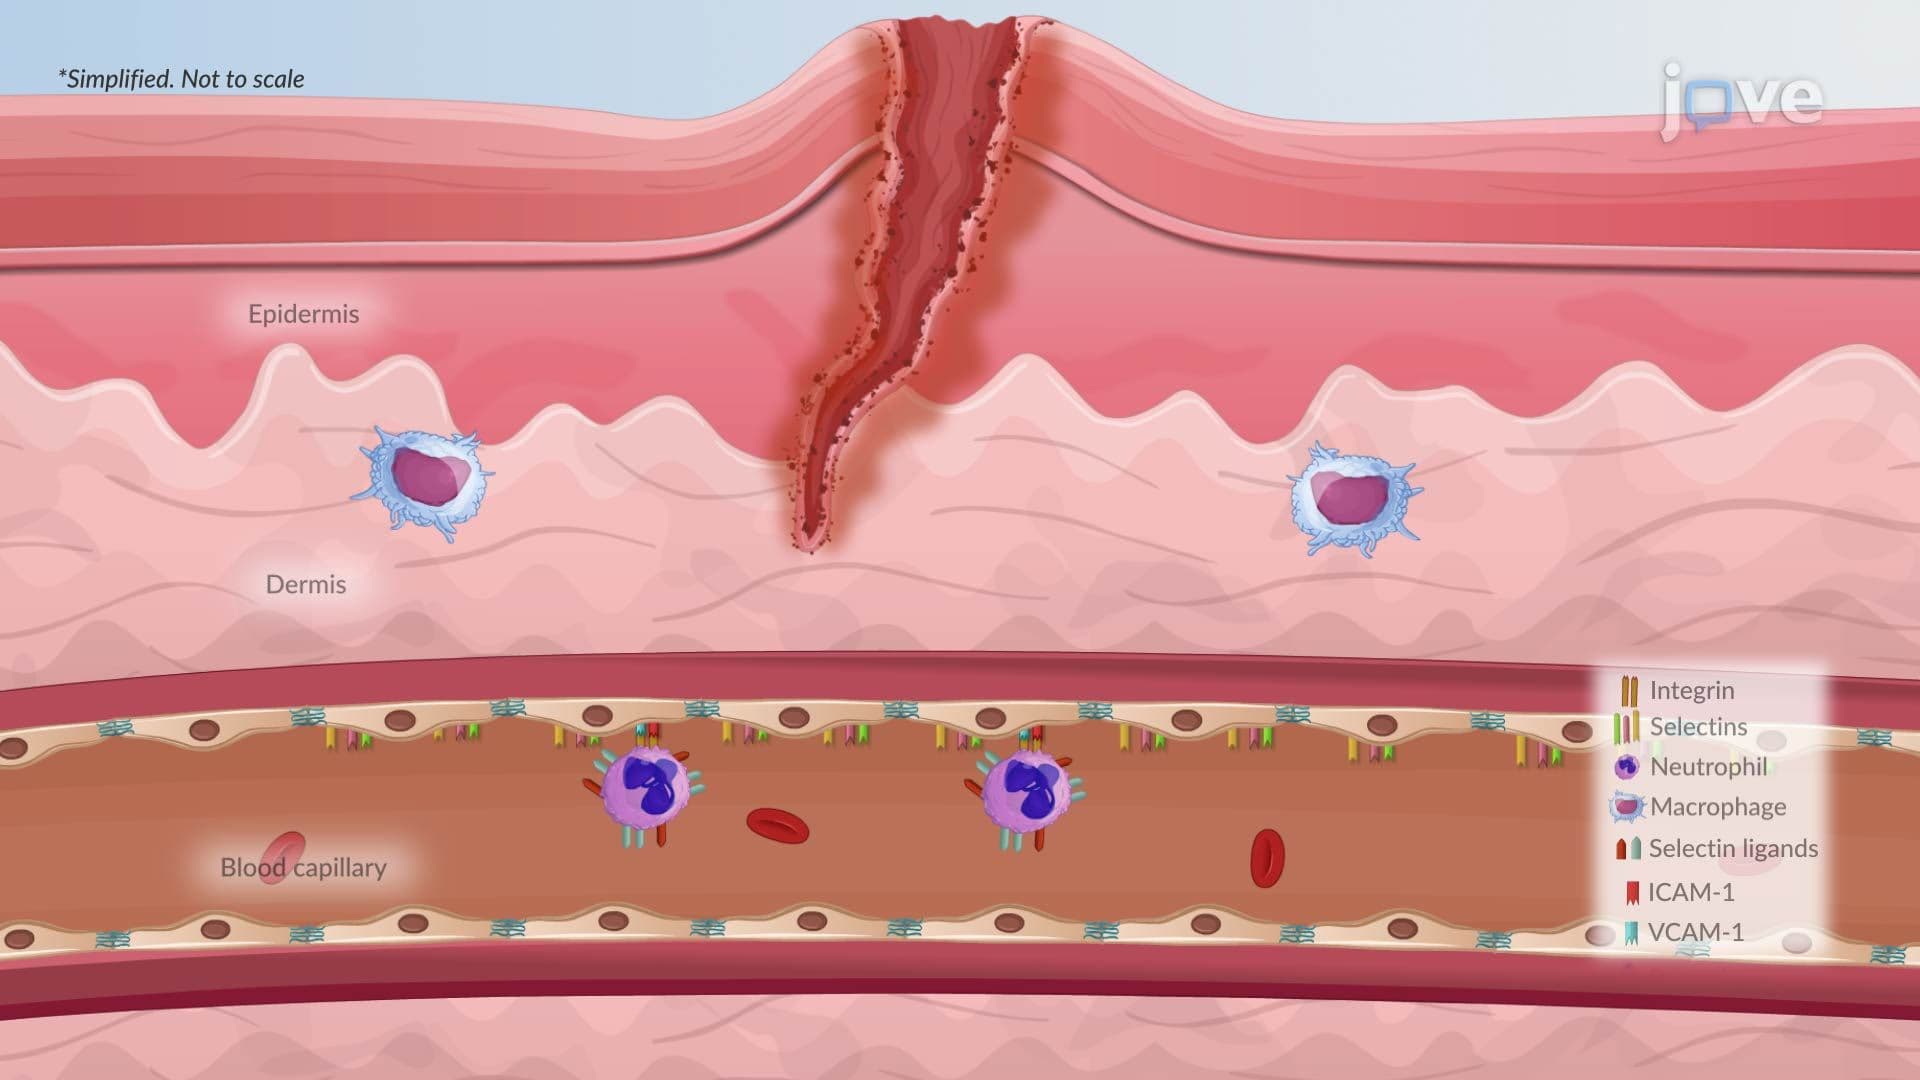
Acute Inflammation II: Cellular Phase
 01:12
Chronic Inflammation: Introduction