Related Experiment Video
Updated: Oct 2, 2026
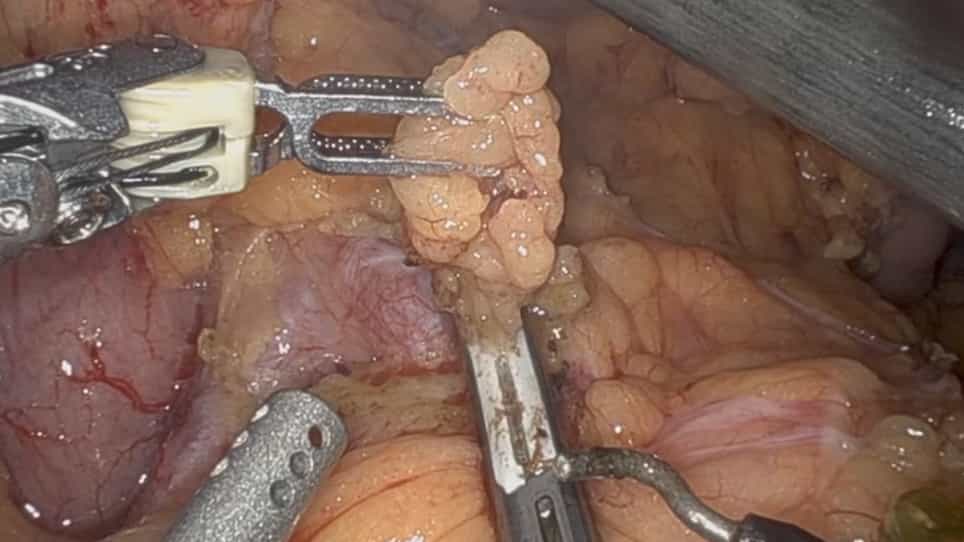

Robot Assisted Distal Pancreatectomy with Celiac Axis Resection (DP-CAR) for Pancreatic Cancer: Surgical Planning and Technique
Published on: August 14, 2021
Localized adenocarcinoma of the pancreas: the rationale for preoperative chemoradiation
Jeffrey D Wayne1, Eddie K Abdalla, Robert A Wolff
1The Department of Surgical Oncology, The University of Texas M. D. Anderson Cancer Center, Houston, Texas 77030, USA.

Abstract:
Pancreatic adenocarcinoma is the fifth leading cause of cancer-related death in the U.S. In spite of advancements in surgical treatment, nearly 80% of patients thought to have localized pancreatic cancer die of recurrent or metastatic disease when treated with surgery alone. Therefore, efforts to alter the patterns of recurrence and improve survival for patients with pancreatic cancer currently focus on the delivery of systemic therapy and irradiation before or after surgery. Postoperative adjuvant therapy appears to improve median survival. However, more than one-fourth of patients do not complete planned adjuvant therapy due to surgical complications or a delay in postoperative recovery of performance status. Utilizing a preoperative (neoadjuvant) approach, overall treatment time is reduced, a greater proportion of patients receive all components of therapy, and patients with rapidly progressive disease are spared the side effects of surgery as metastatic disease may be found at restaging following chemoradiation (prior to surgery). This paper examines the factors pertinent to clinical trial design for resectable pancreatic cancer, and carefully reviews the existing data supporting adjuvant and neoadjuvant therapy for potentially resectable disease.
