Related Experiment Video
Updated: Oct 2, 2026


The 4-vessel Sampling Approach to Integrative Studies of Human Placental Physiology In Vivo
Published on: August 2, 2017
Placental nutrient transfer capacity and fetal growth
P Haggarty1, S Allstaff, G Hoad
1Rowett Research Institute, Aberdeen, AB2 9SB, UK. p.haggarty@abdn.ac.uk

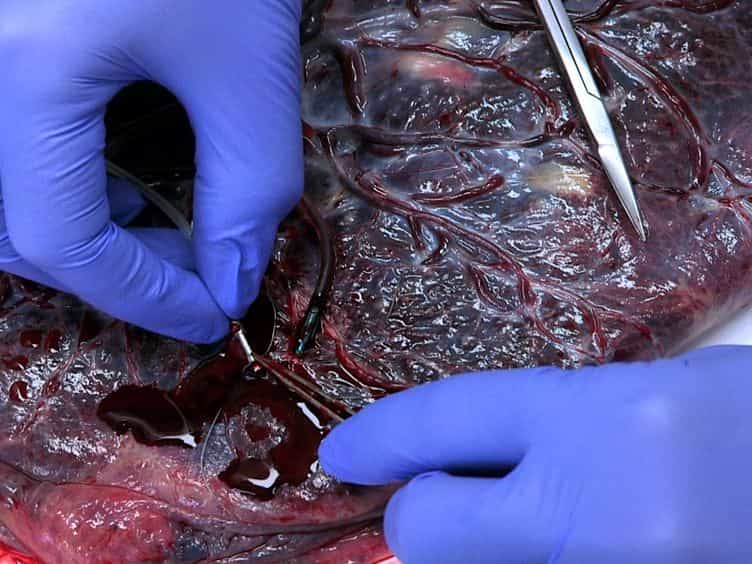
The objective of this study was to determine whether the ability of the human placenta to transfer glucose and fatty acids is related to normal fetal growth. The intrinsic nutrient transport capacity of the placenta was measured under standardized conditions during in vitro perfusion of 30 human term placentas and related to birth weight (range 2640-4640g), birth weight centile (8th-99th), ponderal index (2.43-3.69), placental weight (418-1030g) and placental:fetal weight (0.14-0.31). There was no statistically significant change in the rate of nutrient transfer per placenta or per kg fetal weight, with birth weight, birth weight centile, ponderal index, placental weight and placental:fetal weight. There was a weak but significant relationship (P=0.020, r(2)=9 per cent) between the ratio of glucose to fatty acid transport and birth weight centile, largely due to the high ratio found in the lowest birth weight quartile where the babies are thinnest. This study provides no evidence that placental nutrient transport capacity limits fetal growth across a wide range of birth weights in normal pregnancies. It is proposed that the fetus itself may regulate placental nutrient transport in vivo via the fetal cardiac output and the rate of fetal nutrient utilization.
The objective of this study was to determine whether the ability of the human placenta to transfer glucose and fatty acids is related to normal fetal growth. The intrinsic nutrient transport capacity of the placenta was measured under standardized conditions during in vitro perfusion of 30 human term placentas and related to birth weight (range 2640-4640g), birth weight centile (8th-99th), ponderal index (2.43-3.69), placental weight (418-1030g) and placental:fetal weight (0.14-0.31). There was no statistically significant change in the rate of nutrient transfer per placenta or per kg fetal weight, with birth weight, birth weight centile, ponderal index, placental weight and placental:fetal weight. There was a weak but significant relationship (P=0.020, r(2)=9 per cent) between the ratio of glucose to fatty acid transport and birth weight centile, largely due to the high ratio found in the lowest birth weight quartile where the babies are thinnest. This study provides no evidence that placental nutrient transport capacity limits fetal growth across a wide range of birth weights in normal pregnancies. It is proposed that the fetus itself may regulate placental nutrient transport in vivo via the fetal cardiac output and the rate of fetal nutrient utilization.
More Related Videos

Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:07
Teratogenicity
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:28
Development of the Oral Microbiota