Related Experiment Video
Updated: Oct 2, 2026

Sodium Taurocholate Induced Severe Acute Pancreatitis in C57BL/6 Mice
Published on: June 28, 2021
Urea synthesis in patients with chronic pancreatitis: relation to glucagon secretion and dietary protein intake
O Hamberg1, V Andersen, J Sonne
1Department of Medicine M, Glostrup University Hospital, Copenhagen, Denmark.

Background & Aims:
Up-regulation of urea synthesis by amino acids and dietary protein intake may be impaired in patients with chronic pancreatitis (CP) due to the reduced glucagon secretion. Conversely, urea synthesis may be increased as a result of the chronic inflammation. The aims of the study were to determine urea synthesis kinetics in CP patients in relation to glucagon secretion (study I) and during an increase in protein intake (study II).
Methods:
In study I, urea synthesis rate, calculated as urinary excretion rate corrected for accumulation in total body water and intestinal loss, was measured during infusion of alanine in 7 CP patients and 5 control subjects on spontaneous protein intake. The functional hepatic nitrogen clearance (FHNC), i.e. urea synthesis expressed independent of changes in plasma amino acid concentration, was calculated as the slope of the linear relation between urea synthesis rate and plasma alpha -amino nitrogen concentration. In study II, 6 of the patients of study I had urea synthesis and FHNC determined before and after a period of 14 days of supplementation with a protein-enriched liquid (dietary sequence randomized).
Results:
Study I: Alanine infusion increased urea synthesis rate by a factor of 10 in the control subjects, and by a factor of 5 in the CP patients (P<0.01). FHNC was 31.9+/-2.4 l/h in the control subjects and 16.5+/-2.0 l/h (P<0.05) in the CP patients. The glucagon response to alanine infusion (AUC) was reduced by 75 % in the CP patients. The reduction in FHNC paralleled the reduced glucagon response (r(2)=0.55, P<0.01). Study II: The spontaneous protein intake was 0.75+/-0.14 g/(kg x day) and increased during the high protein period to 1.77+/-0.12 g/(kg x day). This increased alanine stimulated urea synthesis by a factor of 1.3 (P<0.05), FHNC from 13.5+/-2.6 l/h to 19.4+/-3.1 l/h (P<0.01), and the glucagon response to alanine infusion (AUC) by a factor of 1.8 (P<0.05).
Conclusions:
Urea synthesis rate and FHNC are markedly reduced in CP patients. This is associated with, and probably a result of, impaired glucagon secretion, and predicts a lower than normal postprandial hepatic loss of amino nitrogen. An increase in dietary protein intake increases alanine stimulated urea synthesis and FHNC by a mechanism that involves an increase in glucagon. This indicates that the low FHNC during spontaneous protein intake included an adaptation to the low protein intake, effectuated by a further decrease in glucagon secretion.

Related Concept Videos
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:24
Chronic Pancreatitis I: Introduction
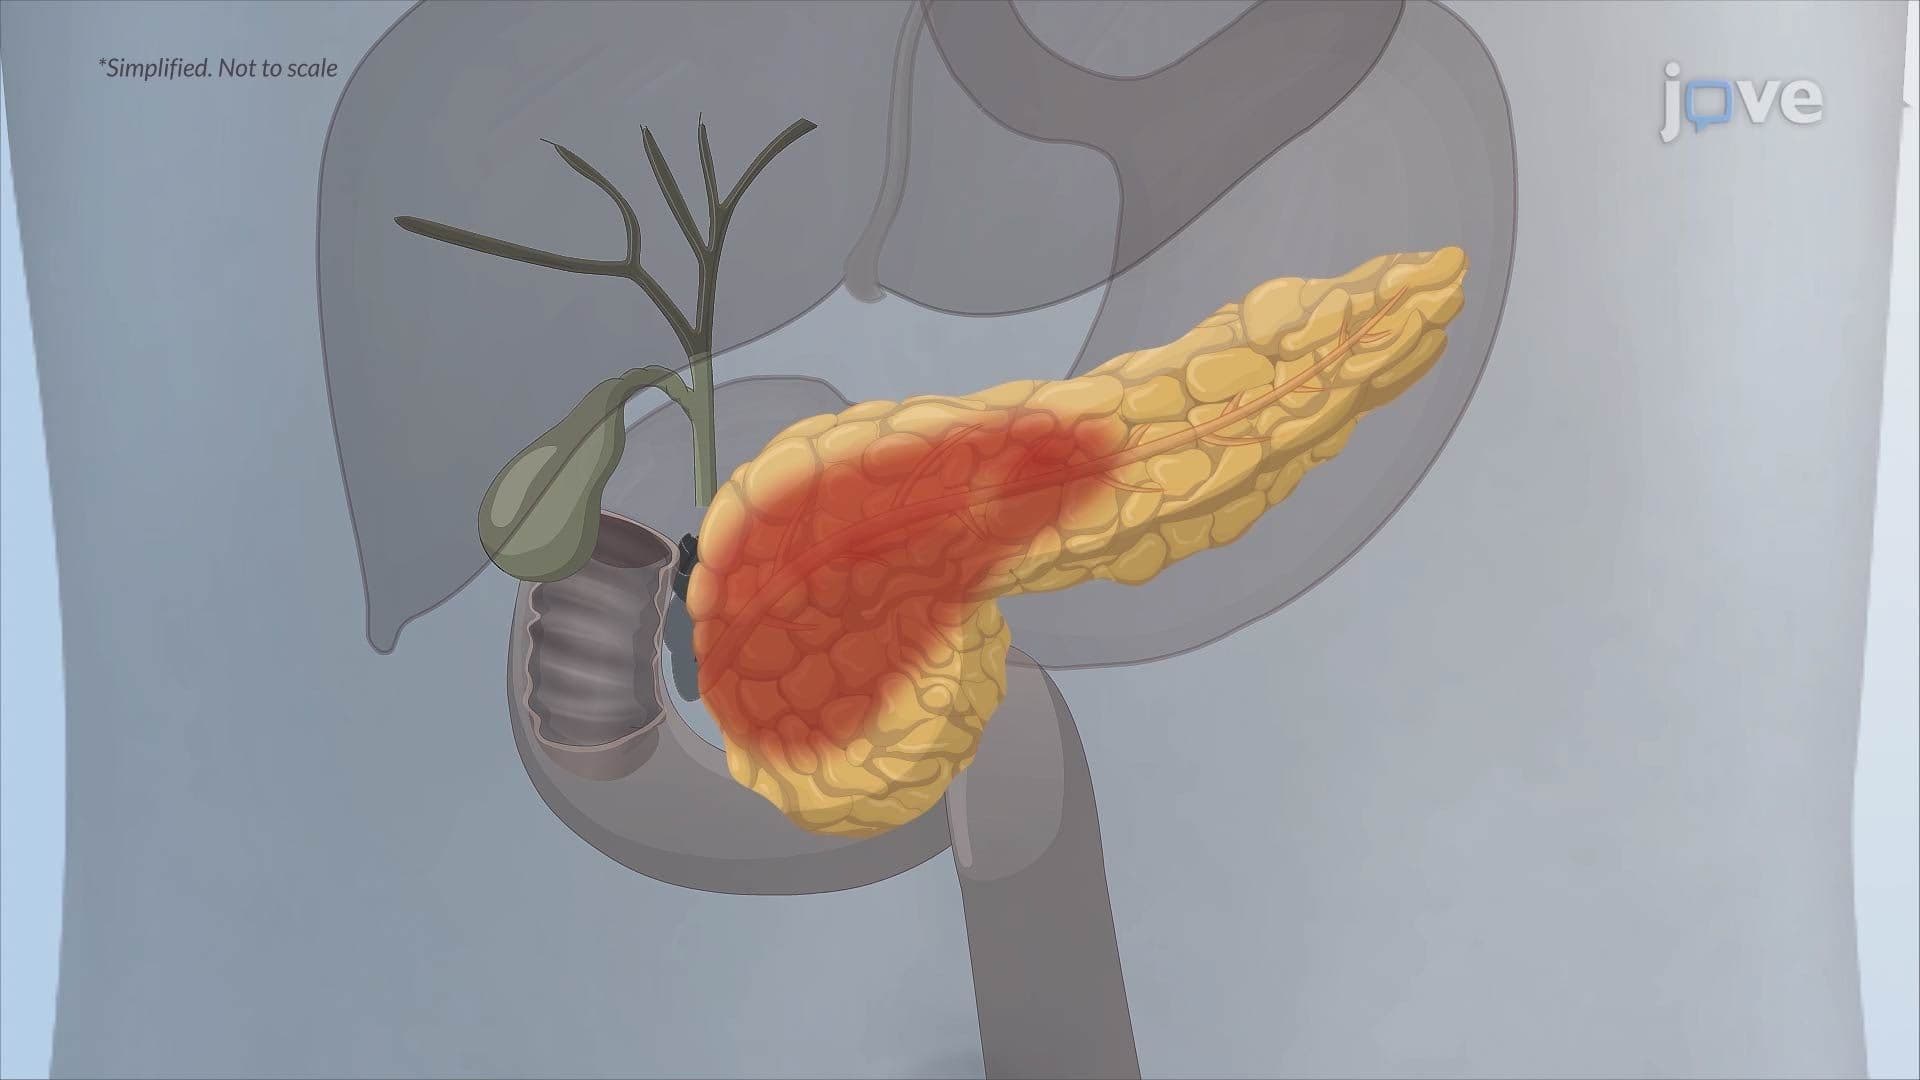
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Chronic Pancreatitis I: Introduction
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: