Related Experiment Videos
The significance of intraoperative pleural effusion during surgery for bronchogenic carcinoma
Enrico Ruffini1, Ottavio Rena, Massimo Bongiovanni
1Department of Thoracic Surgery, University of Torino, 3, Via Genova 10126, Torino, Italy. enrico.ruffini@unito.it

Objectives:
To analyze patients submitted to thoracotomy for lung carcinoma presenting with an intraoperative pleural effusion (PE).
Methods:
From 1993 to 1999, 1279 patients received thoracotomy with curative intent for primary lung carcinoma. Intraoperatively, 52 patients (4%) presented a PE >100ml which was not diagnosed preoperatively. Of these, seven patients had received preoperative transthoracic fine-needle biopsy FNB and were excluded from the analysis. In the remaining 45 patients pleural fluid cytology was undertaken. In patients with cytology-negative PE, clinico-pathologic characteristics including intratumoral vascular invasion, intratumoral perineural invasion, peritumoral lymphocytic infiltrate, visceral, parietal and mediastinal pleural involvement, pTNM and survival were analyzed and compared with our total population of lung cancer patients operated on during the same period.
Results:
The mean amount of collected fluid was 210ml (100-450ml). Of the 45 patients with intraoperative PE, 16 (35%) received exploratory thoracotomy because of pleural carcinosis or major involvement of mediastinal structures; eight (18%) received resection of the tumor, although the cytologic examination of the pleural fluid eventually resulted positive for neoplastic cells. Median survival for the two groups was 6 and 9 months, respectively. Twenty-one patients (47%) received resection of the tumor with a cytology-negative pleural fluid. In this group, analysis of clinico-pathologic characteristics revealed that squamous cell type and mediastinal pleural involvement were significantly associated with the presence of intraoperative PE (P=0.01 and P=0.05, respectively); 3- and 5-year survivals of this group were similar to those observed in our total population of resected lung cancer patients (68 and 56% vs. 54 and 42%, P=0.27).
Conclusions:
The presence of a PE at thoracotomy during surgery for lung carcinoma is an infrequent occurrence. In more than 50% of the cases cytology is positive and prognosis is poor. In the remaining cases, however, cytology is negative and the PE should be considered as reactive; in these patients a curative resection can be accomplished with an anticipated chance of long-term survival.
Related Concept Videos
 01:28
Pleural Effusion II: Symptoms and Management
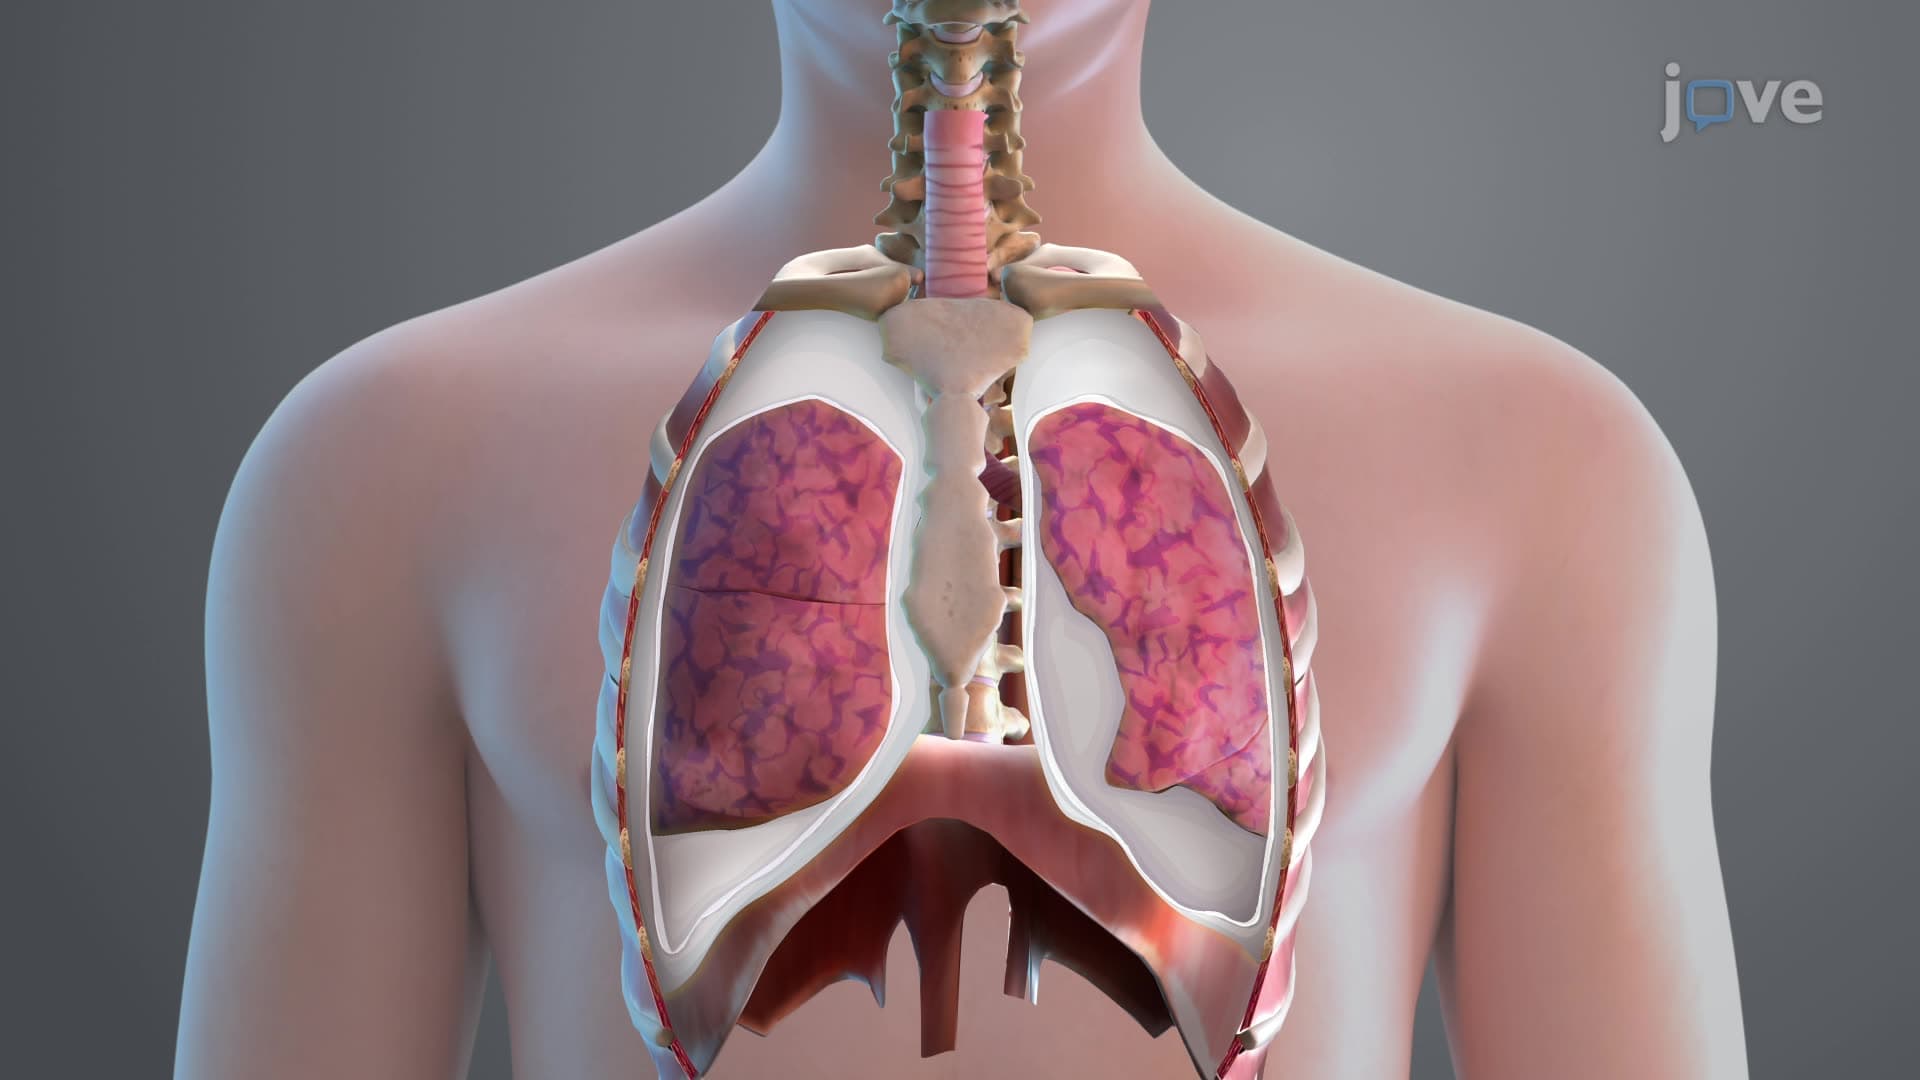
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:13
Pleura of the Lungs
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...