Related Experiment Video
Updated: Oct 2, 2026

An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
The current use of estrogens for growth-suppressant therapy in adolescent girls
Neal D Barnard1, Anthony R Scialli, Suzanne Bobela
1Physicians Committee for Responsible Medicine, Washington, DC 20016, USA. nbarnard@pcrm.org

Objective:
To assess the current prevalence of growth-suppressant therapy using oral estrogens for tall adolescent girls among U.S. pediatric endocrinologists.
Methods:
A questionnaire was mailed to pediatric endocrinologists practicing in the United States, asking how many patients each clinician had recently treated for tall stature using oral estrogens, whether he/she continued to offer such treatment, reasons for offering or declining to offer it, criteria for initiating and terminating treatment, choice of estrogen, and typical doses, durations, and effects.
Results:
Of 411 respondents, 92 (22%) reported having treated 1-5 girls for tall stature during the preceding five years. Only 4 (1%) had treated more than 5 cases during this period. Growth-suppression treatment was currently offered by 137 respondents (33.3%). Reasons for doing so included parents' and patients' concerns about stature and the adverse social effects of unusually tall stature. Reasons for not offering such treatments were that its long-term risks are unknown, that tall stature is not a disease, and a lack of referrals. Few clinicians initiated treatment if predicted mature height was below 183 cm. Treatment was typically terminated based on evidence of epiphyseal fusion, usually within less than two years, although extended treatments were common. Frequently reported adverse effects included weight gain, nausea/vomiting, areolar or nipple pigmentation, headache, and irregular menses.
Conclusions:
Although treatment is less commonly initiated than in the past, many pediatric endocrinologists continue to offer oral estrogens to suppress growth for tall adolescent girls.
Related Concept Videos
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:33
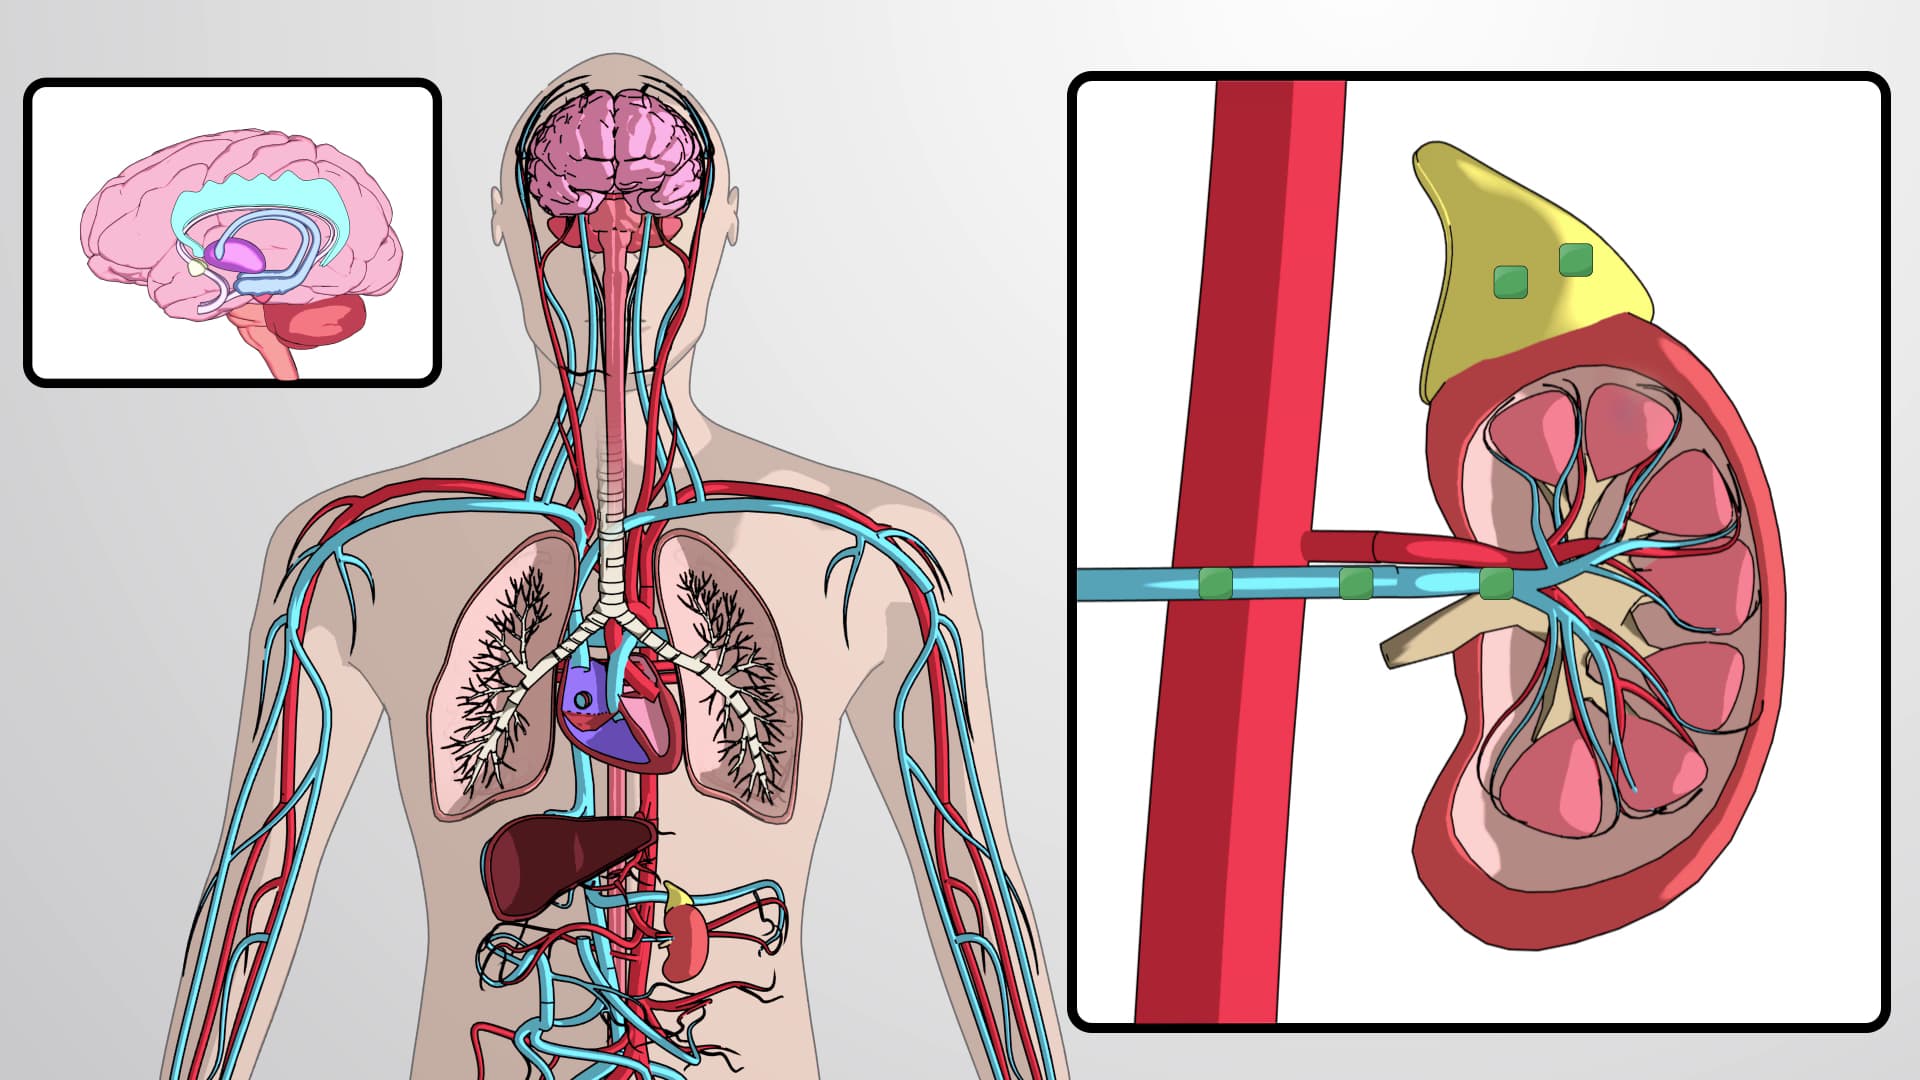
Hormonal Regulation
 02:03
Hormonal Regulation
 02:38
Mitogens and the Cell Cycle
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair growth — and...