Related Experiment Videos
Association between inhaled beta-agonists and the risk of unstable angina and myocardial infarction
David H Au1, J Randall Curtis, Nathan R Every
1Department of Medicine, University of Washington, Seattle 98108, USA. dau@u.washington,edu

Background:
beta-Adrenoceptor agonists (beta-agonists) are commonly used to treat obstructive lung diseases, and preliminary studies have suggested they are associated with an increased risk of adverse cardiovascular outcomes. We further examined the association between acute coronary syndromes and inhaled beta-agonist therapy.
Methods:
We performed a nested, case-control study using data that were collected as part of a larger, ongoing, prospective study of quality improvement in the primary care clinics of seven Veterans Administration Medical Centers. We identified 630 patients with unstable angina or acute myocardial infarction hospitalized between 1996 and 1999. We frequency matched these case patients to 10,486 control subjects according to clinic location, and randomly assigned each an "index date." The computerized pharmacy database at each center was used to ascertain beta-agonist use. Cardiovascular risk factors were assessed from mailed questionnaires and electronic medical records, which included inpatient and outpatient diagnoses, medications, and laboratory results.
Results:
In comparison with patients who had not filled a beta-agonist prescription during the 90 days prior to their index date, patients who had filled a beta-agonist prescription had an increased risk of experiencing an acute coronary syndrome. The increased risk of an acute coronary syndrome persisted after adjusting for age and cardiovascular risk factors, including hypertension, diabetes, and smoking history. Moreover, there was a dose-response relationship with an adjusted odds ratio (OR) of 1.38 for one to two metered-dose inhaler (MDI) canisters (95% confidence interval [CI], 0.86 to 2.23), an OR of 1.57 for three to five MDI canisters (95% CI, 1.01 to 2.46), and an OR of 1.93 for six or more MDI canisters (95% CI, 1.23 to 3.03). After stratifying for receipt of a beta-blocker prescription, the adjusted OR in subjects who did not receive a beta-blocker was 1.55 for one to two MDI canisters (95% CI, 0.60 to 3.99), an OR of 4.07 for three to five canisters (95% CI, 2.17 to 7.64), and an OR of 3.83 for six or more canisters (95% CI, 2.02 to 7.29). Subjects who had received both beta-blockers and beta-agonists had no increase in risk in acute coronary syndromes unless they had filled six or more beta-agonist MDI canisters.
Conclusions:
A prescription for inhaled beta-agonists may increase the risk of myocardial infarction and unstable angina in patients with COPD.
Related Concept Videos
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:25
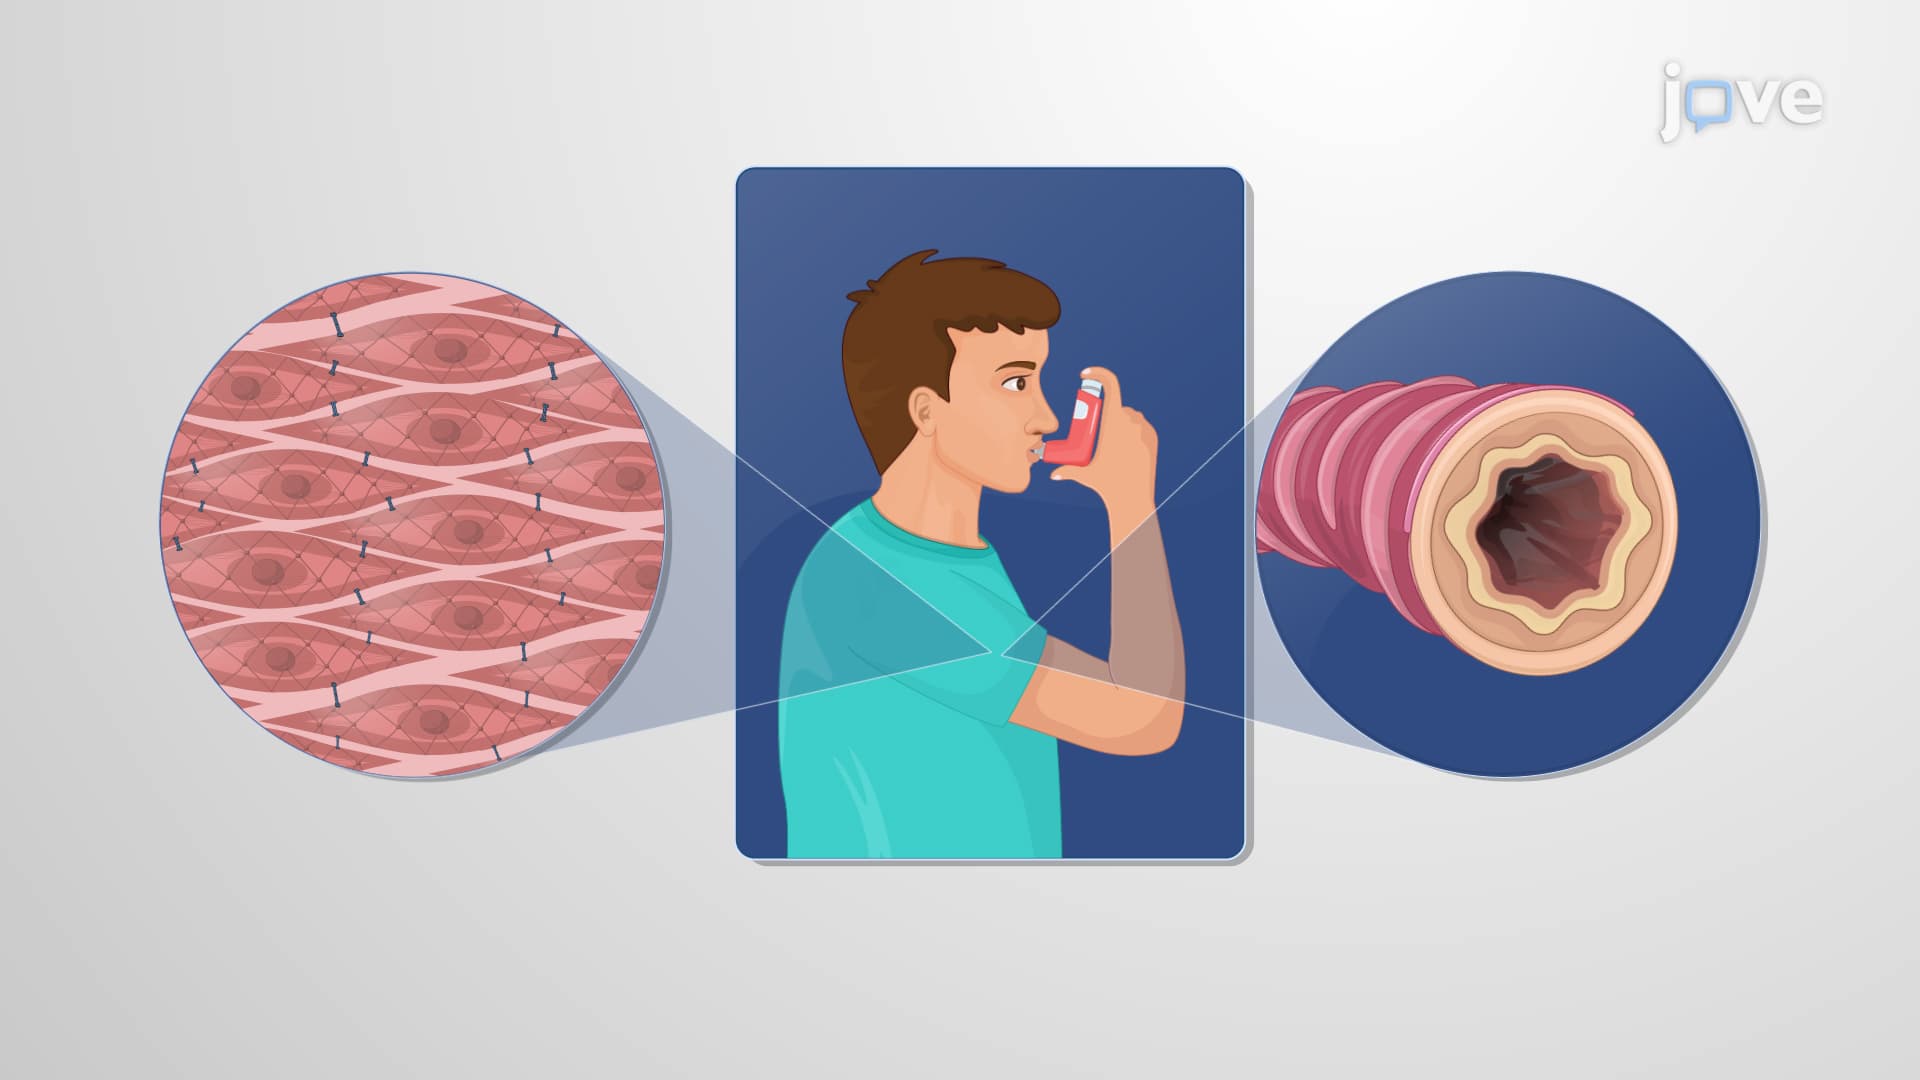
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:26
Angina IV: Management
 01:19
Oral Hypoglycemic Agents: α-Glucosidase Inhibitors
Acarbose and miglitol are typically...
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...