Related Experiment Video
Updated: Oct 2, 2026

Isolation, Fixation, and Immunofluorescence Imaging of Mouse Adrenal Glands
Published on: October 2, 2018
Calretinin and inhibin are useful in separating adrenocortical neoplasms from pheochromocytomas
Merce Jorda1, Madeiros Bruno De, Mehrdad Nadji
1Department of Pathology, University of Miami/Jackson Memorial Medical Center, Florida 33136, USA. mjorda@med.miami.edu

Abstract:
Most adrenocortical neoplasms and pheochromocytomas can be diagnosed by a combination of clinical findings and morphologic features. Occasionally, however, this histologic differential diagnosis requires ancillary tests, such as immunohistochemistry. Both tumors are generally negative for epithelial markers but express synaptophysin. Inhibin and chromogranin are used for the diagnosis of adrenocortical neoplasms and pheochromocytomas, respectively. Both antigens, however, are expressed focally and may be completely negative, particularly in small biopsies. The authors investigated the potential value of adding calretinin to inhibin in the differential diagnosis of these tumors. Fifty-five primary adrenal neoplasms including 33 adrenocortical tumors (21 adenomas and 12 carcinomas), 22 pheochromocytomas, and 7 healthy adrenal glands were examined immunohistochemically for the expression of calretinin and inhibin. Inhibin was demonstrated in 24 (73%) adrenocortical neoplasms. When calretinin was added, the number of tumors staining positively for the two markers alone or in combination increased to 31 (94%). Both antigens showed a focal pattern of distribution in many cases. None of the pheochromocytomas reacted for any of these two markers. Healthy adrenal gland showed a distinct positive and negative pattern of immunoreactivity for both antigens in cortex and medulla, respectively. There were no differences between staining patterns of calretinin and inhibin in healthy adrenal cortex, adrenocortical adenomas, and adrenocortical carcinomas. The authors conclude that the addition of calretinin to inhibin increases the sensitivity of the diagnosis of adrenocortical neoplasms. When used together, they are highly specific and sensitive for the differential diagnosis of these tumors from pheochromocytomas. These markers, however, do not distinguish between benign and malignant adrenocortical neoplasms.


Related Concept Videos
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:31
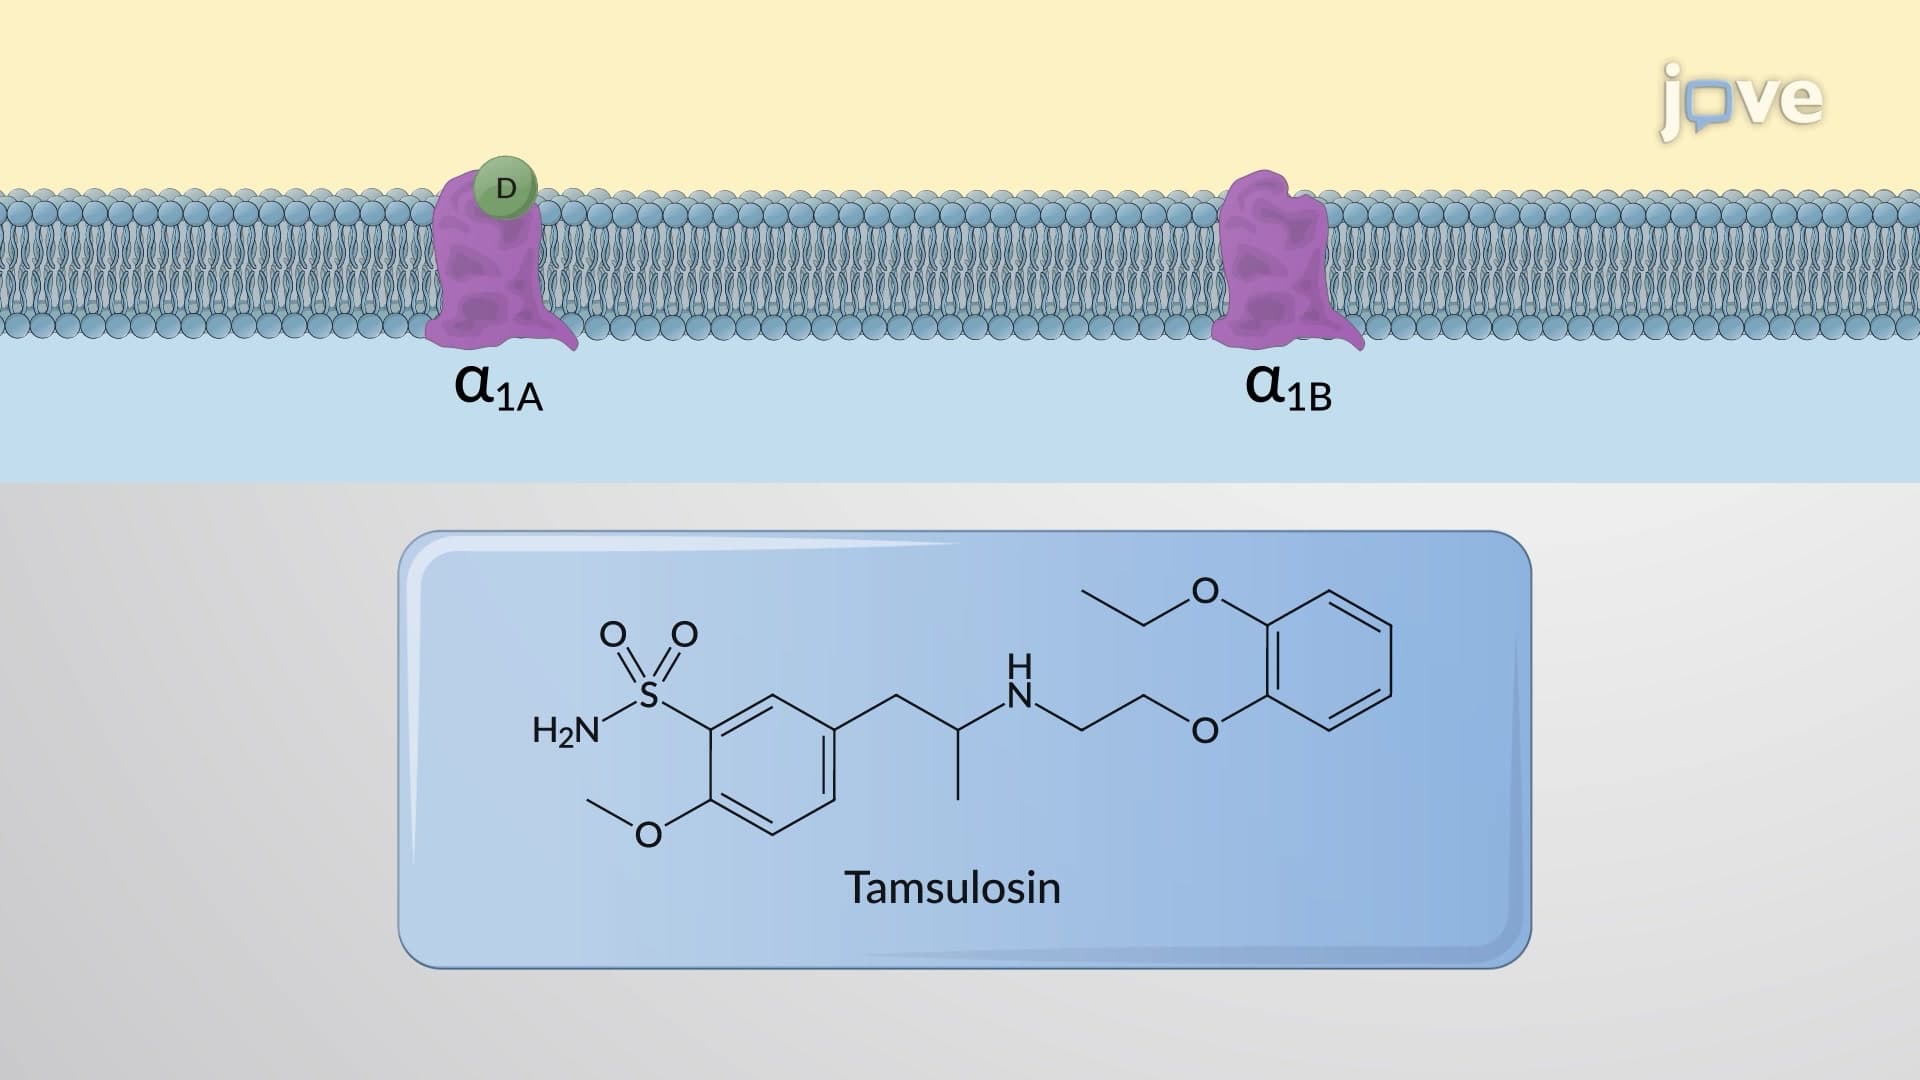
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
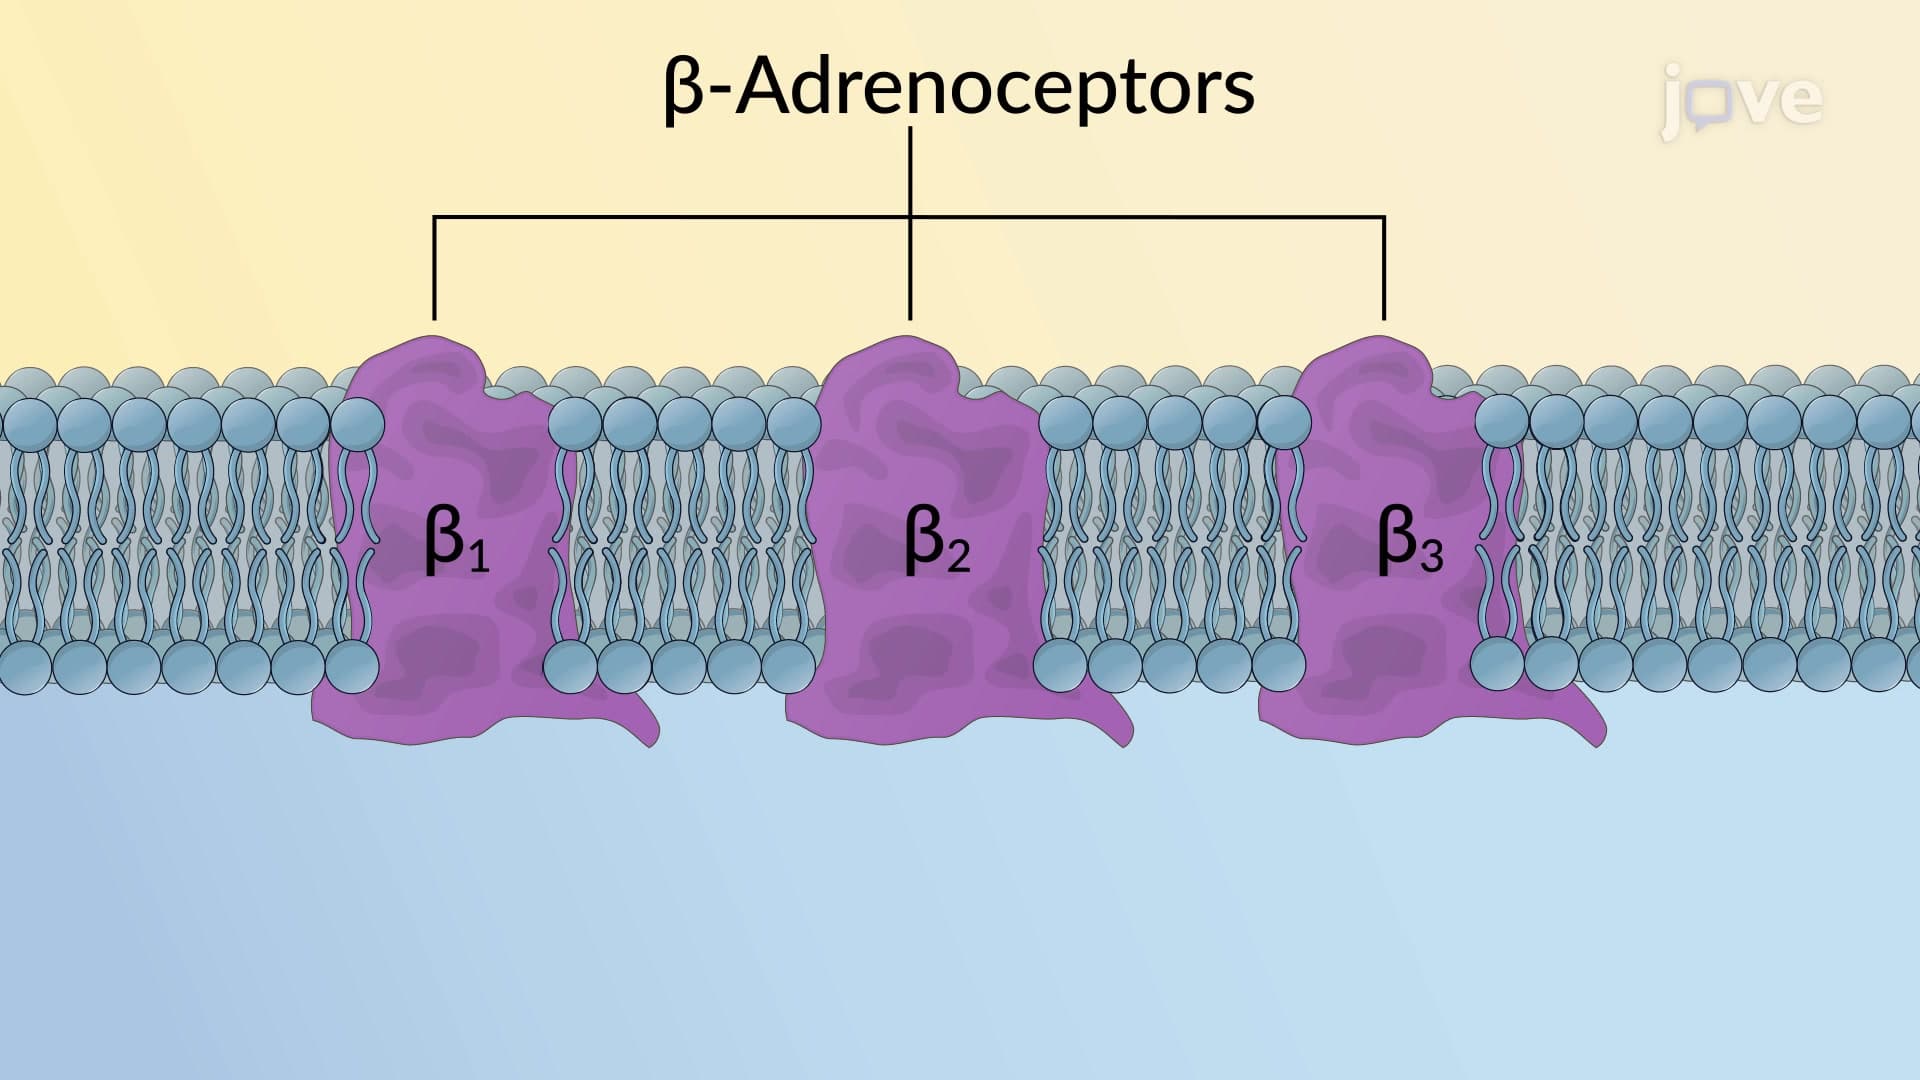
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:17
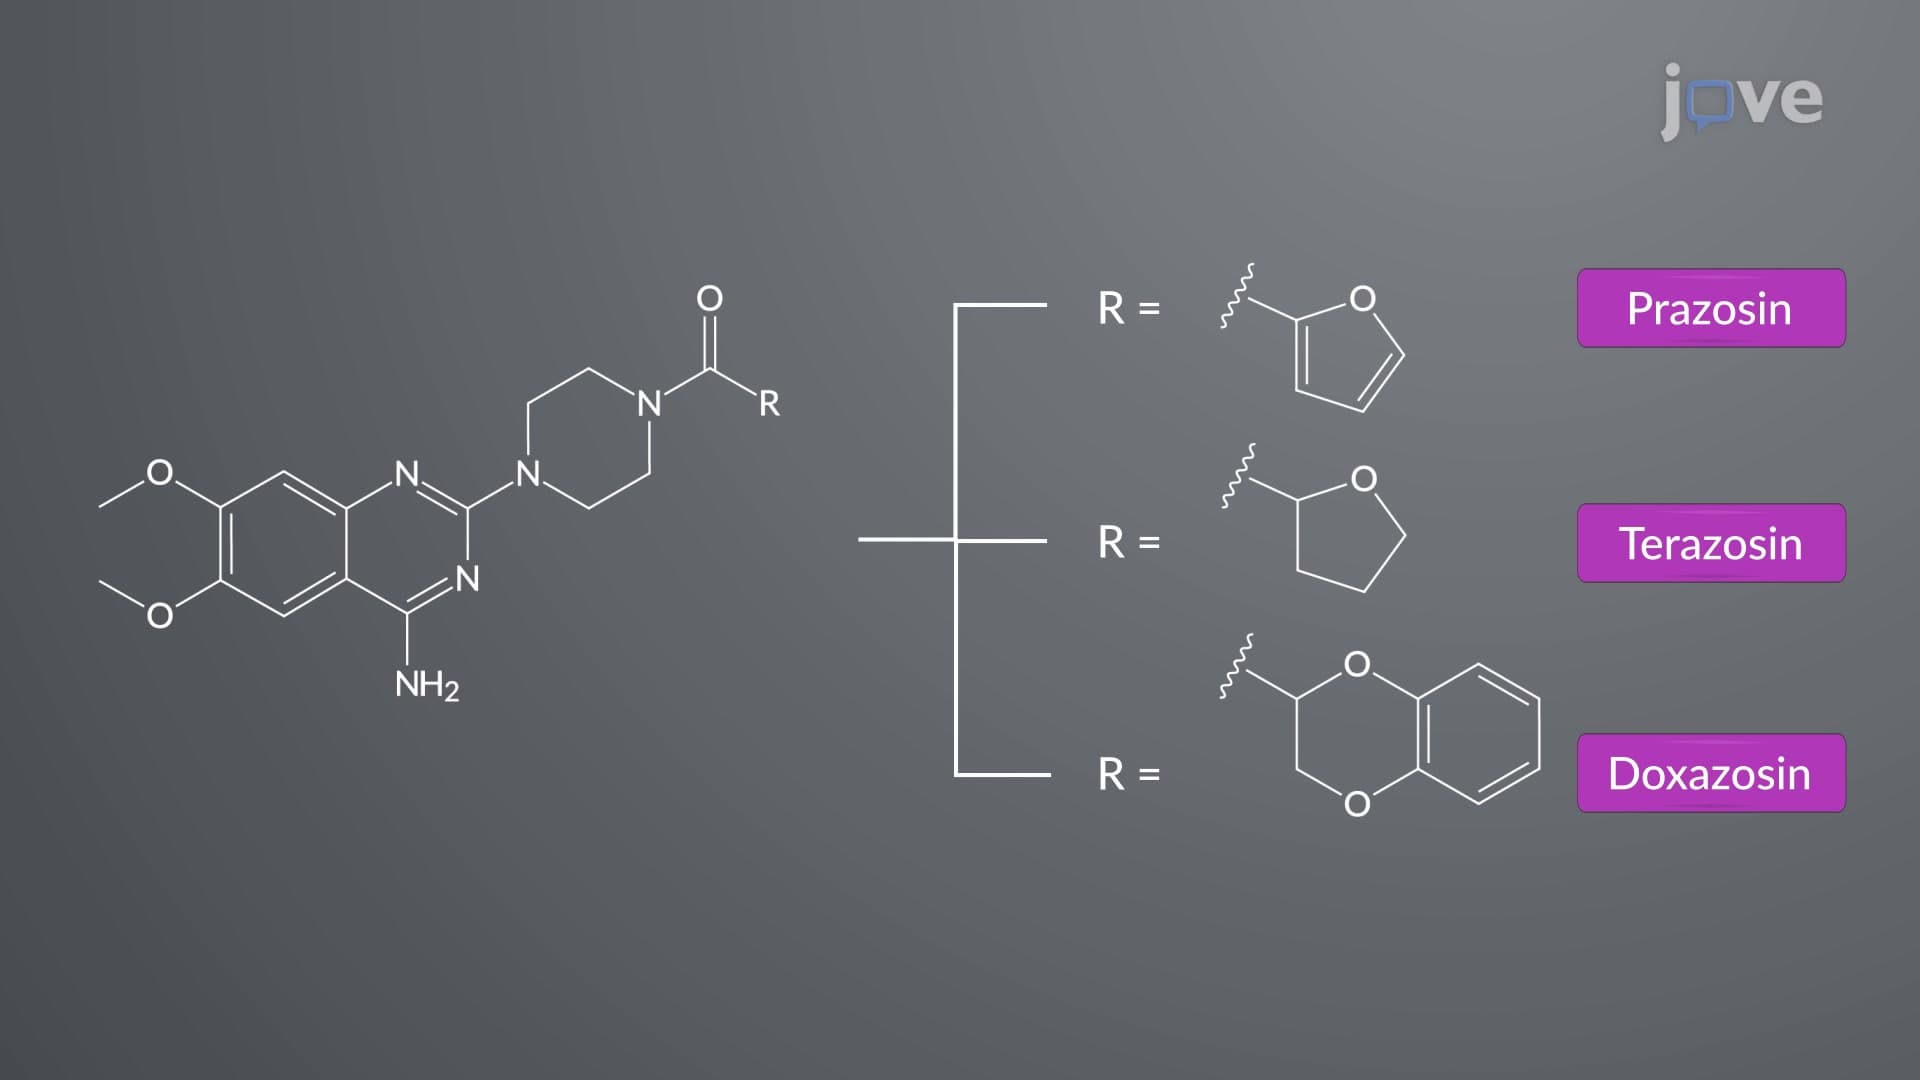
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...