Related Experiment Videos

Pedal gangrene secondary to disseminated intravascular coagulation with gastric carcinoma

Liza Gragasin-Saviano1, Ernest Isaacson, Rodney M Stuck

  • 1Edward Hines, Jr Hospital, Department of Veterans Affairs, Hines, IL, USA.

Related Concept Videos

Gastritis III: Clinical Manifestations and Management01:23

Gastritis III: Clinical Manifestations and Management

The clinical manifestations of gastritis can vary depending on the cause and type of gastritis, but some common symptoms may include the following.
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
Peripheral Artery Disease V: Postoperative Nursing Management01:23

Peripheral Artery Disease V: Postoperative Nursing Management

During the postoperative period, it is crucial to focus on maintaining circulation, identifying and managing potential complications, and planning for discharge.Nursing AssessmentVital signs monitoring: Regularly monitor vital signs, including blood pressure, heart rate, respiratory rate, and temperature, to detect early signs of complications such as bleeding and infection.Circulation assessment: Monitor pulses, perform Doppler assessments, and check capillary refill, color, temperature, and...
Gastritis II: Pathophysiology01:26

Gastritis II: Pathophysiology

The pathophysiology of gastritis begins with the colonization of the stomach lining by Helicobacter pylori (H. pylori). This bacterium spreads mainly via the oral-oral route through saliva or shared utensils, and can also be transmitted in overcrowded or unhygienic environments through contaminated water, despite its brief survival outside the body.ColonizationOnce ingested, H. pylori enters the stomach and begins colonization by navigating through the mucus layer lining the stomach wall. It...
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation01:21

Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
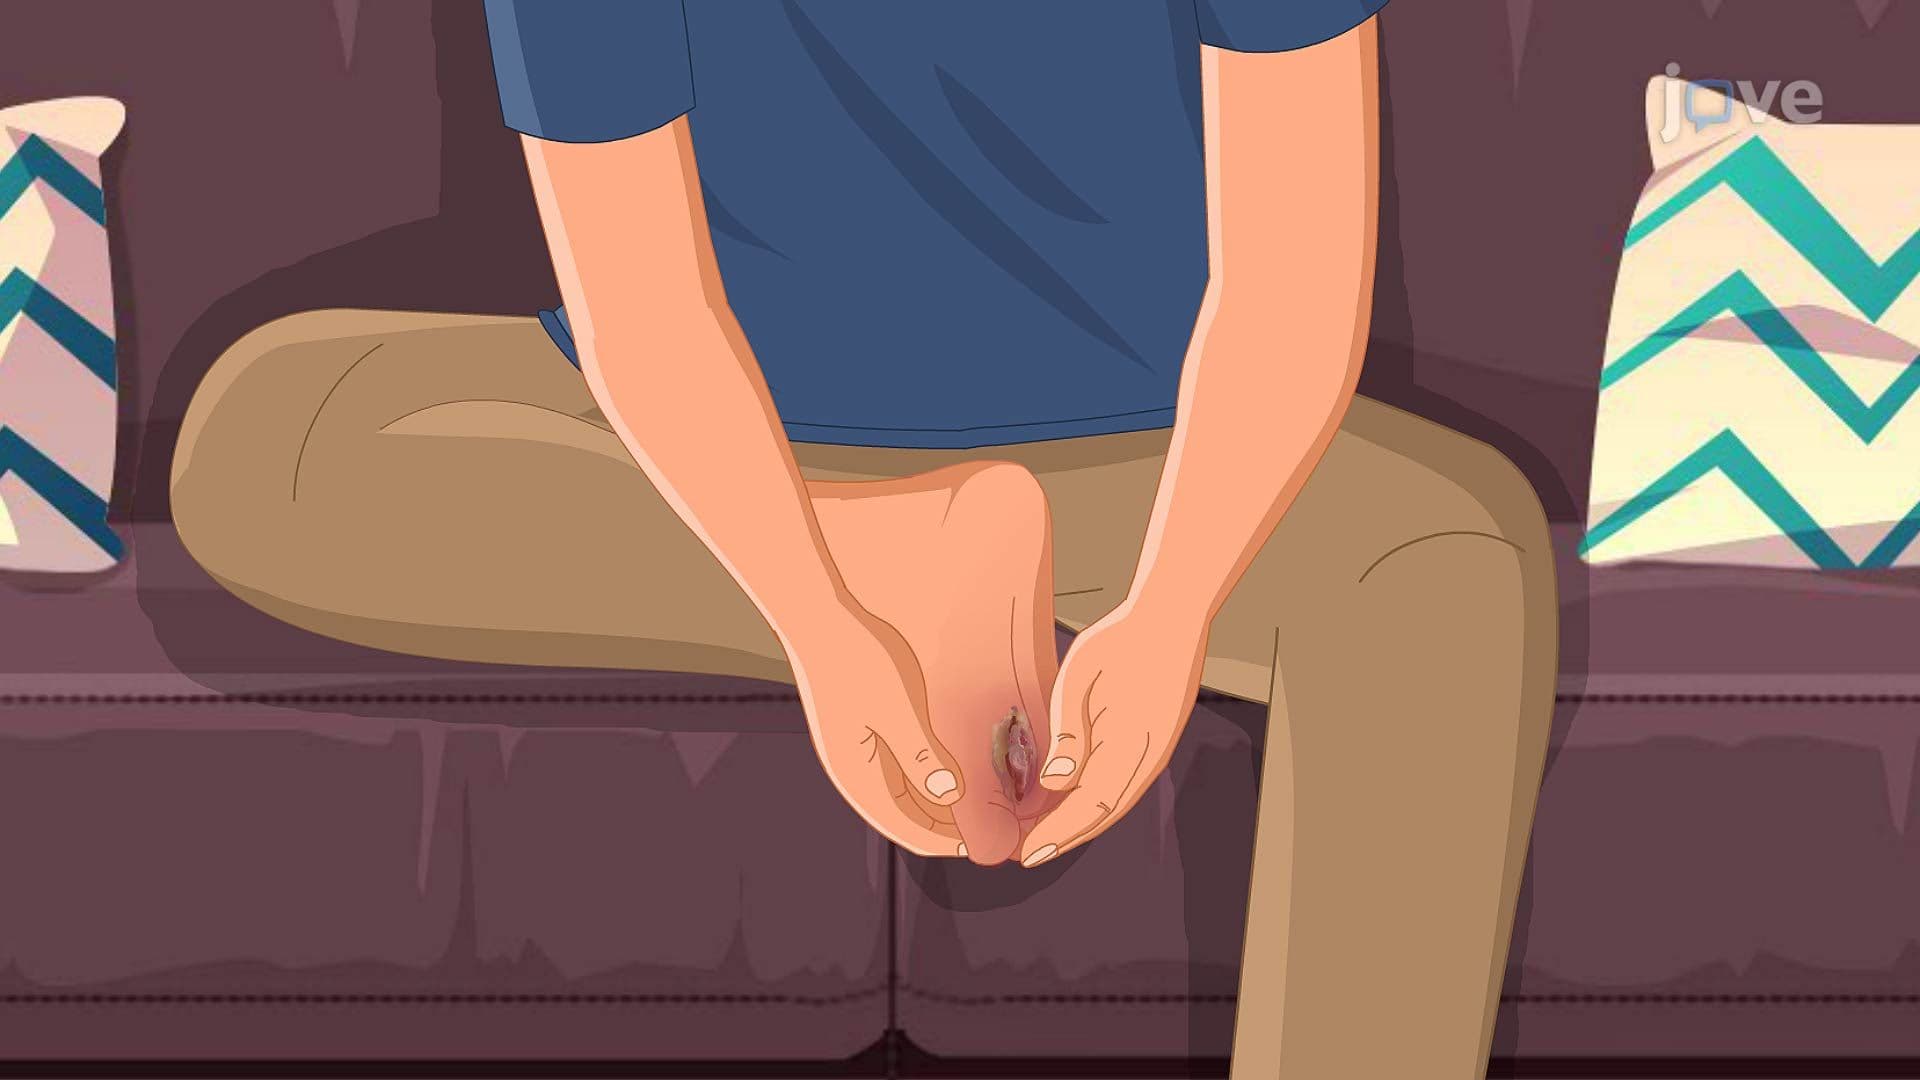
Clinical manifestationsPeripheral Arterial Disease (PAD) manifests through a range of symptoms, from the characteristic intermittent claudication to atypical presentations and severe complications in advanced stages. Intermittent claudication, a hallmark symptom of PAD, presents as exercise-induced muscle pain that typically resolves within minutes of rest. This pain is reproducible and stems from inadequate blood flow, leading to the accumulation of lactic acid produced during anaerobic...
Diabetic Foot Ulcer01:31

Diabetic Foot Ulcer

Definition A diabetic foot ulcer (DFU) is a chronic, non-healing wound that develops in individuals with diabetes. It typically occurs on pressure-bearing areas such as the heel, metatarsal heads, or hallux, and carries a high risk of infection and amputation.Pathophysiology • The development of DFUs can be explained by four interconnected mechanisms: neuropathy, ischemia, infection, and impaired wound healing. • Neuropathy is the most common factor. Sensory neuropathy reduces pain perception,...
Peptic Ulcer Disease III: Clinical Manifestations and Complications01:25

Peptic Ulcer Disease III: Clinical Manifestations and Complications

Duodenal UlcersDuodenal ulcers are the most common form of peptic ulcer disease, presenting with chronic, intermittent epigastric pain. Pain typically appears 2–3 hours after meals, especially when the stomach is empty, often waking patients at night. It is characteristically relieved by food or antacids (“pain–food–relief”). Some patients remain asymptomatic until complications like bleeding or perforation emerge, particularly with NSAID or anticoagulant use.Gastric UlcersGastric ulcers share...
