Related Experiment Video
Updated: Oct 2, 2026
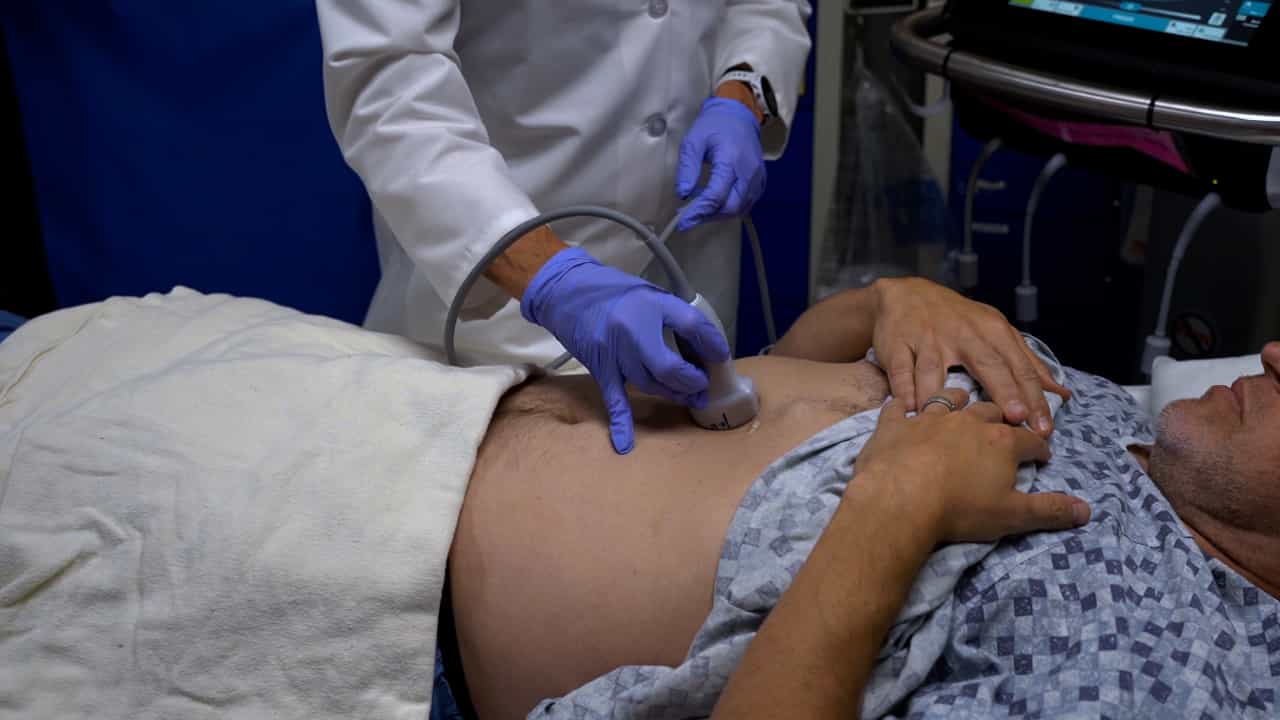
Gastric Point of Care Ultrasound in Adults: Image Acquisition and Interpretation
Published on: September 22, 2023
Amylin is associated with delayed gastric emptying in critically ill children
Anton-Paul T Mayer1, Andrew Durward, Charles Turner
1Department of Paediatric Intensive Care, Guy's Hospital, Saint Thomas Street, London, SE1 9RT, UK. amayer@doctors.org.uk

Objectives:
Amylin is a novel 37 amino acid that is secreted together with insulin from the pancreas in response to enteral nutrient intake. As a potent inhibitor of gastric motility it plays an important role in the control of carbohydrate absorption. In this study we aimed to determine the relationship between amylin levels and gastric emptying in critically ill children.
Design:
Prospective interventional study.
Setting:
Tertiary paediatric intensive care unit.
Patients:
Twenty-three patients were studied following admission to a paediatric intensive care unit. The median age (25th-75th centiles) was 5.8 years (1.5-11.6) and weight 20 kg (12.8-47.5).
Interventions:
Patients were defined as feed-intolerant on the basis of gastric residual volume greater than 125% 4 h after a feed challenge. Three objective measures of gastric emptying were then calculated from a 6 h paracetamol absorption test. Blood glucose, serum insulin and amylin levels were averaged across the paracetamol absorption test period.
Measurements And Results:
Eight patients were classified as feed-intolerant (nTOL) and 15 as feed-tolerant (TOL) [median gastric residual volumes 321% (261-495) and 4% (0-6), respectively]. Gastric emptying was delayed in the feed-intolerant group as assessed by all paracetamol absorption test parameters ( p< or =0.01). The median serum amylin concentration was significantly higher in the feed-intolerant group [nTOL 47.0 (37.7-54.8) versus TOL 22.7 (13.6-26.7) pmol/l, p<0.0001]. A positive correlation between serum amylin and insulin was observed ( r=0.46, p=0.02) but not between amylin and glucose ( r=0.25, p=0.23).
Conclusions:
The use of gastric residual volumes to define feed intolerance is justified in critically ill children. High serum amylin levels are associated with delayed gastric emptying in these patients. The correlation between serum amylin and insulin levels indicates a degree of preservation of pancreatic hormonal co-release.

Related Concept Videos
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:11
Pyloric Obstruction
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:15
Hypoglycemia and Glucagon
 01:27
Esophageal Achalasia