Related Experiment Video
Updated: Mar 6, 2026


Author Spotlight: Optimizing EAS with Long Electrodes for Enhanced Cochlear Coverage and Hearing Preservation
Published on: October 11, 2024
Long-term follow up of carbonic anhydrase II deficiency syndrome
Mohammad Awad1, Abdullah A Al-Ashwal, Nadia Sakati
1Department of Pediatrics, King Faisal Specialist Hospital & Research Center, PO Box 3354 Riyadh 11211, Kingdom of Saudi Arabia.

Insights
Carbonic anhydrase II deficiency syndrome in Saudi children presents with distinctive facial features, growth failure, and renal tubular acidosis. While generally benign, long-term monitoring is crucial for potential neurological complications.
Area of Science:
- Genetics and rare diseases
- Pediatric endocrinology
- Neurology
Background:
- Carbonic anhydrase II deficiency syndrome is a rare genetic disorder.
- It affects multiple organ systems, including skeletal, neurological, and renal functions.
- Long-term clinical data from affected pediatric populations are limited.
Purpose of the Study:
- To delineate the long-term clinical, biochemical, and radiological spectrum of carbonic anhydrase II deficiency syndrome.
- To describe the natural history and outcomes in a cohort of Saudi Arabian children.
- To identify potential complications and inform management strategies.
Main Methods:
- Retrospective evaluation of medical records of 35 Saudi children diagnosed with carbonic anhydrase II deficiency syndrome.
- Diagnosis confirmed by clinical and radiological findings.
- Carbonic anhydrase II levels measured in a subset of patients.
Main Results:
- Patients exhibited characteristic facial features, growth failure, and psychomotor retardation.
- Distal renal tubular acidosis was a consistent biochemical finding.
- Radiological features included metaphyseal osteopetrosis and progressive intracranial calcification in some cases.
- Complications observed were optic nerve entrapment leading to blindness and bone marrow involvement causing anemia.
- Adult height was significantly reduced in both males and females.
Conclusions:
- Carbonic anhydrase II deficiency syndrome is typically compatible with long-term survival but can lead to severe complications.
- Neurological involvement, particularly cranial nerve compromise, requires vigilant monitoring.
- Regular clinical and neurological assessments are essential for early detection and management of complications.
Objective:
To describe the long term clinical, biochemical and radiological features of 35 Saudi Arabian children with carbonic anhydrase II deficiency syndrome who have been followed at King Faisal Specialist Hospital and Research Center, Riyadh since 1979.
Methods:
The records of these patients were retrospectively evaluated. The diagnosis was based on the clinical and the radiological evidence of the disease. Carbonic anhydrase II level was measured in 9 patients.
Results:
Clinically, these patients had typical facial features, growth failure and varying degrees of psychomotor retardation. Biochemically, all children had renal tubular acidosis that was of distal type in the majority of them. Radiologically, this syndrome was characterized by metyphyseal osteopetrosis and intracranial calcification that was progressive in 2 patients. Five patients were blind secondary to optic nerve entrapment and 2 patients developed anemia and secondary erythropoesis due to bone marrow involvement. Nineteen patients had attained the final adult height; the mean adult height was 146 cm (-3 standard deviation) in 11 females and 152 cm (-4 standard deviation) in 8 males. Two patients were married and had clinically and radiologically normal children.
Conclusion:
The syndrome of carbonic anhydrase II deficiency is usually benign in nature and compatible with long term survival, however it can progress and involve the cranial nerves. Close clinical and neurological assessment of these patients is mandatory to early detect and manage potential serious complications.


Related Concept Videos
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:29
Renal Regulation of Acid-Base Balance
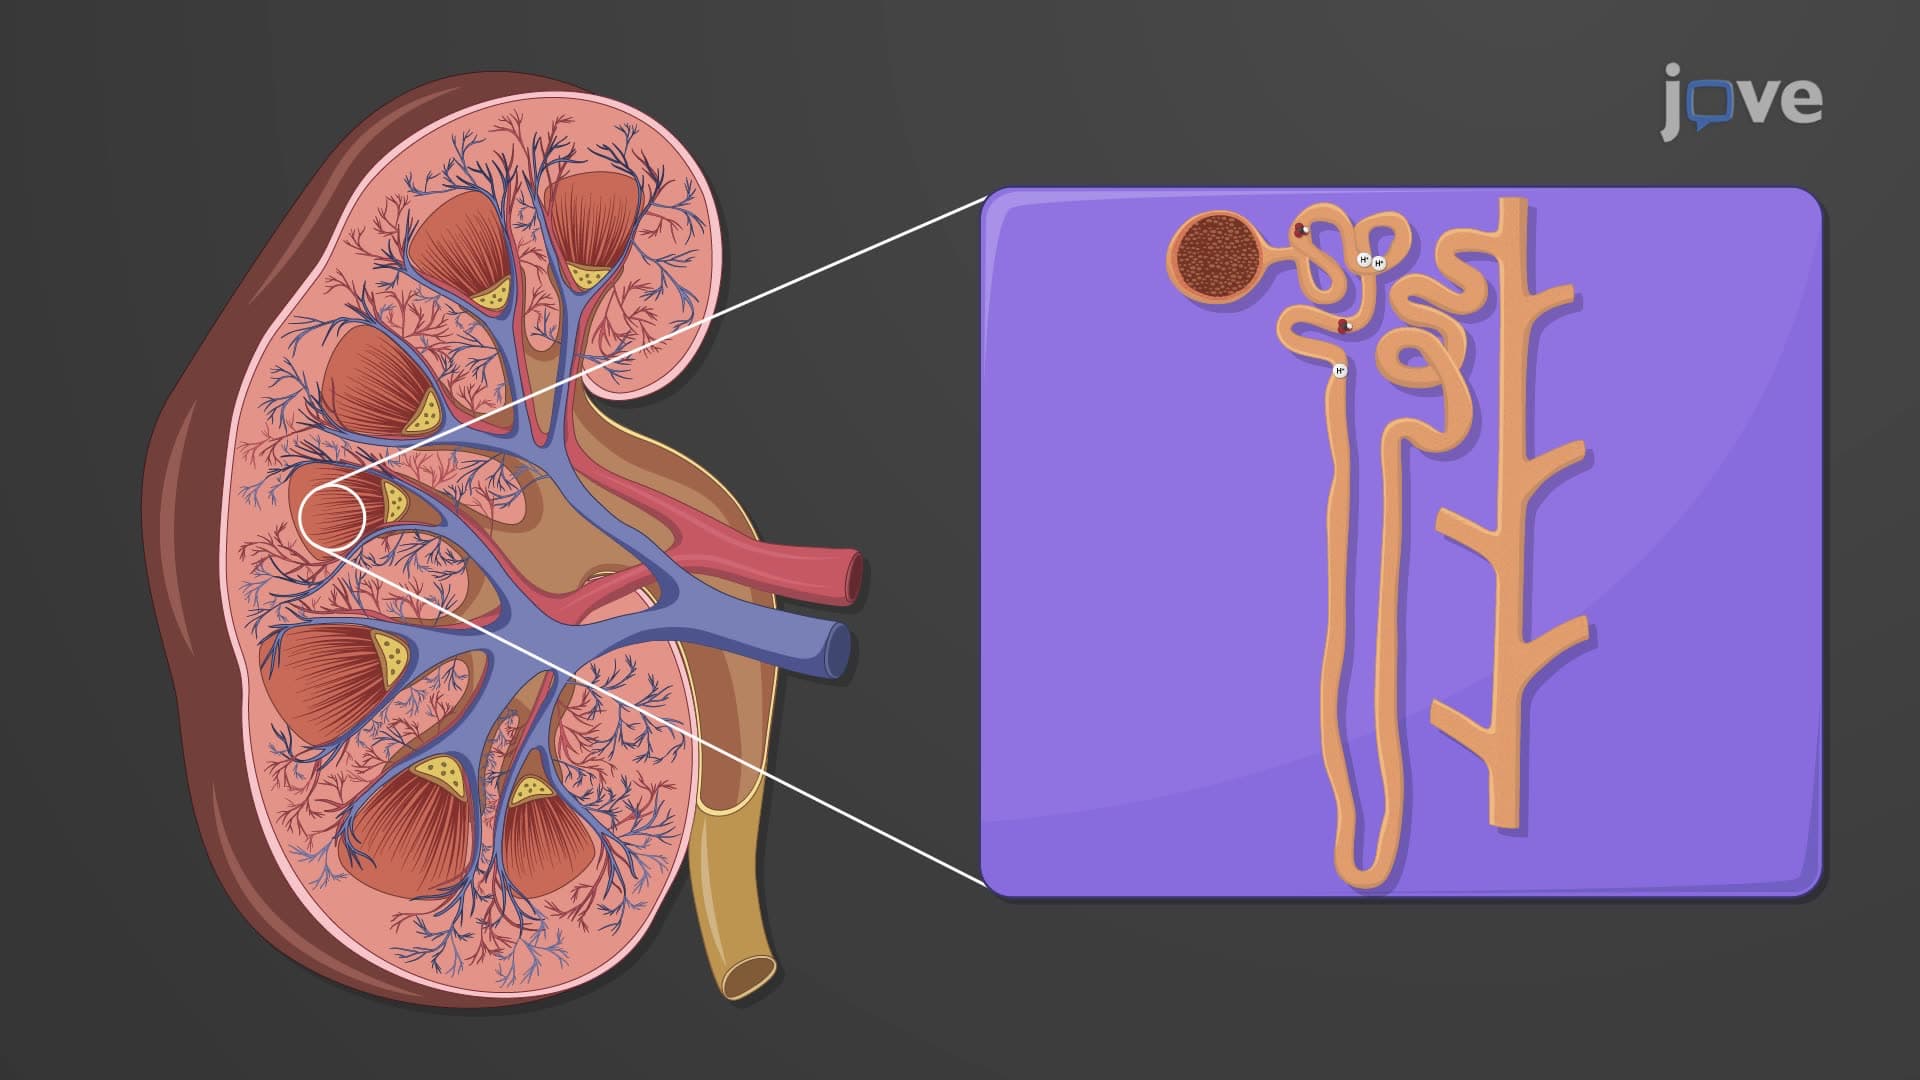
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History