Related Experiment Video
Updated: Oct 1, 2026
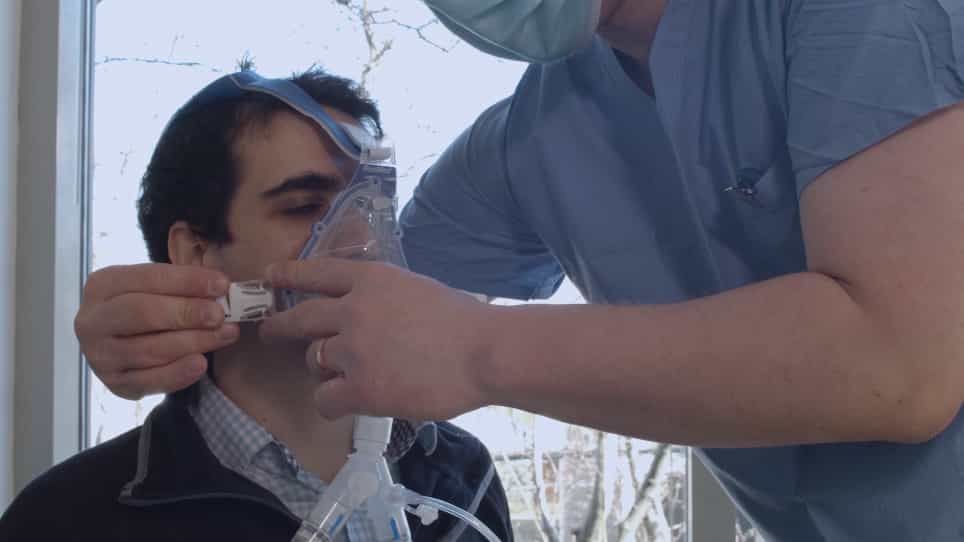
A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Exhaled nitric oxide at school age in prematurely born infants with neonatal chronic lung disease
Suvi T Mieskonen1, L Pekka Malmberg, M Anneli Kari
1Department of Pediatrics, Jorvi Hospital, Espoo, Finland. suvi.mieskonen@hus.fi

Insights
Children born very prematurely with chronic lung disease (CLD) show bronchial obstruction, but exhaled nitric oxide (eNO) levels do not indicate airway inflammation in nonatopic individuals.
Area of Science:
- Pediatric Pulmonology
- Neonatology
- Allergy and Immunology
Background:
- Infants born prematurely with chronic lung disease (CLD) experience significant respiratory issues and bronchial obstruction later in childhood.
- The underlying causes of these lung function abnormalities, particularly the role of inflammation, require further investigation.
Purpose of the Study:
- To assess the potential inflammatory basis of lung function abnormalities in school-aged children born very prematurely.
- To investigate the relationship between exhaled nitric oxide (eNO) levels, atopy, and chronic lung disease (CLD) history in this population.
Main Methods:
- Study included 40 very prematurely born children (7.5-9.6 years) and 14 term-born controls.
- Evaluated lung function using flow-volume spirometry and measured exhaled nitric oxide (eNO).
- Compared eNO levels and spirometry results between atopic/nonatopic prematurely born children, CLD/non-CLD groups, and controls.
Main Results:
- Prematurely born children had significantly lower spirometry values than controls, indicating bronchial obstruction.
- Nonatopic prematurely born children, even with a history of CLD, did not show elevated eNO levels compared to controls.
- eNO levels were significantly higher in atopic prematurely born children than nonatopic ones, but not associated with CLD severity.
Conclusions:
- Airway inflammation, as indicated by eNO, is not evident in nonatopic school-aged children born very prematurely with a history of CLD.
- Exhaled nitric oxide (eNO) levels do not correlate with the severity of chronic lung disease in this cohort.
- Atopy appears to be a significant factor influencing eNO levels in prematurely born children, irrespective of CLD history.
Abstract:
Prematurely born infants with neonatal chronic lung disease (CLD) have increased respiratory morbidity and bronchial obstruction at school age. To evaluate the possible inflammatory basis of lung function abnormalities, we studied 40 children, 7.5-9.6 years of age, born very prematurely (birth weights, 600-1,575 g) and 14 nonatopic term-born controls, using flow-volume spirometry and exhaled nitric oxide (eNO) measurements. In children born prematurely, eNO was significantly higher in atopics than in nonatopics (respective means, 14.8 vs. 6.3 ppb, P = 0.02). Nonatopic prematurely born infants did not differ significantly from controls (means, 6.3 vs. 6.4 ppb, P = ns). Of the 27 nonatopic children not on regular glucocorticoid inhalations, 9 had a history of CLD. Spirometry indicated bronchial obstruction and values that were significantly lower in prematurely born infants with or without CLD than in controls, and they were lower in the CLD than the non-CLD group. However, no significant differences were observed in eNO levels between CLD, non-CLD, and control groups (means, 6.8, 5.9, and 6.4 ppb, P = ns). In nonatopic schoolchildren born very prematurely and with a history of CLD, we found no evidence of airway inflammation associated with increased eNO concentrations. Neither were eNO levels associated with severity of chronic lung disease, as determined by conventional lung function tests. eNO levels were higher in atopic children born prematurely than in controls.
Related Concept Videos
 01:05
Breathing
 01:17
Pulmonary Cycle: Exhalation
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema