Related Experiment Video
Updated: Oct 1, 2026

Studying the Hypothalamic Insulin Signal to Peripheral Glucose Intolerance with a Continuous Drug Infusion System into the Mouse Brain
Published on: January 4, 2018
Mechanism of suppression of insulin signalling with lignocaine
Munetaka Hirose1, J A Jeevendra Martyn, Yoshihiro Kuroda
1Department of Anaesthesiology, Kyoto Prefectural University of Medicine, Kamigyoku, Kyoto 602-8566, Japan. hirose@koto.kpu-m.ac.jp

Abstract:
Lignocaine suppresses insulin-stimulated glucose transport into the cells and insulin-stimulated glycogenesis at doses equivalent to that used in the treatment of muscle pain disorder. We evaluated the direct effect of lignocaine on insulin receptor (IR) kinase activity. After lignocaine (40 mM, approximately equivalent to 1%) or an equal volume (100 microl) saline had been injected into the tibialis anterior muscle of rat, insulin (50 mM g-1 body weight) was administered into the portal vein in vivo. Immunoprecipitation and immunoblotting were used to detect insulin-mediated tyrosine phosphorylation of both IR-beta and insulin receptor substrate (IRS)-1, and insulin-stimulated binding of IRS-1 to p85 regulatory subunit of phosphatidylinositol 3-kinase (PI3-K) in the extracted muscle. In the in vitro study, purified IR from rat liver and/or recombinant IRS-1 protein with adenosine triphosphate were incubated with lignocaine (4 or 40 mM). Lignocaine reduced insulin-stimulated tyrosine phosphorylation of IR-beta to 12.6+/-5.7% (P<0.001), and IRS-1 to 32.1+/-18.8% (P<0.01), and also reduced insulin-stimulated binding of IRS-1 to p85 to 27.4+/-12.7% (P<0.001) relative to control (100%) in muscle in vivo. The in vitro study revealed that lignocaine directly inhibited both basal and insulin-stimulated tyrosine phosphorylation of IR. These results indicate that clinically used doses of lignocaine inhibit insulin signalling in skeletal muscle. The inhibitory effect of lignocaine on tyrosine kinase activity of the IR underlies the suppression of insulin signalling with lignocaine.

Related Concept Videos
 01:23
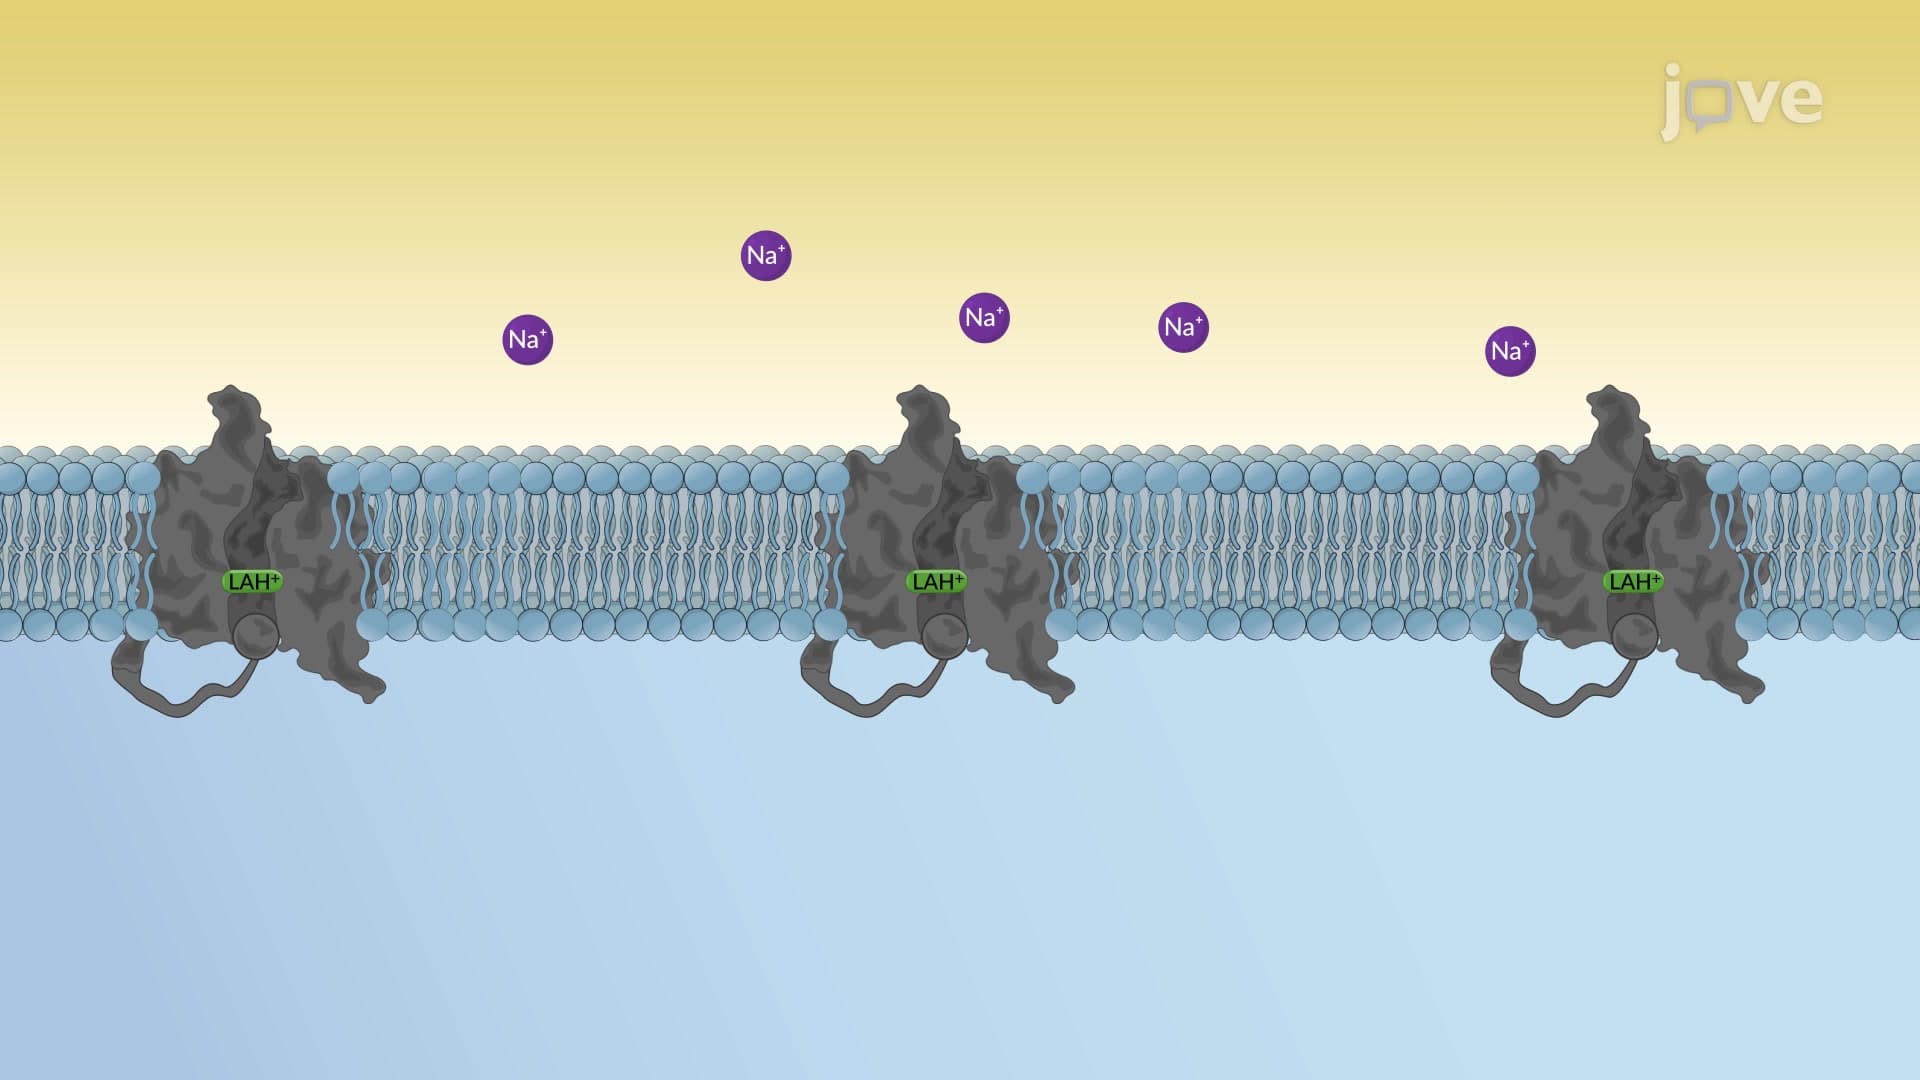
Local Anesthetics: Mechanism of Action
Local anesthetics are amphiphilic molecules consisting of a hydrophobic aromatic part linked to a hydrophilic group by an ester or amide linkage. They are weak bases and are usually available as salts, which increases their solubility and stability. Once administered, LAs exist in the body either...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:06
Oral Hypoglycemic Agents: Glinides
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:05
Insulin Secretory Vesicles
 01:15
Hypoglycemia and Glucagon