Delta aminolevulinic acid urinary excretion in rural region inhabitants

A Borzecki1, H Borzecka, B Nieradko

  • 1Department of Hygiene, Medical University of Lublin.

Annales Universitatis Mariae Curie-Sklodowska. Sectio D: Medicina
|April 30, 2002
PubMed

Related Concept Videos

Drug Elimination by Renal Route: Tubular Reabsorption01:22

Drug Elimination by Renal Route: Tubular Reabsorption
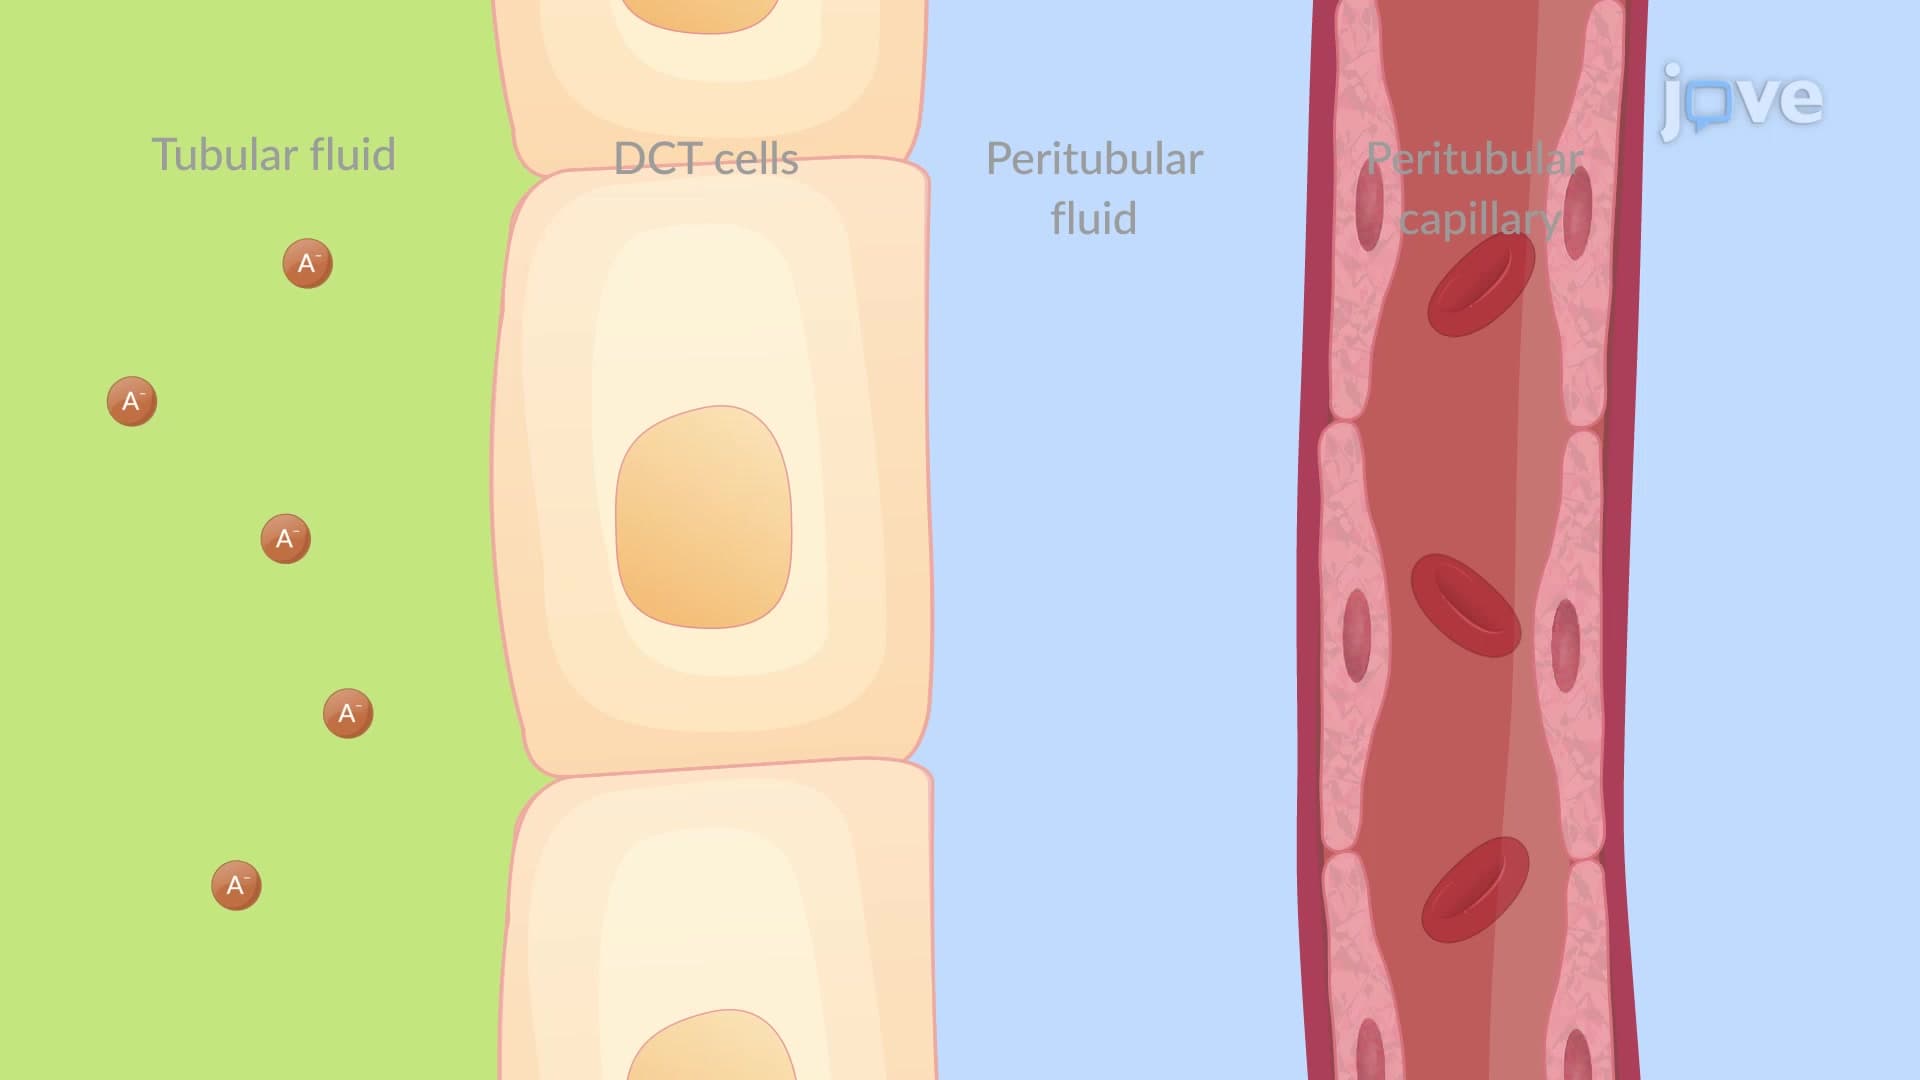
During the process of renal excretion, as the glomerular filtrate progresses to the distal convoluted tubule (DCT), drugs that are highly permeable, lipophilic, and nonionized undergo passive reabsorption from the tubular fluid into the surrounding peritubular capillaries. This reabsorption process restricts their elimination through the kidneys. However, the majority of drugs are either weak acids or weak bases, and their ionization level is dependent on pH. By altering the pH of urine, the...
Drug Elimination: Non-Renal Routes01:23

Drug Elimination: Non-Renal Routes

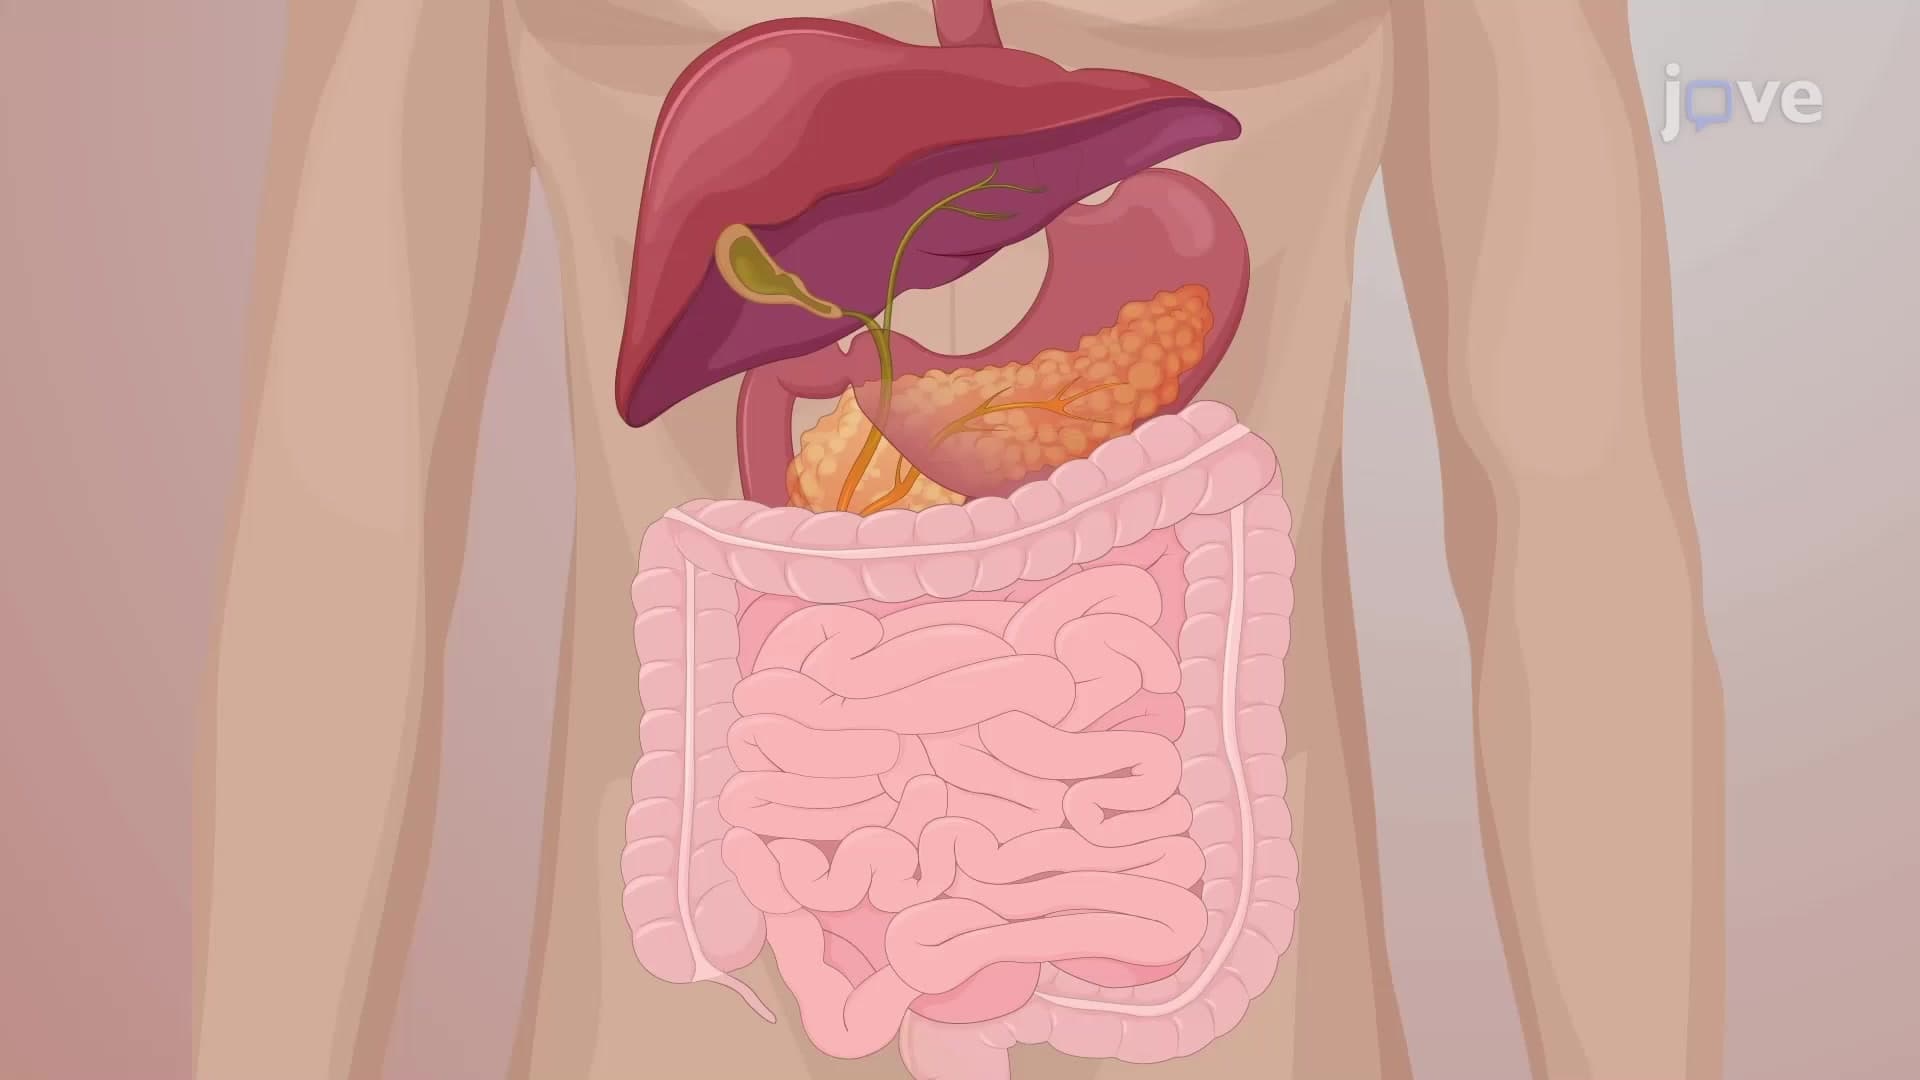
The liver plays a pivotal role in eliminating drugs and their metabolites, primarily through a process known as biliary excretion. This process involves the hepatocytes, the primary cells in the liver that generate bile. A range of transporters actively expels polar drugs or hydrophilic drug metabolites into the bile, which transports the drugs and metabolites into the small intestine. From here, they are eventually expelled from the body through feces. In some instances, the original drug or a...
Renal Drug Excretion: Tubular Secretion01:28

Renal Drug Excretion: Tubular Secretion
Active tubular secretion is a robust, energy-demanding process that utilizes carrier systems to transport drugs into renal tubules. The active renal secretion systems include the organic anion transporter (OAT) for weak acids and the organic cation transporter (OCT) for weak bases. Structurally similar drugs can compete for the same transporter, potentially leading to drug accumulation and toxicity. However, this principle can be exploited therapeutically. One example is probenecid (Probalan),...
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa01:22

Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa

The pH of urine, the drug's pKa, and the urine flow rate are vital parameters for drug reabsorption and excretion. Urinary pH varies between 4.6 and 8.0 and is influenced by diet, drug intake, and the patient's pathophysiology. It affects a drug's ionization state and reabsorption. For instance, carbohydrate-rich food produces alkaline urine promoting drug excretion, while proteins and certain medications like ascorbic acid lead to acidic urine enhancing reabsorption.
The pKa of a drug,...
Drug Excretion: Miscellaneous Routes01:10

Drug Excretion: Miscellaneous Routes

Drug excretion involves various organs, including the liver, intestines, skin, and eyes. In the case of drugs or toxins, they can be actively secreted into bile by transporters in the hepatocyte's canalicular membrane. These substances enter the GI tract during digestion and may be reabsorbed into the body from the intestine. This process, known as enterohepatic recycling, can significantly prolong the presence and effects of a substance in the body. To interrupt this cycle, specific substances...
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance01:25

Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance

In healthy individuals, serum creatinine levels remain stable due to a balance between its constant production—primarily from muscle metabolism—and renal excretion. Creatinine is freely filtered by the glomeruli, making it a valuable marker for estimating renal function. When the glomerular filtration rate (GFR) decreases, the kidneys can only eliminate less creatinine, causing serum levels to rise.Serum creatinine concentration is widely used to estimate creatinine clearance (Clcr), a...