Nerve entrapments of the lower leg, ankle and foot in sport
Related Experiment Video
Updated: Sep 7, 2026
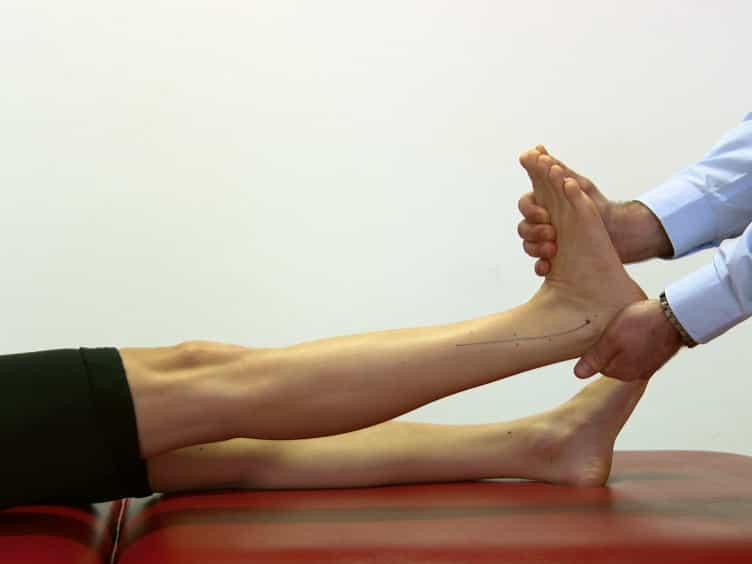
Diagnosis of Musculus Gastrocnemius Tightness - Key Factors for the Clinical Examination
Published on: July 7, 2016
Paul McCrory1, Simon Bell, Chris Bradshaw
1Department of Neurology, Olympic Park Sports Medicine Centre, Melbourne, Victoria, Australia. pmccrory@compuserve.com

Abstract:
Exercise-related leg pain is a common and yet difficult management problem in sports medicine. There are many common causes of such symptoms including stress fractures and muscle compartment syndromes. There are also a number of less common but important conditions including popliteal artery entrapment and nerve entrapment syndromes. Even for an astute clinician, distinction between the different medical causes may be difficult given that many of their presenting features overlap. This review highlights the common clinical presentations and raises a regional approach to the diagnosis of the neurogenic symptoms. In part, this overlapping presentation of different pathological conditions may be due to a common aetiological basis of many of these conditions namely, fascial dysfunction. The same fascial restriction that predisposes to muscle compartment syndromes may also envelop the neurovascular structures within the leg resulting in either ischaemic or neurogenic symptoms. For many athletes with chronic exercise-related leg pain, combinations of such problems often coexist suggesting a more widespread fascial pathology. In our clinical experience, we often label such patients as 'fasciopaths'; however, the precise pathophysiological basis of this fascial problem remains to be elucidated. This review discusses the various nerve entrapment syndromes in the lower limb that may result in exercise-related leg pain in the sporting context. The anatomy, clinical presentation, investigation, medical management and surgical treatment are discussed at length for each of the syndromes. It is clear from clinical experience that the outcome of surgical management of such syndromes fares much better where a clear dermatomal pain distribution is present or where focal weakness and/or sensory symptoms appropriate for the nerve are present. In many situations, however, nonspecific leg pain or vague nonlocalising sensory symptoms are present and in such situations, alternative diagnoses must be considered and investigated appropriately. As mentioned above, many different pathologies may coexist in the lower limb and may be a source of confusion for the clinician or alternatively may be the reason for poor treatment outcomes.


Related Concept Videos
 01:11
Pulse Assessment Sites
 01:10
Bones of the Lower Limb: Tibia and Fibula
 01:10
Ankle Joint
 01:28
Muscles of the Leg that Move the Foot and Toes
Anterior Compartment
The anterior compartment includes muscles that contribute to the dorsiflexion of the foot. This compartment houses the tibialis anterior, extensor hallucis longus, and extensor digitorum longus muscles.
 01:08
Reflex Activity
A reflex exam is a diagnostic procedure performed by a healthcare professional to evaluate the functionality of a patient's...
 01:15
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the knee,...