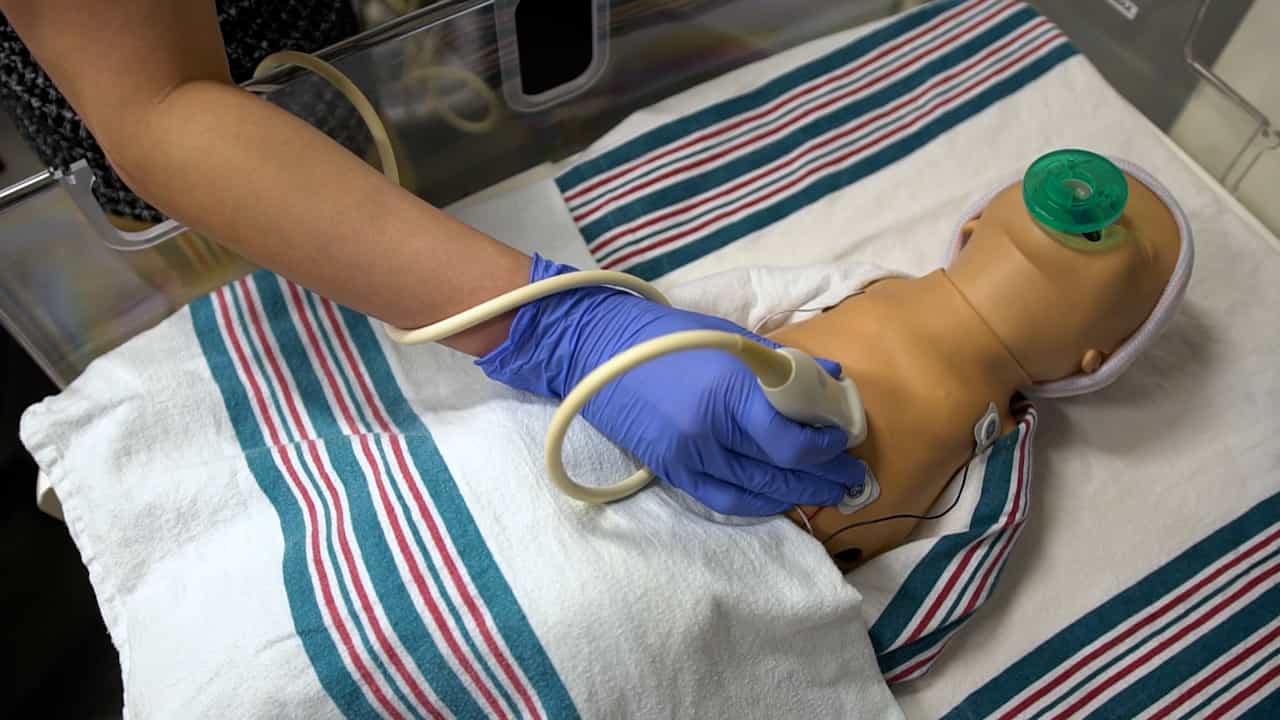
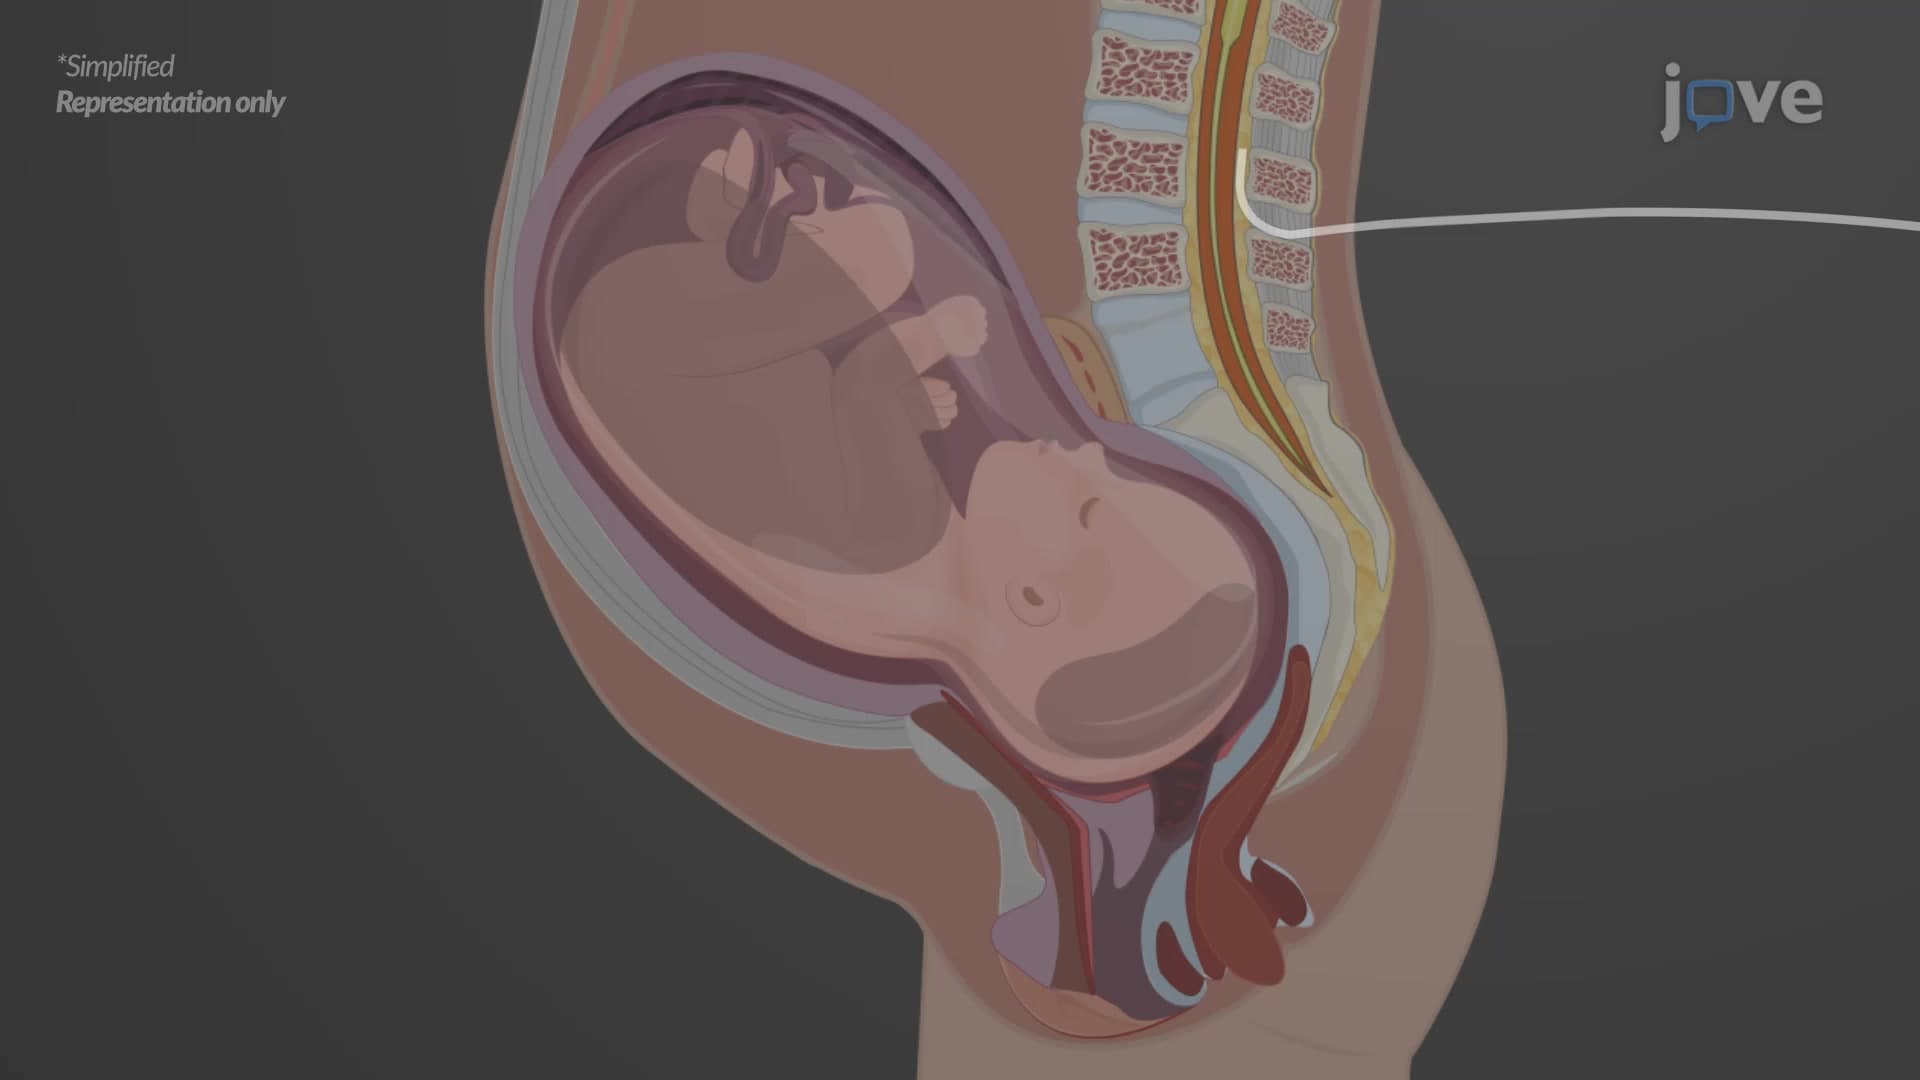
Pulmonary Doppler flow velocity pattern during caudal epidural anaesthesia in children
Related Experiment Video
Updated: Oct 1, 2026
Fetal Echocardiography and Pulsed-wave Doppler Ultrasound in a Rabbit Model of Intrauterine Growth Restriction
Published on: June 29, 2013
Hiroshi Ozasa1, Keishi Hashimoto, Yoji Saito
1Department of Anesthesiology, Shimane Medical University Izumo, Japan.

Insights
Caudal anesthesia in children can affect pulmonary hemodynamics. Lidocaine, but not saline, administered epidurally caused significant changes in pulmonary Doppler flow velocity, suggesting increased pulmonary arterial resistance.
Area of Science:
- Pediatric Anesthesiology
- Cardiovascular Physiology
Background:
- Hemodynamic effects of caudal anesthesia in pediatric patients remain under-investigated.
- Pulmonary hemodynamics during caudal anesthesia require further evaluation.
Purpose of the Study:
- To assess the impact of caudal anesthesia on pulmonary hemodynamics in children.
- Utilize Doppler-echocardiography to evaluate hemodynamic changes.
Main Methods:
- Fifteen children undergoing elective surgery were divided into two groups: lidocaine or saline in the caudal epidural space.
- General anesthesia was induced and maintained with nitrous oxide and sevoflurane.
- Hemodynamic data, including echocardiography, were measured pre- and post-epidural administration.
Main Results:
- No significant changes in mean blood pressure or left ventricular function were observed in either group.
- Pulmonary Doppler flow velocity indices (peak velocity, acceleration-to-ejection time ratio) decreased significantly after caudal lidocaine administration.
- Saline administration did not result in significant changes in pulmonary Doppler flow velocity.
Conclusions:
- Caudal epidural anesthesia with lidocaine induces changes in pulmonary Doppler flow velocity in children.
- These changes are likely attributed to an increase in pulmonary arterial resistance.
Background:
Haemodynamic effects of caudal anaesthesia in children have not been fully investigated. In the present study, we evaluated pulmonary haemodynamics during caudal anaesthesia in otherwise healthy children using Doppler-echocardiography.
Methods:
Fifteen children undergoing elective lower abdominal surgery were randomly divided into two groups: nine children received 1.5% lidocaine and six physiological saline in the caudal epidural space. General anaesthesia was slowly induced and maintained using nitrous oxide and sevoflurane in oxygen. An epidural catheter was inserted into the caudal epidural space. Haemodynamic data including those with echocardiography were measured before and after epidural administration of lidocaine or saline.
Results:
Mean blood pressure, end diastolic diameter of the left ventricle, ejection fraction of the left ventricle and mean velocity circumferential fibre shortening did not change in either group following caudal epidural block. Indices of pulmonary Doppler flow velocity, including peak velocity of pulmonary flow and acceleration-to-ejection time ratio, demonstrated a significant decrease after caudal lidocaine, but not after saline.
Conclusions:
Our data suggest that pulmonary Doppler flow velocity changes during caudal epidural anaesthesia, probably due to an increase in the pulmonary arterial resistance.